Related Experiment Video
Updated: Sep 21, 2026

Bile Duct Ligation in Mice: Induction of Inflammatory Liver Injury and Fibrosis by Obstructive Cholestasis
Published on: February 10, 2015
Selective surgical management of progressive familial intrahepatic cholestasis (Byler's disease)
1Liver Transplant Program, University of California, San Francisco 94143-0780, USA.

Insights
Partial biliary diversion (PBD) offers a promising primary therapy for progressive familial intrahepatic cholestasis (PFIC), effectively managing symptoms and halting liver fibrosis. Orthotopic liver transplantation (OLT) remains crucial for advanced cases.
Area of Science:
- Pediatric Gastroenterology
- Hepatology
- Surgical Gastroenterology
Background:
- Progressive familial intrahepatic cholestasis (PFIC) is a severe childhood liver disease characterized by cholestasis, fibrosis, and potential cirrhosis.
- Medical therapies for PFIC are often unsuccessful, leading to poor growth and liver failure.
- Biliary diversion has shown potential in halting or reversing liver fibrosis progression.
Purpose of the Study:
- To evaluate the efficacy of partial biliary diversion (PBD) as a primary treatment for PFIC.
- To reserve orthotopic liver transplantation (OLT) for PFIC patients with progressive disease or established cirrhosis.
- To assess long-term outcomes of PBD and OLT in pediatric PFIC patients.
Main Methods:
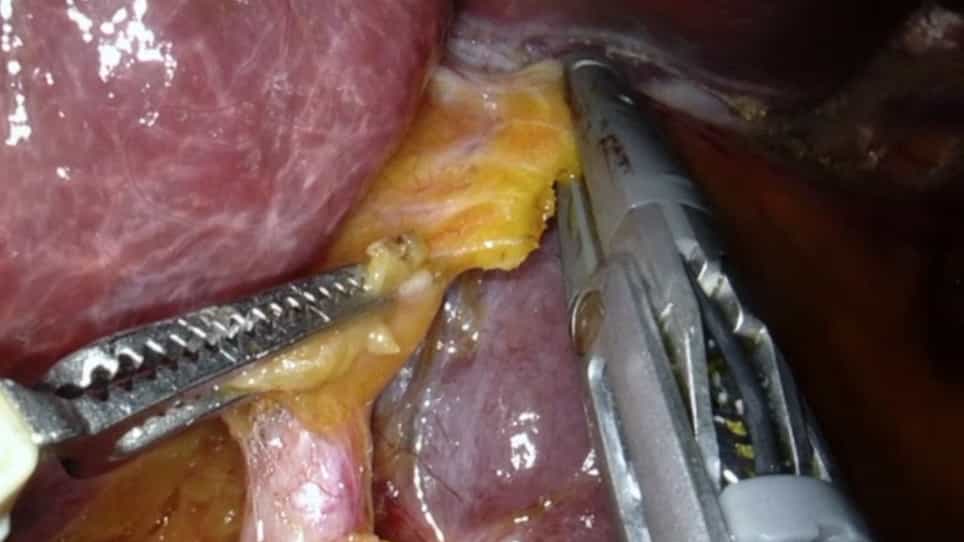
- Eight PFIC patients underwent partial biliary diversion (PBD) involving a jejunal segment anastomosed to the gallbladder.
- Eleven PFIC patients with hepatic insufficiency or cirrhosis received standard orthotopic liver transplantation (OLT).
- Patient outcomes were monitored for clinical symptoms, liver function tests, and hepatic fibrosis progression.
Main Results:
- Six of eight (75%) patients treated with PBD showed complete symptom resolution and halted fibrosis progression, with normal liver function markers.
- Two patients did not benefit from PBD due to advanced fibrosis or cirrhosis.
- Eight of eleven (73%) patients who underwent OLT for advanced disease or cirrhosis are alive postoperatively.
Conclusions:
- Partial biliary diversion (PBD) is an effective primary therapy for PFIC, capable of resolving symptoms and reversing liver fibrosis.
- Early diagnosis and intervention are critical for successful PBD outcomes before irreversible liver damage occurs.
- Orthotopic liver transplantation (OLT) remains a vital option for PFIC patients with advanced liver disease or cirrhosis.
Abstract:
Progressive familial intrahepatic cholestasis (PFIC) presents in early childhood with pruritus, jaundice, hepatomegaly, and growth failure. Medical therapy is unsuccessful, with progression from cholestasis to hepatic fibrosis, cirrhosis, and ultimately death before the age of 10 years. Because of evidence that biliary diversion can arrest or reverse progression to hepatic fibrosis, we have used partial biliary diversion (PBD) as primary therapy in PFIC, reserving orthotopic liver transplantation (OLT) for children who have progressive disease or established cirrhosis. Seventeen children with PFIC (aged 2 months to 19 years) have been treated. PBD was performed in eight cases. In these procedures, a 10-cm properistaltic jejunal segment was anastomosed to the side of the gallbladder, terminating as an end stoma for the collection and discard of bile. Eleven patients with hepatic insufficiency (or end-stage cirrhosis) received OLT using standard techniques, at the average age of 4 years. Six of the eight children treated with PBD had complete resolution of clinical symptoms and remain well 1 to 13 years postoperatively. These six patients have conjugated bilirubin values of less than 0.3 mg/dL, normal transaminases, and a serum bile salt concentration of less than 10 nmol/mL. All have had either reversal or no progression of the hepatic fibrosis. Postoperative bleeding complications occurred in two (25%), which required reoperation. One patient had an adhesive intestinal obstruction that was managed surgically 9 months postoperatively. Two patients had no benefit from PBD, and all of them had severe bridging fibrosis (1) or cirrhosis (3). These and nine others with cirrhosis at the time of presentation received orthotopic liver transplantation; of these, eight are alive (1 to 5 years postoperatively). These results show the importance of establishing a correct diagnosis in children with cholestasis. Clinical symptoms often are severe in children with PFIC before the development of irreversible hepatic fibrosis. Because several patients who appear to have been cured with PBD initially were scheduled for OLT, it is important that transplant surgeons recognize the feasibility of this approach.

Related Concept Videos
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: