Related Experiment Video
Updated: Aug 17, 2026
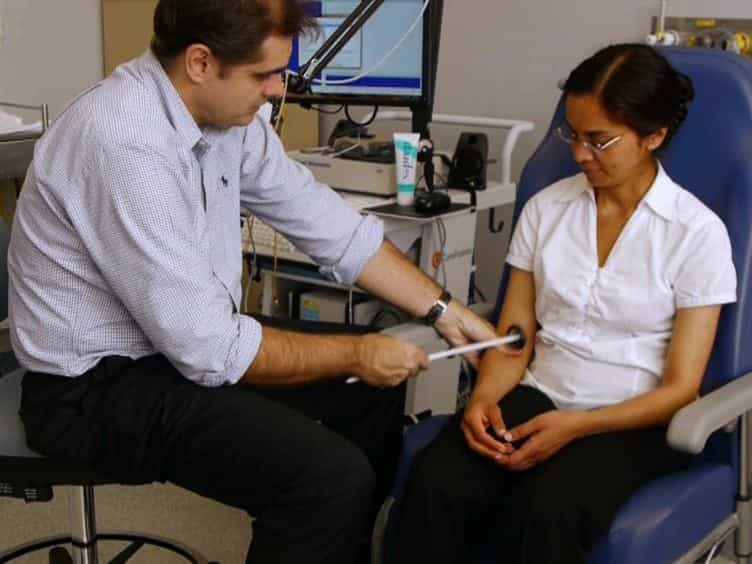

Utility of Dissociated Intrinsic Hand Muscle Atrophy in the Diagnosis of Amyotrophic Lateral Sclerosis
Published on: March 4, 2014
[A 34-year-old woman with delayed motor milestones, high arched palate, and proximal muscle weakness]
T Yamamoto1, T Kitada, E Hirasawa
1Department of Neurology, Juntendo University, Izunagaoka Hospital, Tokyo, Japan.

We report a right-handed 34-year-old woman with diffuse muscle atrophy. The patient was a full-term infant of uneventful delivery, however, motor milestones were delayed in that neck control was obtained at 10 months of the age and she started to walk unassisted at 2 years of the age. Mental development was normal. She was unable to run with her mates at her kindergarten and she required a handrail when she walk up the stairs. She could not close her mouth completely at the primary school. She was unable to use a straw as a middle school pupil. Recently, she noted difficulty in raising her head from the supine position, and has become unable to walk a long distance. She was admitted to our hospital in September 17, 1994 when she was 34-year-old. On admission, general physical examination revealed that she looked slender weighing 38 kg with 149.5 cm height. She showed a high arched palate, slight scoliosis, and pes equinus. Otherwise general physical examination was unremarkable. Upon neurologic examination, she was alert and well oriented. Cranial nerves were unremarkable except for bilateral facial atrophy and moderate weakness. Her voice was of nasal quality, and swallowing was slightly difficult. No atrophy was noted in the sternocleidomastoid muscle. She showed waddling gait and positive Gowers' sign. Diffuse muscle atrophy was noted and mild to moderate weakness was presented more in the proximal part in both upper and lower extremities, however, deltoid muscles retained normal power. No ataxia was noted. All the deep tendon reflexes were lost. Sensation was intact. Routine laboratory examination was unremarkable. Serum CK was 56 IU/l. Electromyography revealed myogenic changes in the deltoid, biceps, and quadriceps muscles. A diagnostic biopsy was performed in the left biceps brachii muscle. The patient was discussed in the neurologic CPC, and the chief discussant arrived at the conclusion that the patient had nemaline myopathy. Opinions were divided among nemaline myopathy, central core disease, and congenital fiber type disproportion. Histologic examination of the biopsied specimen revealed marked atrophy of type 1 muscle fibers; many central nuclei were seen in the type 1 fibers. Approximately 70% of the muscle fibers were type 1 fibers. No nemaline rods or central cores were noted. Histologic appearance was consistent with the diagnosis of congenital fiber type disproportion.
We report a right-handed 34-year-old woman with diffuse muscle atrophy. The patient was a full-term infant of uneventful delivery, however, motor milestones were delayed in that neck control was obtained at 10 months of the age and she started to walk unassisted at 2 years of the age. Mental development was normal. She was unable to run with her mates at her kindergarten and she required a handrail when she walk up the stairs. She could not close her mouth completely at the primary school. She was unable to use a straw as a middle school pupil. Recently, she noted difficulty in raising her head from the supine position, and has become unable to walk a long distance. She was admitted to our hospital in September 17, 1994 when she was 34-year-old. On admission, general physical examination revealed that she looked slender weighing 38 kg with 149.5 cm height. She showed a high arched palate, slight scoliosis, and pes equinus. Otherwise general physical examination was unremarkable. Upon neurologic examination, she was alert and well oriented. Cranial nerves were unremarkable except for bilateral facial atrophy and moderate weakness. Her voice was of nasal quality, and swallowing was slightly difficult. No atrophy was noted in the sternocleidomastoid muscle. She showed waddling gait and positive Gowers' sign. Diffuse muscle atrophy was noted and mild to moderate weakness was presented more in the proximal part in both upper and lower extremities, however, deltoid muscles retained normal power. No ataxia was noted. All the deep tendon reflexes were lost. Sensation was intact. Routine laboratory examination was unremarkable. Serum CK was 56 IU/l. Electromyography revealed myogenic changes in the deltoid, biceps, and quadriceps muscles. A diagnostic biopsy was performed in the left biceps brachii muscle. The patient was discussed in the neurologic CPC, and the chief discussant arrived at the conclusion that the patient had nemaline myopathy. Opinions were divided among nemaline myopathy, central core disease, and congenital fiber type disproportion. Histologic examination of the biopsied specimen revealed marked atrophy of type 1 muscle fibers; many central nuclei were seen in the type 1 fibers. Approximately 70% of the muscle fibers were type 1 fibers. No nemaline rods or central cores were noted. Histologic appearance was consistent with the diagnosis of congenital fiber type disproportion.
More Related Videos
 19:53
Single-stage Dynamic Reanimation of the Smile in Irreversible Facial Paralysis by Free Functional Muscle Transfer
Published on: March 1, 2015
 06:35
In Vivo Electrophysiological Measurement of Compound Muscle Action Potential from the Forelimbs in Mouse Models of Motor Neuron Degeneration
Published on: June 15, 2018
Related Concept Videos
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:19
Multiple Sclerosis l: Introduction
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:12
Alterations in Muscle Tone ll
 01:11
Alterations in Muscle Tone lll