Missed injuries in abdominal trauma
Related Experiment Video
Updated: Oct 13, 2026
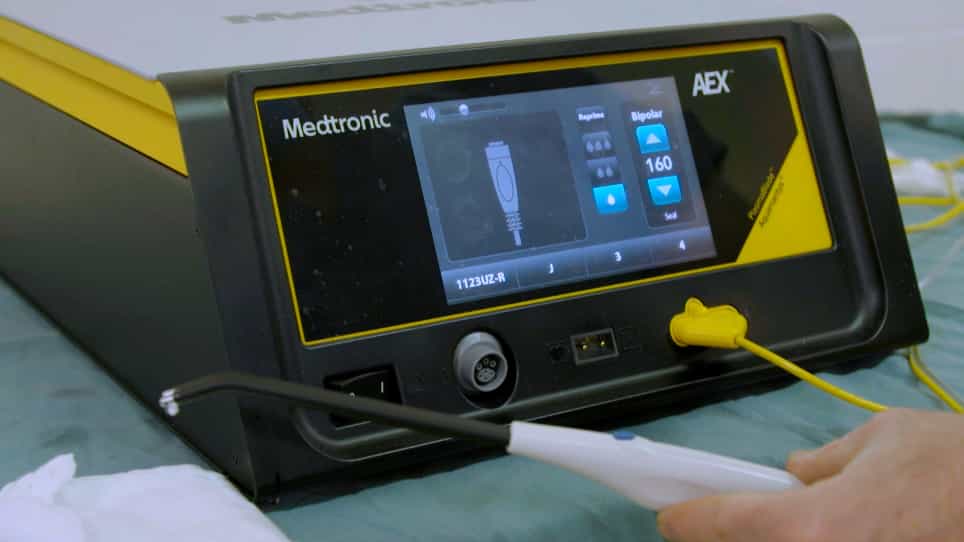
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020

Abstract:
Injuries missed at initial diagnoses or operations have the potential to cause disastrous complications in abdominal trauma patients. The aim of this retrospective study is to assess the causes and the outcomes of missed abdominal injuries. Twelve patients (2%) with missed injuries were identified among 607 abdominal trauma patients operated on from 1985 to 1993. Ten patients were male and two were female. The modes of the trauma were ten blunt injuries (83%) and two stab penetrating injuries (17%). Five cases had delayed operations because of clinical errors in the initial diagnosis. Their causative factors were obscured trauma history (two cases), radiologic misinterpretation (two cases), no reliable radiologic finding (one case), and admission to inappropriate department (one case). Missed injured organs were spleen (two cases), liver (one case), diaphragm (one case), and rectum (one case). Median delayed time was 7 days (3 to 96 days). Another seven cases of injuries were missed at the time of initial operation because of incomplete exploration. Their causative factors were surgical inexperience (two cases), severe peritoneal adhesions (one case), neglected exploration of retroperitoneal hematoma (two cases), underestimated mesocolic vascular injury (one case), and early contraction of the perforating wound with intraoperative hypotension (one case). Missed injured organs were stomach (two cases), duodenum (one case), rectum (one case), pancreas (one case), urinary bladder (one case), and rectosigmoid mesocolon (one case). Median time interval between initial and second operation was 9 days (4 to 32 days). Two patients died of complications directly related to their missed injuries. Major complication and mortality rates of missed injuries were 83 and 17%, respectively. These were significantly higher compared with those (39 and 6.3%, respectively) of detected abdominal injuries. We conclude that missed abdominal injuries can cause high mortality and morbidity, and, therefore, a systematic approach, including careful history taking, complete diagnostic procedure, complete surgical explorations, and early reoperation are mandatory for patients with multiple trauma.
Related Concept Videos
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:23
Assessment of the Abdomen III: Palpation
 01:25
Assessment of the Abdomen I: Inspection and Auscultation
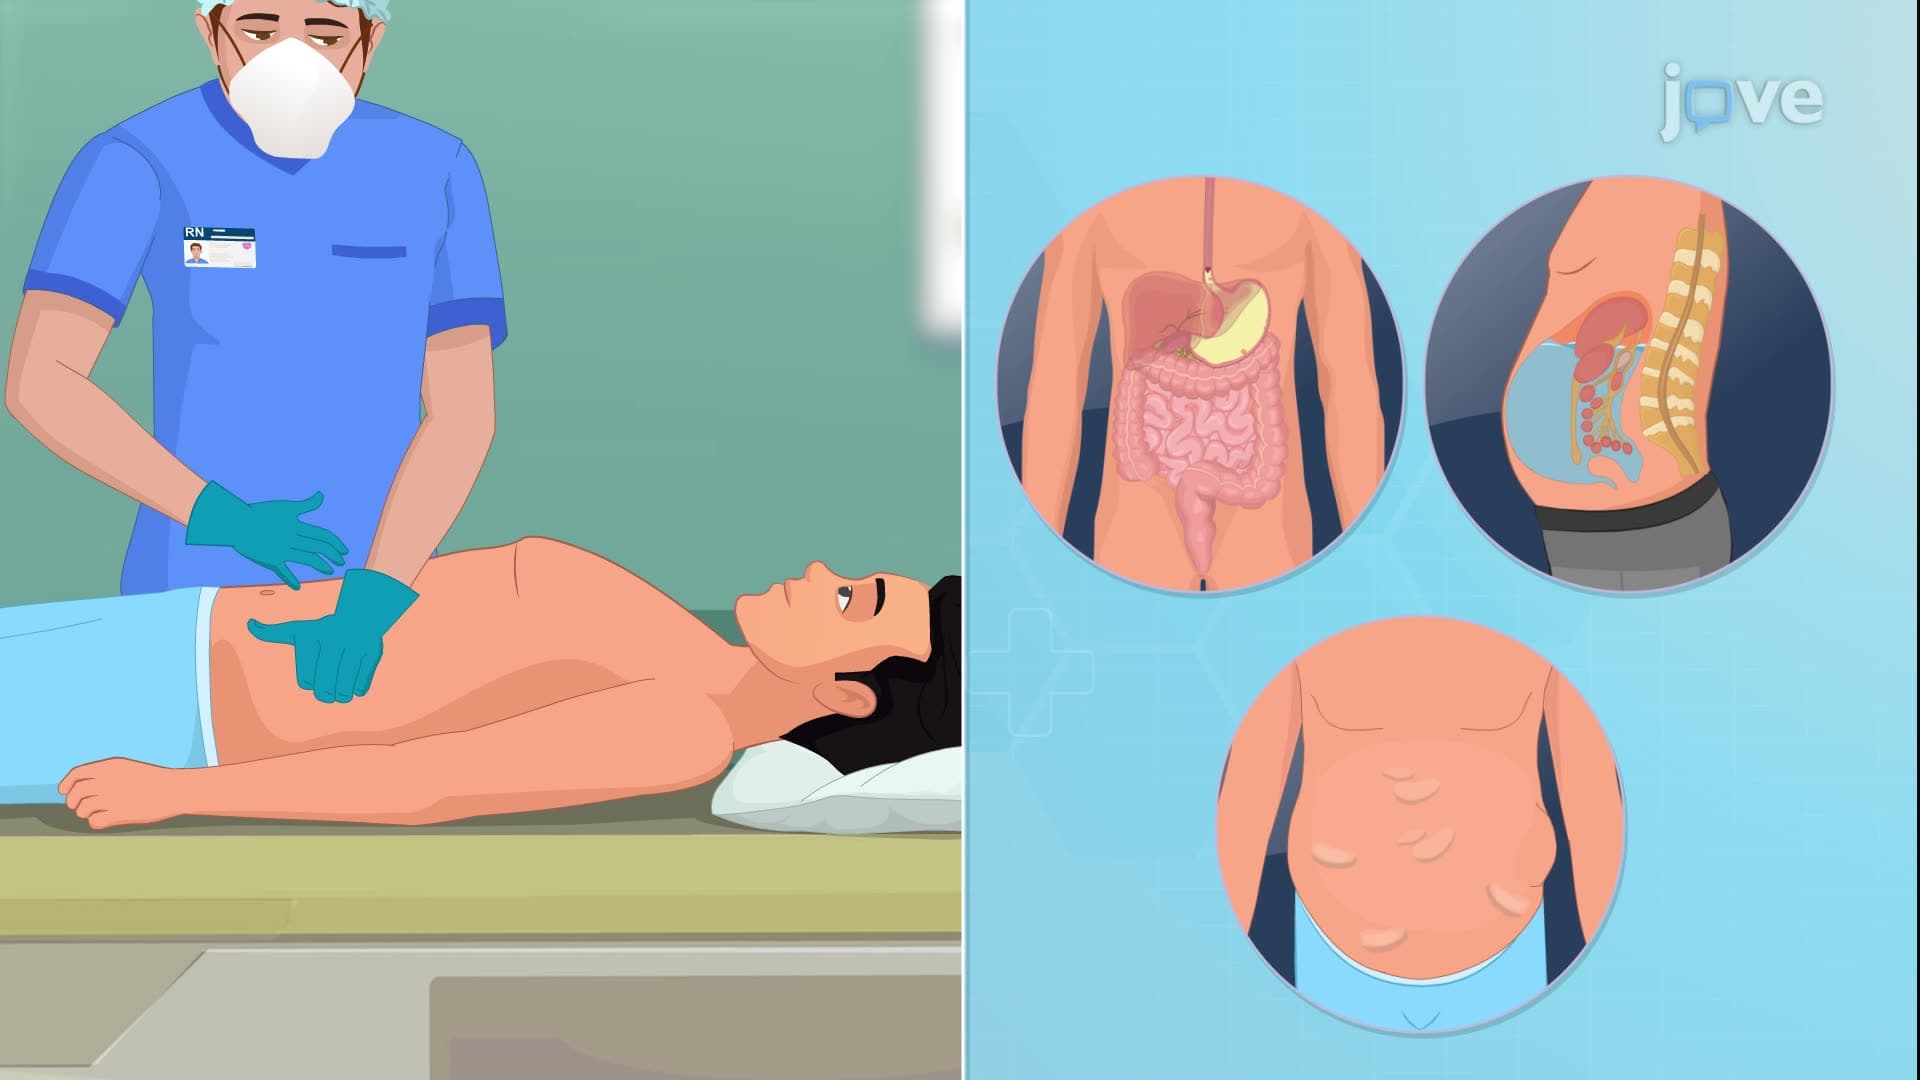
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection.
 01:18
Assessment of the Abdomen II: Percussion
Percussion
Percussion is an essential...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...