Related Experiment Video
Updated: Aug 19, 2026
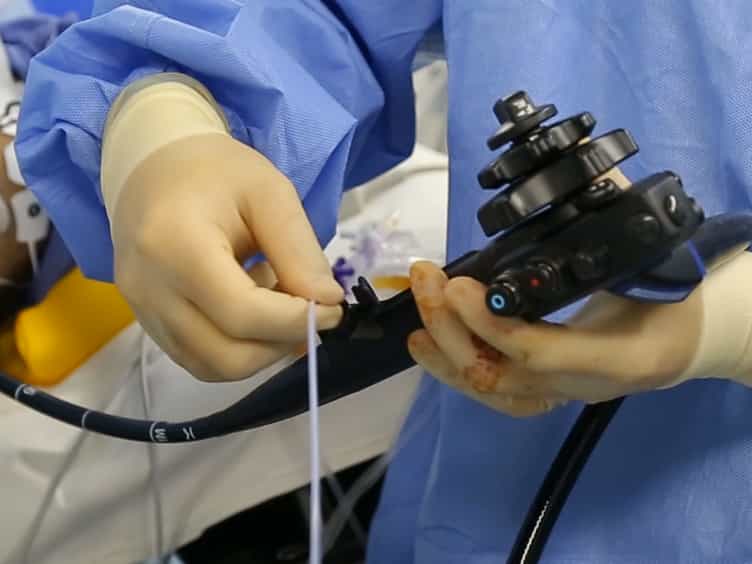

Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Pre-, intra- and postoperative staging of gastric carcinoma and clinical outcome
W Schweizer1, A Reinhart, H E Wagner
1Department of Visceral and Transplantation Surgery, University of Berne, Switzerland.

Background:
We compared preoperative (combined clinical and radiological staging and endoscopical Borrmann classification), intraoperative (by the surgeon: curative/palliative; R0/R1/R2-resection; intraoperative stage I to IV) and postoperative staging including histological results (pTNM) in respect of resectability and prognosis.
Methods:
All patients with adenocarcinoma of the stomach were prospectively and consecutively included in the study protocol and were staged during the hospitalisation by the different specialists. Out of 215 patients with malignant tumors of the stomach, 153 were finally evaluated for the study. We excluded 62 patients with other malignancies or with a follow up of less than 6 months. Preoperative endoscopic Borrmann classification was done by the gastroenterologist, preoperative TNM-classification by the radiologist and surgeon, intraoperative classification by the surgeon and postoperative classification by the pathologist. All results were immediately described in the protocol. Follow-up and survival curves were performed by the Regional Tumor Registry and statistics by the Statistical Department of the University using Kaplan-Meier survival curves and Log-Rank and Wilcoxon Test for significance.
Results:
Preoperative staging was unreliable and there was no relationship between preoperative and postoperative staging nor survival. In opposite intra- and postoperative staging correlated significantly between the different groups and with survival (p < 0.001).
Conclusions:
As long as preoperative staging systems are not improved (which may be in the future the case with endosonography), all operable patients with gastric carcinoma should undergo a laparotomy or laparoscopy, because only intraoperative evaluation of the surgeon allows a decision on a possible curative resection. Patients with stages I-III should be resected radically with complete dissection of lymph node compartments 1 and 2. This policy is justified especially in view of a minimal hospital mortality (3%).
More Related Videos
 10:28
Gene Regulation and Targeted Therapy in Gastric Cancer Peritoneal Metastasis: Radiological Findings from Dual Energy CT and PET/CT
Published on: January 22, 2018
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024