Related Experiment Video
Updated: Aug 6, 2026


A Modified Two Kidney One Clip Mouse Model of Renin Regulation in Renal Artery Stenosis
Published on: October 26, 2020
Gastrin processing and secretion in patients with end-stage renal failure
G D Ciccotosto1, J K Dawborn, K J Hardy
1University of Melbourne, Department of Surgery, Victoria, Australia.

Abstract:
Gastrin circulates at higher than normal concentrations in patients with end-stage renal failure (ESRF). However, it remains unclear which forms of gastrin are elevated and whether there is also an alteration in the secretory profile after stimulation. In the present study all processed and partially processed forms of circulating gastrin were measured in plasma before and after meal stimulation in ESRF patients and control subjects. Since Helicobacter pylori (HP) infection affects gastrin secretion, HP status was determined. Fasting gastrin-amide (36 +/- 8 pmol/L), gastrin-Gly (55 +/- 16 pmol/L), and total gastrin (218 +/- 32 pmol/L) measured in ESRF/HP-patients were all significantly greater than those in the control group (10 +/- 1, 15 +/- 3, and 17 +/- 2 pmol/L, respectively; P < 0.01). Plasma gastrin-amide (126 +/- 67 pmol/L) and total gastrin (397 +/- 164 pmol/L) were highest in the ESRF/HP+ patients. The proportion of nonamidated gastrin products was 4-fold higher in ESRF patients than in control subjects, suggesting structure-specific changes in gastrin secretion and metabolism, and this was confirmed by chromatography. The meal-stimulated increments in control/HP- and ESRF/HP-groups were similar. However, the ESRF/HP+ group had a markedly potentiated gastrin response. Fasting plasma somatostatin, an inhibitor of gastrin secretion, was also measured and was significantly lower in the ESRF patients than that in the control group. These studies show that the hypergastrinemia associated with renal failure has been underestimated. This is because only amidated products were measured. The potentiated gastrin meal response in ESRF attributed previously to changes in gastrin metabolism are in part explained by the effect of HP infection. The observed diminished somatostatin response suggests that the increase in circulating gastrin in ESRF is the result of loss of inhibition of secretion as well as decreased metabolism. As both amidated and nonamidated gastrin are now considered to have trophic and secretory effects, these findings may explain the gastrointestinal tract hypertrophy often associated with ESRF.


Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:17
Factors Affecting Renal Clearance: Renal Impairment
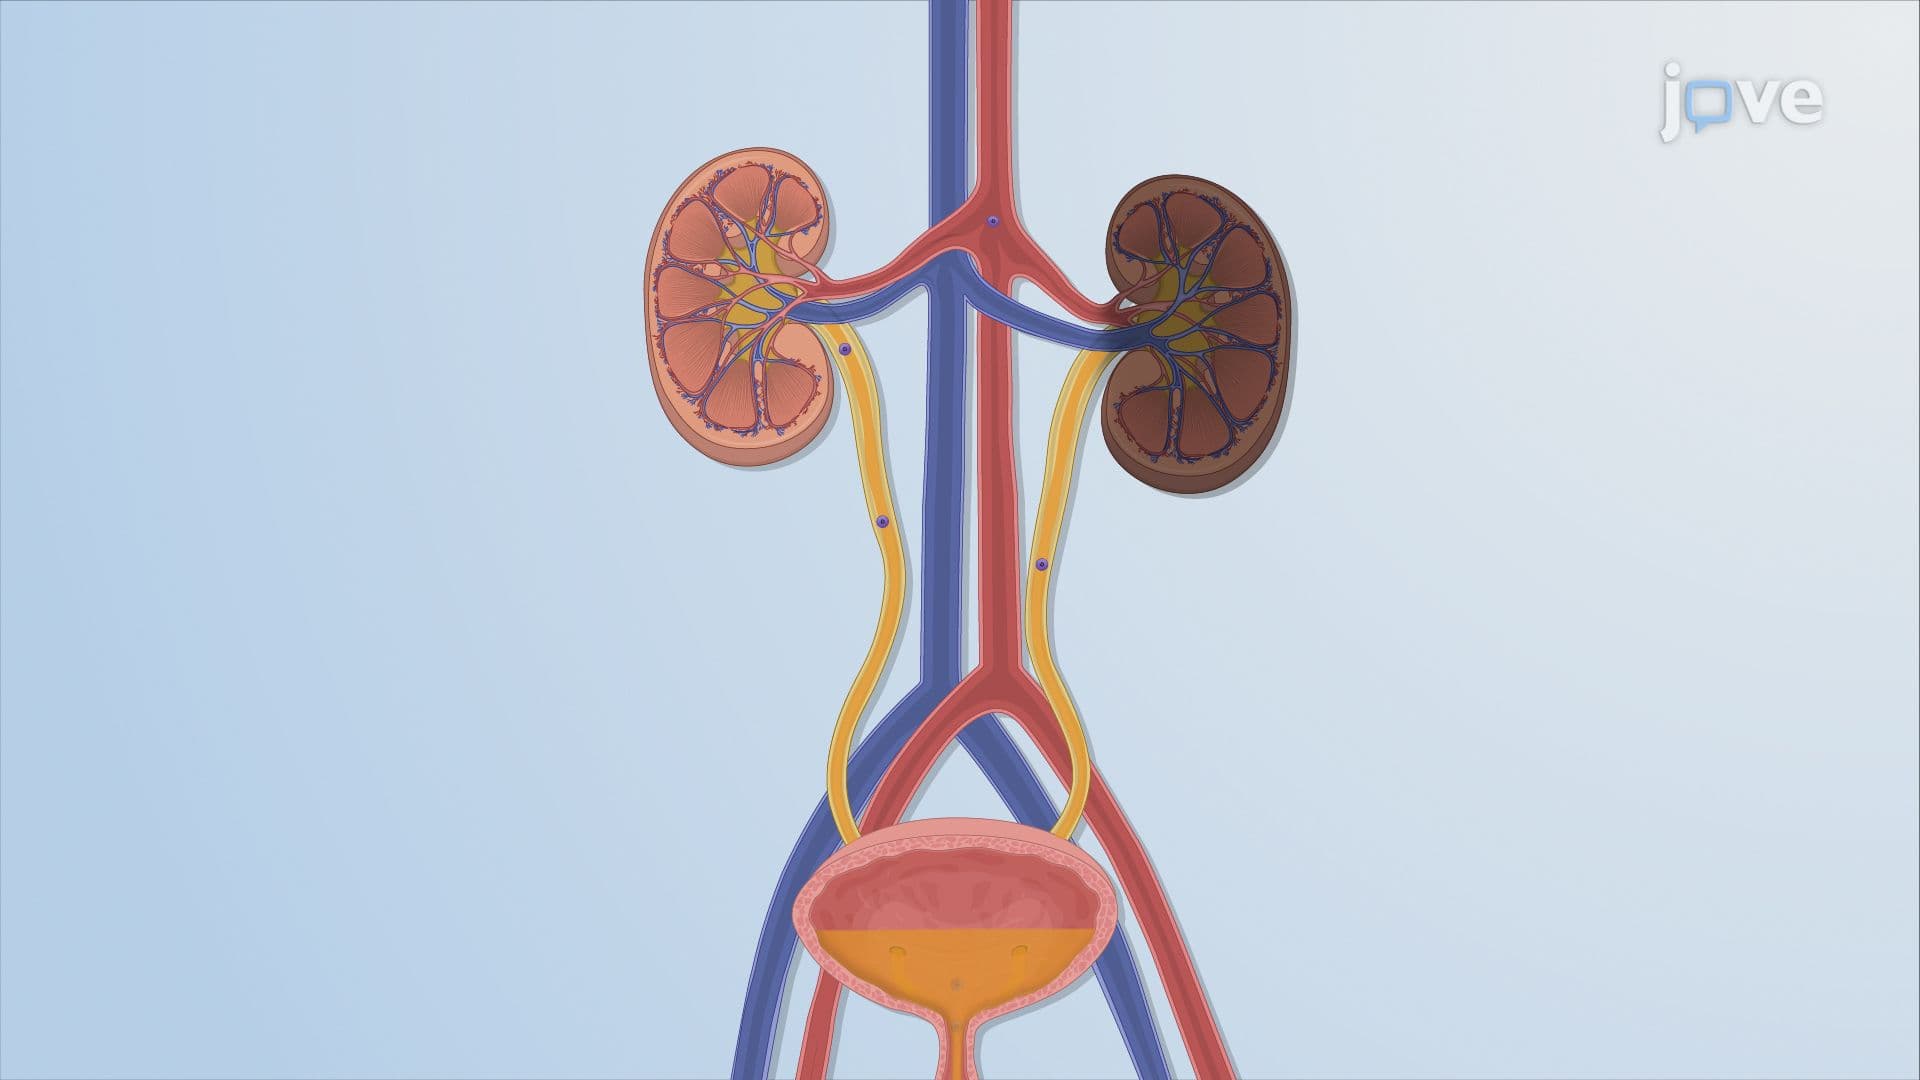
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:26
Gastritis II: Pathophysiology