Related Experiment Video
Updated: Jul 30, 2026

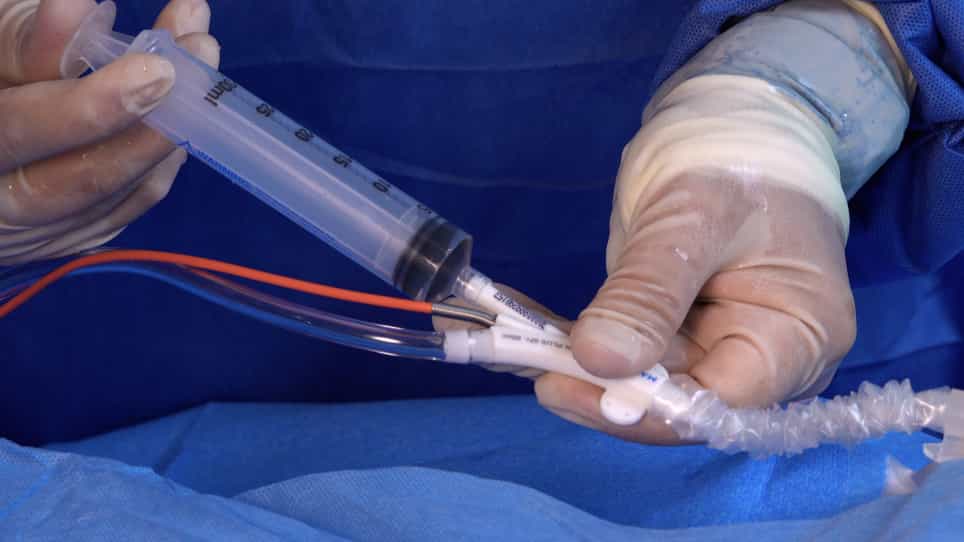
Balloon-based Injury to Induce Myointimal Hyperplasia in the Mouse Abdominal Aorta
Published on: February 7, 2018
Prospective evaluation of factors associated with intraaortic balloon rupture
J J Patel1, C Kopistansky, B Boston
1Department of Medicine, Hahnemann University Hospital, Philadelphia, Pennsylvania 19102-1192, USA.

The authors undertook a prospective analysis of all intraaortic balloon catheter (IAB) insertions at Hahnemann University Hospital during an 18 month period. Attention was directed to balloon rupture and factors associated with this complication. A total of 384 insertions were attempted in 363 patients: 19 patients (5.2%) experienced balloon rupture. The mean time to rupture was 2.1 +/- 3.3 days (range 0-15 days). All ruptured IAB catheters were removed percutaneously without subsequent complications. Ten balloons were subjected to leak testing and scanning electron microscopy. All but one rupture appeared to be the result of balloon abrasion against atherosclerotic plaque. The puncture site occurred at variable distances from the proximal end of the balloon at 9.4 +/- 8.3 cm. Comparison of patients with and without balloon rupture revealed several significant (p < 0.04) differences by univariate analysis (Table 1). No procedure related variables (IAB catheter size 9 versus 11 Fr, sheathless insertion, duration of counterpulsation) were associated with rupture. Stepwise logistic regression analysis revealed body surface area as the only independent predictor of balloon rupture (p = 0.007). Intraaortic balloon rupture with 40 cc balloons, is directly related to the size of the patient. Evaluation of smaller balloons in patients with body surface area < or = 1.8 m2 appears warranted to minimize IAB rupture.
The authors undertook a prospective analysis of all intraaortic balloon catheter (IAB) insertions at Hahnemann University Hospital during an 18 month period. Attention was directed to balloon rupture and factors associated with this complication. A total of 384 insertions were attempted in 363 patients: 19 patients (5.2%) experienced balloon rupture. The mean time to rupture was 2.1 +/- 3.3 days (range 0-15 days). All ruptured IAB catheters were removed percutaneously without subsequent complications. Ten balloons were subjected to leak testing and scanning electron microscopy. All but one rupture appeared to be the result of balloon abrasion against atherosclerotic plaque. The puncture site occurred at variable distances from the proximal end of the balloon at 9.4 +/- 8.3 cm. Comparison of patients with and without balloon rupture revealed several significant (p < 0.04) differences by univariate analysis (Table 1). No procedure related variables (IAB catheter size 9 versus 11 Fr, sheathless insertion, duration of counterpulsation) were associated with rupture. Stepwise logistic regression analysis revealed body surface area as the only independent predictor of balloon rupture (p = 0.007). Intraaortic balloon rupture with 40 cc balloons, is directly related to the size of the patient. Evaluation of smaller balloons in patients with body surface area < or = 1.8 m2 appears warranted to minimize IAB rupture.
Related Concept Videos
 01:30
Aneurysm I: Introduction
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management