Related Experiment Video
Updated: Jul 30, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Multiple-dose pharmacokinetics of pentoxifylline and its metabolites during renal insufficiency
C M Paap1, K S Simpson, M W Horton
1School of Pharmacy, University of Colorado, Denver 80262, USA.

Objective:
To characterize pentoxifylline (PTF) and metabolite disposition after multiple oral doses given two and three times a day to patients with renal dysfunction.
Design:
An open-label, randomized, crossover, parallel group design.
Setting:
Community-based clinical research center. PATIENT POPULATIONS: Subjects with renal function stratified based on 24-hour urinary creatine clearance (Clcr): group I = Clcr > 80 mL/min (n = 9); group II = Clcr 30-80 mL/min (n = 6); and group III = Clcr < 30 mL/min (n = 10).
Methods:
PTF 400 mg bid or tid was administered on days 1-7 and 400 mg bid or tid was given on days 14-20 with a 1-week washout. Timed blood samples were taken on days 1, 7, and 20. Blood samples were analyzed for PTF and its metabolites (M-I, M-IV, M-V) by gas-liquid chromatography.
Main Outcome Measures:
Maximum plasma concentrations (Cmax), time to maximum concentration (tmax), average steady-state plasma concentration (CavgSS), and area under the plasma concentration-time curve at steady-state (AUCSS) were determined by visual and model independent methods. ANOVA, paired t-test, and linear regression were used with significance level set at p < 0.05.
Results:
The ratio of PTF AUCSS (tid):AUCSS (bid) and M-I AUCSS (bid and tid) were not significantly different between the groups. Significant differences were found in M-IV and M-V Cmax, AUCSS, CavgSS, and AUCSS ratios (M-IV:PTF and M-V:PTF) between renal function groups (p < 0.05 for all). A change in dosage regimen from tid to bid resulted in significant changes in M-IV and M-V CavgSS for subjects with normal renal function and in those with moderate dysfunction, although not in subjects with severe renal dysfunction.
Conclusions:
Renal dysfunction did not cause significant accumulations of PTF or M-I after multiple bid and tid dosing, however, M-IV and M-V had significant accumulation in patients with renal impairment. Dosage reduction to 400 mg bid for patients with moderate renal impairment and 200-400 mg/d for severe renal impairment, as well as close clinical monitoring, seem prudent until the complex pharmacologic interactions of PTF and its metabolites can be further delineated.


Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:23
Nonlinear Pharmacokinetics: Dependence of Elimination Half-Life and Dose Clearance
A study on guinea pigs examined the...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
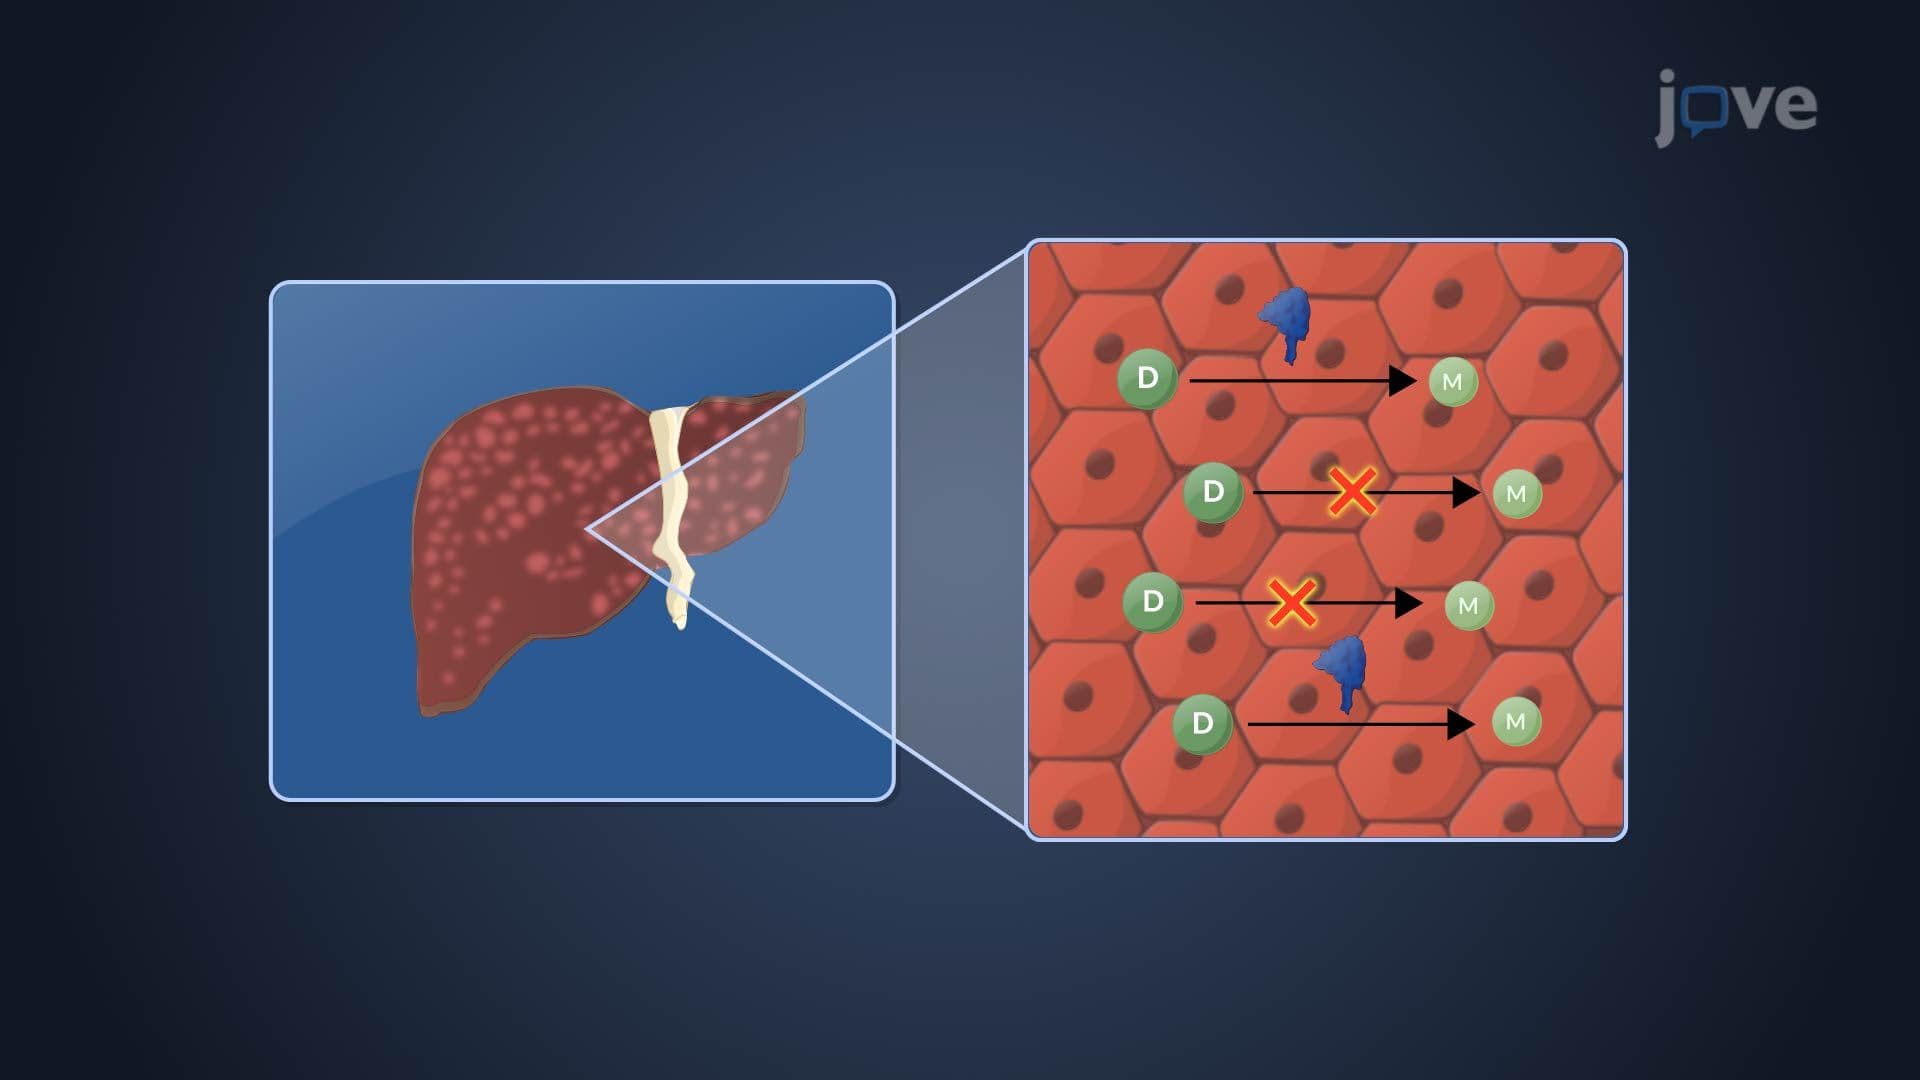
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant