Related Experiment Video
Updated: Jul 29, 2026
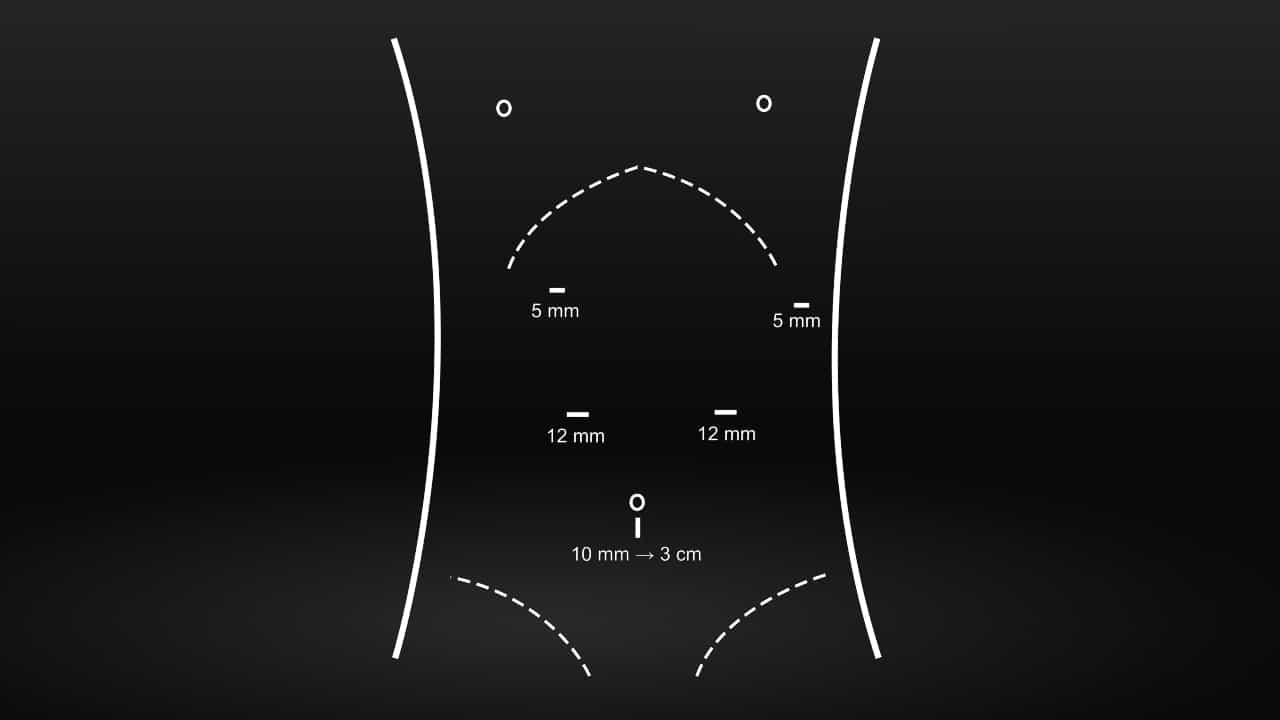

Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Management of esophageal varices in children by endoscopic variceal ligation
M R Price1, K H Sartorelli, F M Karrer
1Department of Surgery, University of Colorado School of Medicine, Children's Hospital, Denver 80218, USA.

Abstract:
Endoscopic variceal sclerotherapy (EVS) has been considered the mainstay of therapy for bleeding esophageal varices in adults. However, recent data have shown that endoscopic variceal ligation (EVL) is just as efficacious and has fewer complications than EVS. Although there are many reports concerning EVL in adults, only a few studies have been done in children. This report describes experience with EVL in 22 children with esophageal variceal hemorrhage. Eighty-seven EVL procedures were performed during a 9-year period in 22 children. The causes of portal hypertension were biliary atresia (10), portal vein thrombosis (8), chronic active hepatitis (1), cirrhosis secondary to cystic fibrosis (2), and primary sclerosing cholangitis (1). The age range at the onset of variceal bleeding was 8 months to 19 years. Twelve patients had EVS before EVL treatment was begun. Distal esophageal varices (one to four per session) were mechanically ligated using an elastic band ligature device attached to a flexible endoscope. The aim of therapy was obliteration of distal esophageal varices by EVL, every 2 to 4 weeks, until eradication. Subsequent EVL was dictated by the status of the varices. Outcome was assessed with respect to survival, rebleeding, status of varices, and complications. The patients underwent a mean of four sessions of EVL (range, one to eight). Four patients subsequently underwent liver transplantation. Of the 18 patients remaining (average follow-up period, 5.3 years), 12 had their varices eradicated (average of four EVL sessions), four are still in treatment, one has not been evaluated in the past 4 years, and one died of liver failure. Complications included bleeding between sessions (6 patients), cervical esophageal perforation (1 patient), and transient fever (2 patients). No child has experienced symptoms of esophageal stenosis or gastroesophageal reflux. Two patients died of liver disease, unrelated to bleeding from portal hypertension. EVL is effective in controlling variceal hemorrhage in children with portal hypertension, regardless of etiology. The complication rate is low, and EVL is an acceptable and perhaps preferable alternative to EVS in children with esophageal varices.


Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care