Rheumatoid arthritis complicated by pachy- and leptomeningeal rheumatoid nodule-like granulomas and systemic

N Kamio1, S Kuramochi, R J Wang

  • 1Department of Pathology, Keio University School of Medicine, Tokyo, Japan.

Related Concept Videos

Rheumatic Heart Disease I: Introduction01:23

Rheumatic Heart Disease I: Introduction

Rheumatic heart disease or RHD is a chronic condition that results from rheumatic fever, causing permanent damage to the heart valves.Etiology and Risk FactorsIt primarily arises from rheumatic fever, an inflammatory disease that can develop after untreated or inadequately treated group A streptococcal (GAS) pharyngitis. Streptococcus spreads through direct contact with oral or respiratory secretions. While the bacteria are the causative agents, factors like malnutrition, overcrowding, poor...
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies01:22

Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
The key clinical manifestations of Rheumatic heart disease (RHD) include several distinct cardiac symptoms.Carditis, a hallmark of acute rheumatic fever, involves inflammation of the heart's endocardium, myocardium, and pericardium. Chronic RHD often results from recurrent episodes of carditis. Its symptoms include the following:Murmurs are caused by valvular damage, especially to the mitral and aortic valves. Mitral stenosis or regurgitation is common, with characteristic heart murmurs...
Bacterial Meningitis I: Introduction01:22

Bacterial Meningitis I: Introduction

Bacterial meningitis is a severe, life-threatening inflammation of the meninges, particularly the pia mater and arachnoid mater, affecting the subarachnoid space, ventricles, and cerebrospinal fluid (CSF). If untreated, it can lead to significant neurological complications or death.Causative AgentsCommon pathogens vary with age and immune status. In adults, major organisms include Streptococcus pneumoniae, Neisseria meningitidis, and Haemophilus influenzae. Streptococcus agalactiae (group B...
Bacterial Meningitis II: Pathophysiology01:26

Bacterial Meningitis II: Pathophysiology

Bacterial meningitis typically begins when pathogens such as Neisseria meningitidis and Streptococcus pneumoniae colonize the nasopharynx and invade the bloodstream. This process is facilitated by bacterial virulence factors, such as polysaccharide capsules, which resist phagocytosis and complement-mediated killing. Less commonly, bacteria reach the central nervous system via contiguous spread from infections like otitis media or sinusitis, through congenital or acquired dural defects, or...
Brain Abscess l: Introduction01:26

Brain Abscess l: Introduction

A brain abscess is a focal, intracerebral infection characterized by a localized collection of pus within the brain parenchyma, resulting from microbial invasion and the body’s inflammatory response. It progresses through stages: early and late cerebritis, followed by early and late capsule formation, reflecting tissue destruction, immune response, and eventual encapsulation.Etiology and PathogenesisCausative organisms vary with source and host factors, often involving polymicrobial infections,...
Hypersensitivity Reactions: Immune-Complex Reactions01:19

Hypersensitivity Reactions: Immune-Complex Reactions

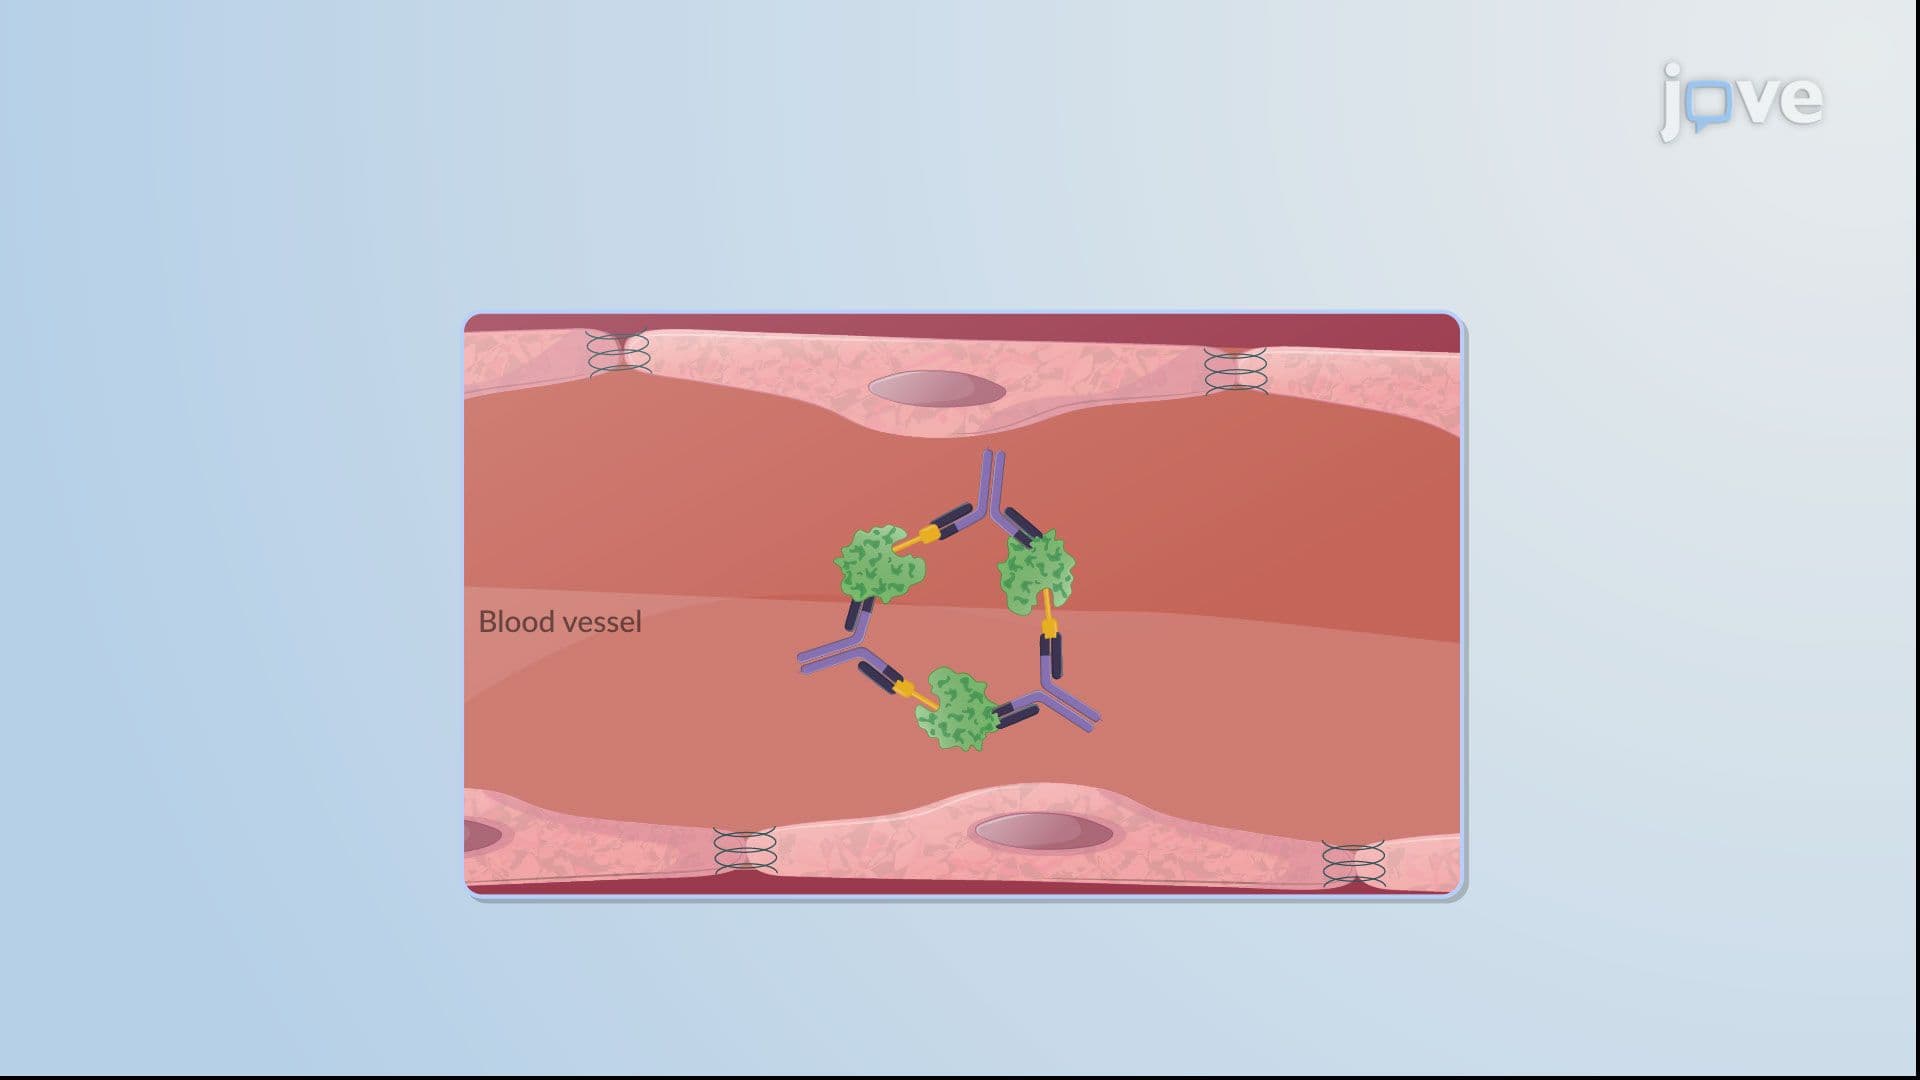
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...