Intracranial hypotension
Related Experiment Video
Updated: Nov 4, 2026

Pre-Chiasmatic, Single Injection of Autologous Blood to Induce Experimental Subarachnoid Hemorrhage in a Rat Model
Published on: June 18, 2021
1Division of Neurology, Union Memorial Hospital, Baltimore, Maryland, USA.

Insights
Intracranial hypotension (IH), characterized by low cerebrospinal fluid (CSF) pressure, often causes severe headaches. Understanding its causes and symptoms is crucial for effective diagnosis and treatment.
Area of Science:
- Neurology
- Neurosurgery
Background:
- Intracranial hypotension (IH) is defined by cerebrospinal fluid (CSF) pressure ≤ 60 mm H2O without prior dural puncture.
- It disproportionately affects women (3:1 ratio) and presents with orthostatic headache as a primary symptom.
- Associated symptoms include visual disturbances, auditory issues, and potential visual field defects upon examination.
Purpose of the Study:
- To elucidate the pathophysiology, diagnostic approaches, and management strategies for intracranial hypotension.
- To highlight the importance of neuroimaging in patients with postural headaches before lumbar puncture.
- To review the utility of radionuclide cisternography in identifying CSF fistulas.
Main Methods:
- Review of clinical presentation, postulated mechanisms (brain sagging, venous dilation, adenosine receptor activation), and diagnostic findings.
- Discussion of primary IH (occult dural leak) and secondary causes (lumbar puncture, trauma, etc.).
- Evaluation of diagnostic imaging and CSF fistula detection methods.
Main Results:
- Orthostatic headache is the hallmark symptom of IH.
- Radionuclide cisternography is highly sensitive for detecting CSF leaks.
- Neuroimaging is recommended prior to lumbar puncture in patients with suspected IH.
Conclusions:
- Intracranial hypotension encompasses diverse etiologies and clinical manifestations.
- Prompt diagnosis and appropriate management, including caffeine or epidural interventions, can alleviate symptoms.
- Further research into the underlying mechanisms and optimal treatment is warranted.
Abstract:
Intracranial hypotension (IH) is present when cerebrospinal fluid (CSF) pressure is 60mm H2O or lower and there has been no previous dural puncture. IH is more common in women than in men (3:1). Orthostatic headache is the cardinal symptom. Visual, auditory, and other symptoms occur. Postulated mechanisms include sagging of the brain, dilation of intracranial veins, and activation of adenosine receptors. Examination may disclose visual field defects. The condition may be primary (probably related to an occult dural leak) or secondary to many causes that include lumbar puncture, trauma, pneumonectomy, diabetic coma, and uremia. Patients with postural headache should undergo neuroimaging prior to lumbar puncture. Radionuclide cisternography is the most sensitive means of demonstrating a CSF fistula. Severe, intractable headache associated with IH may respond to intravenous of oral caffeine. An epidural blood patch and epidural infusion of normal saline are treatment measures for symptoms of IH that follow lumbar puncture.


Related Concept Videos
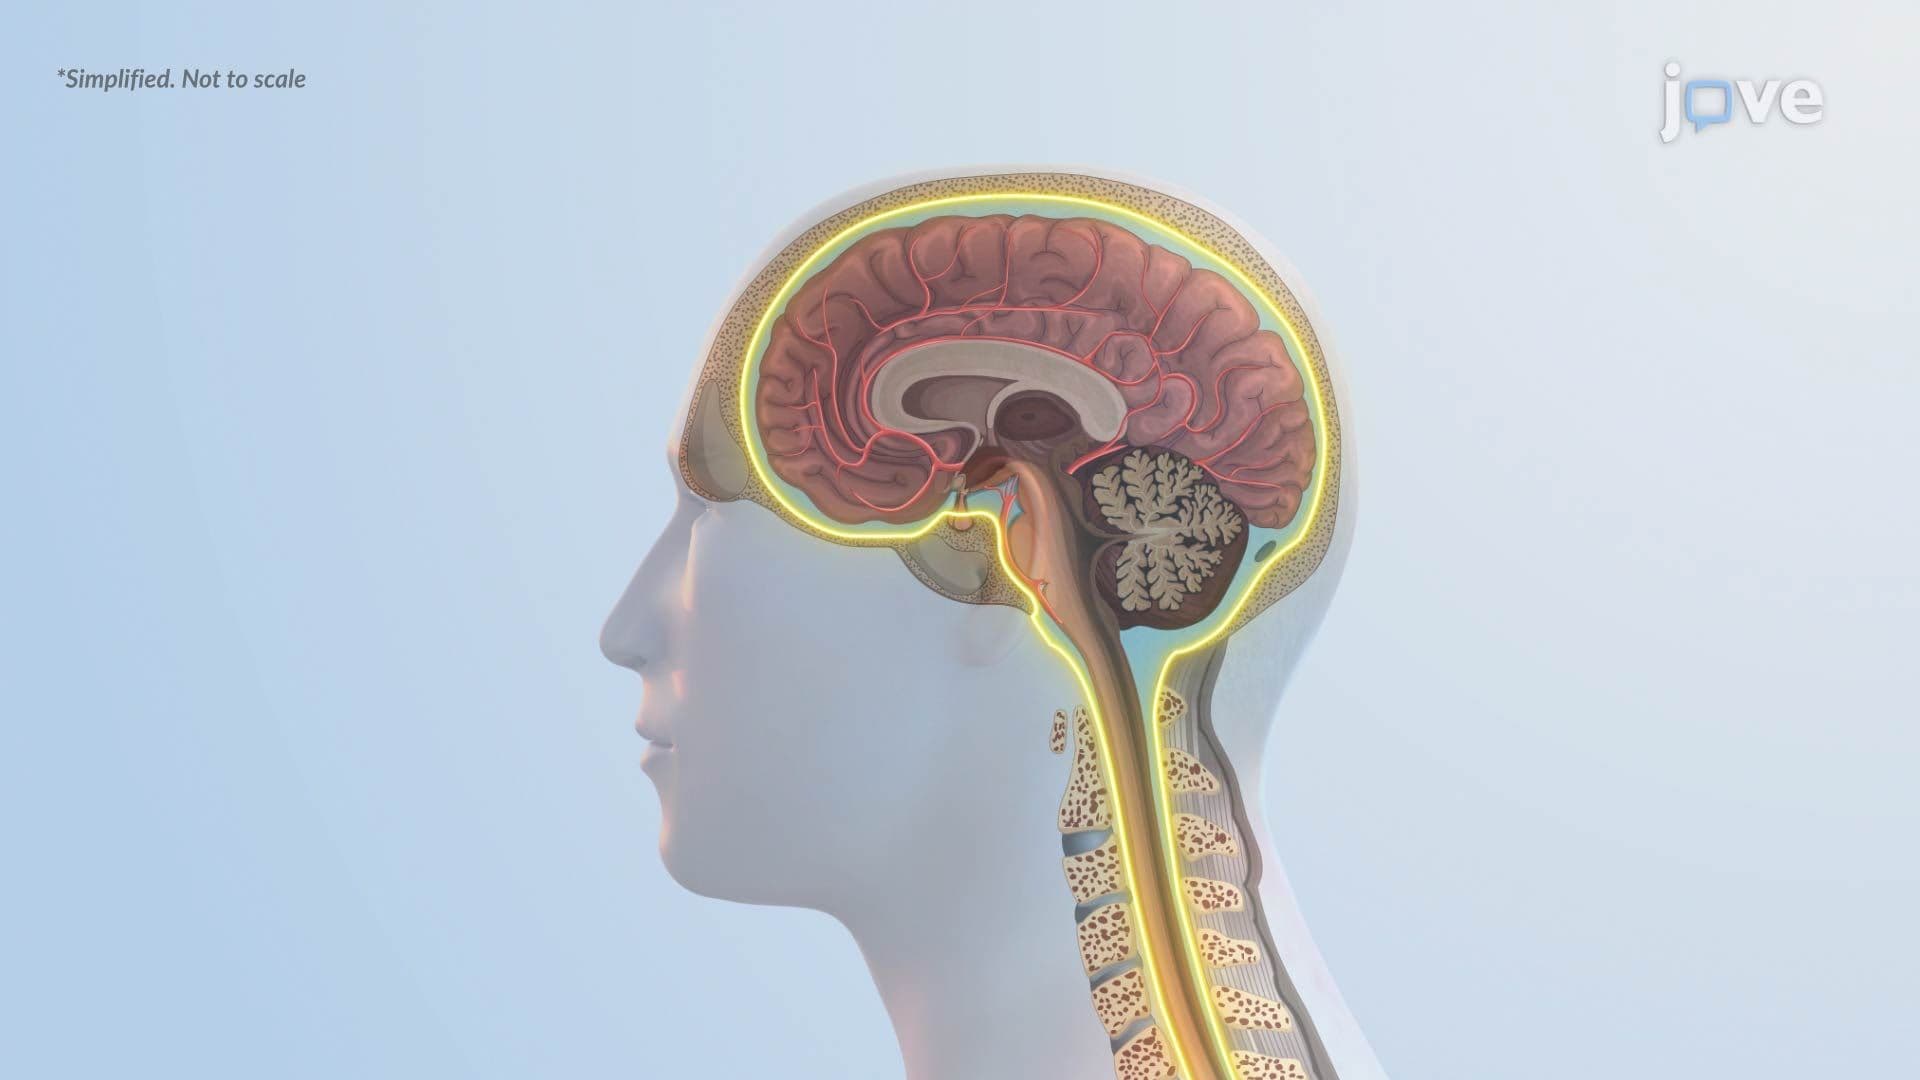 01:14
Increased Intracranial Pressure l: Introduction
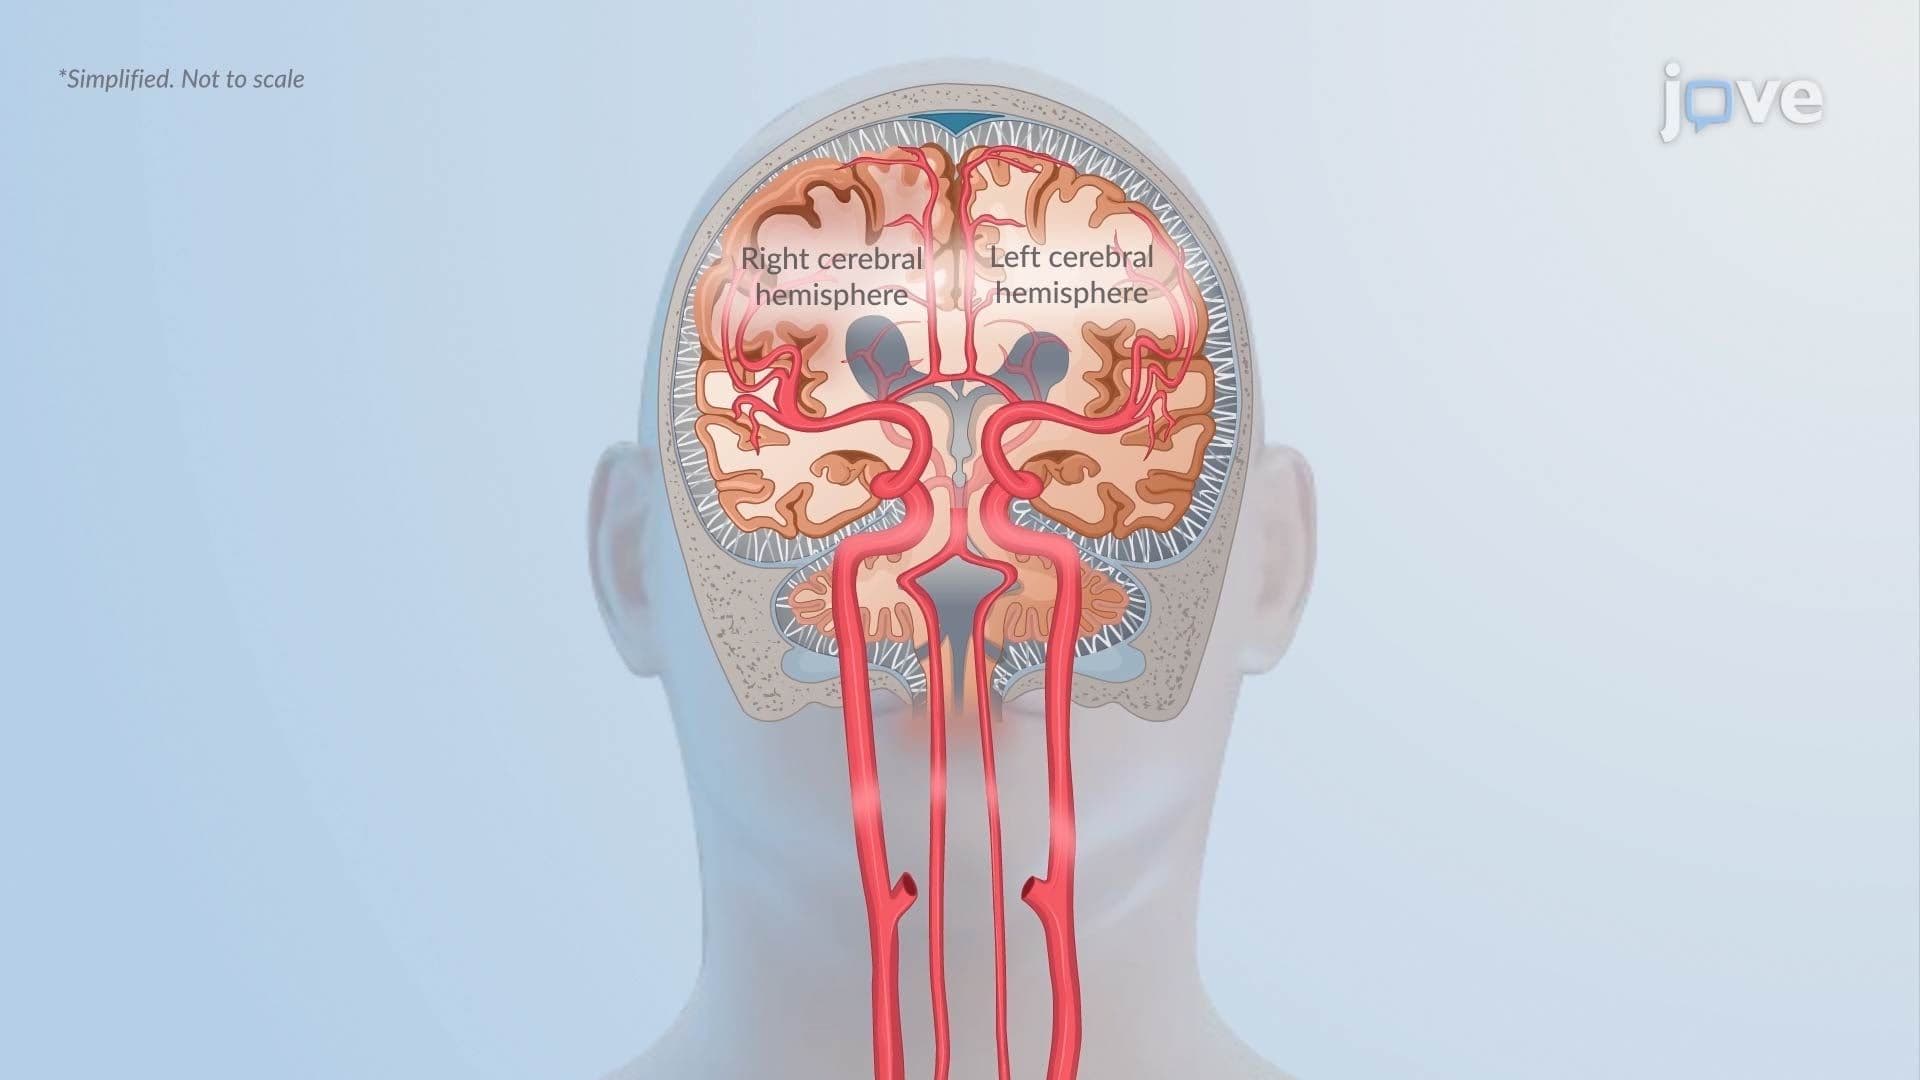 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart beats)...
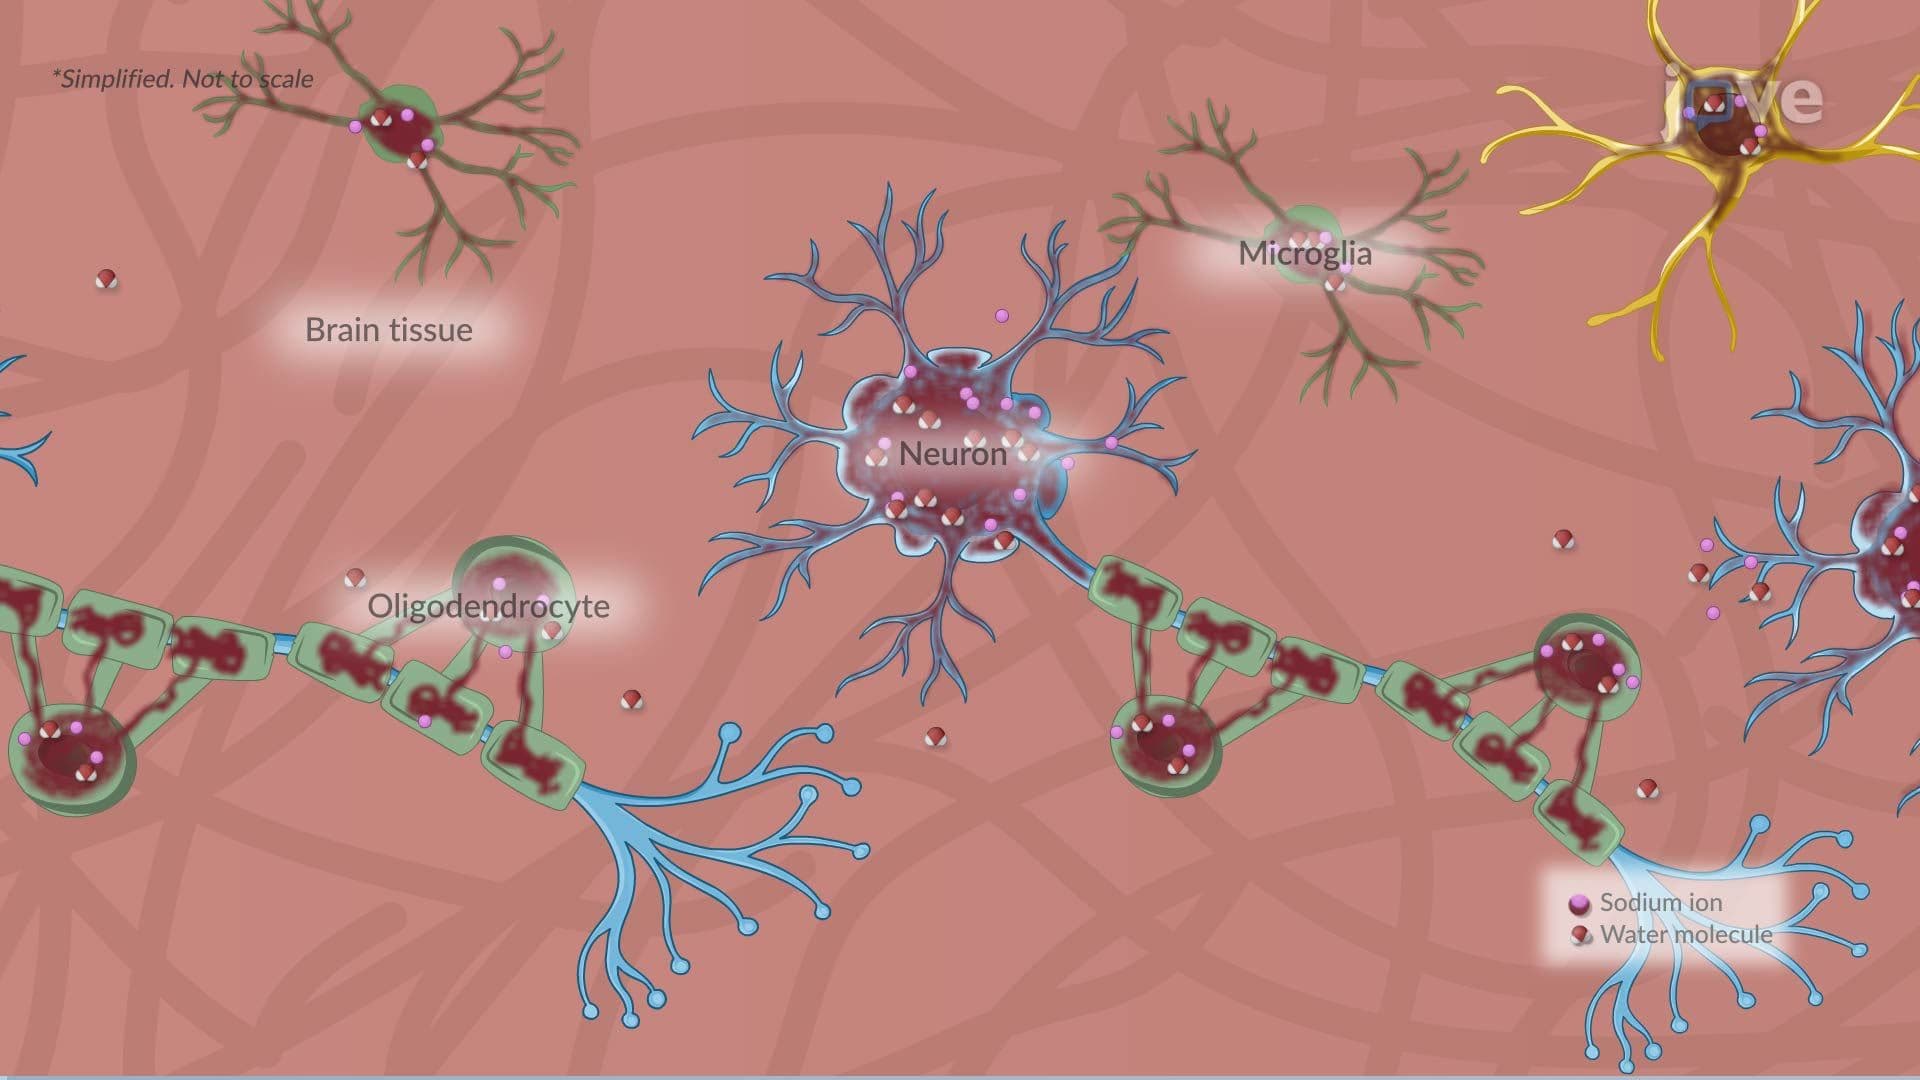 01:19
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
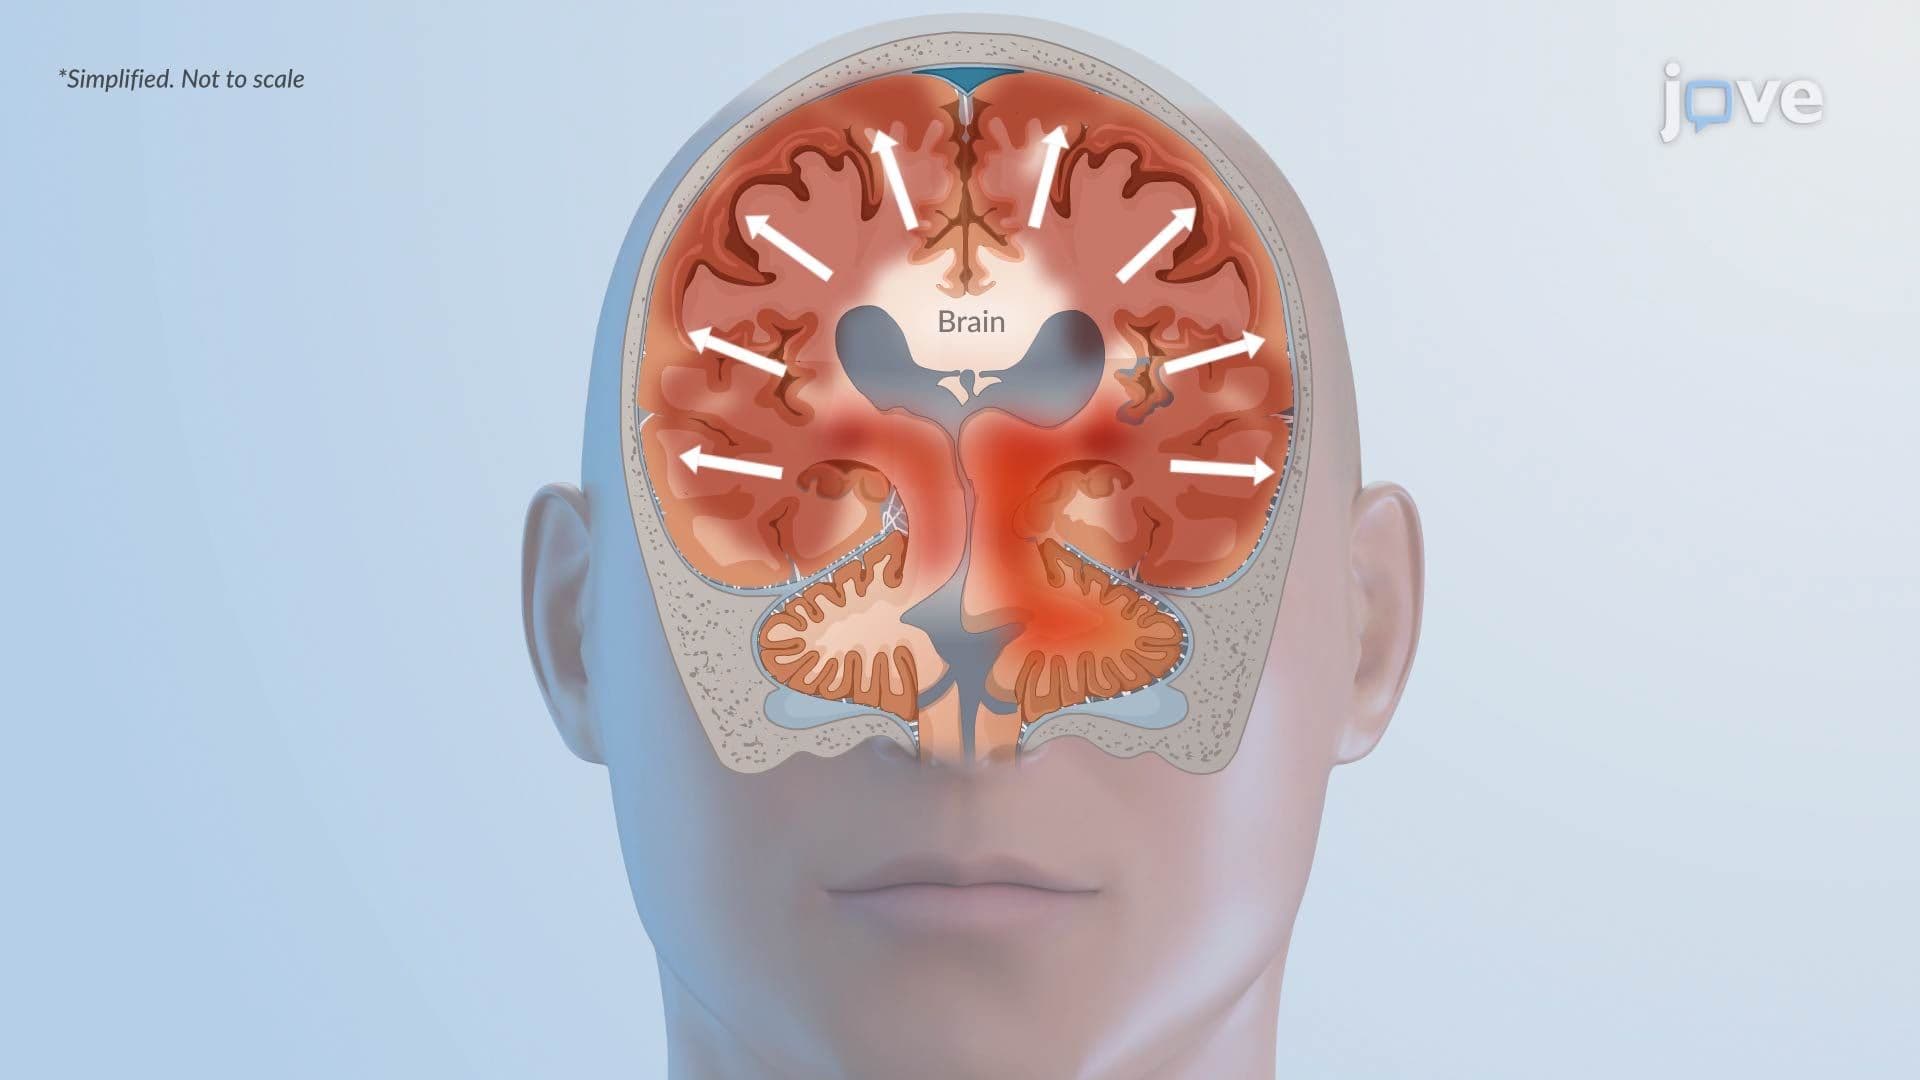 01:21
Cytotoxic Edema: Pathophysiology