Weaning and extubation in the intensive care unit. Clinical or index-driven approach?
Related Experiment Video
Updated: Nov 4, 2026

A Structured Approach to Extubation in Mechanically Ventilated Rats
Published on: July 18, 2025
E A Leitch1, J L Moran, B Grealy
1Intensive Care Unit, Queen Elizabeth Hospital, Wodville, Australia.

Objective:
To assess the outcome of a clinical judgement-based approach to weaning and extubation and to adduce the predictive accuracy of various mechanical respiratory indices measured in parallel.
Design:
Prospective study.
Setting:
Multidisciplinary intensive care unit at a university teaching hospital.
Patients:
163 consecutive mechanically ventilated patients, excluding tracheotomy, for weaning trial and extubation.
Interventions:
Using bedside clinical assessment, aided by arterial gas analysis, patients were weaned from mechanical ventilation to spontaneous ventilation via to continuous positive airway pressure (CPAP) circuit (with pressure support) of a microprocessor-controlled ventilator. Extubation occurred from the CPAP circuit at 7 cmH2O pressure support, fractional inspired oxygen (FIO2) < or = 0.5 and CPAP level of < or = 5 cmH2O, such that the partial pressure of oxygen in arterial blood (PaO2) was > or = 65 mmHg. Before extubation, observation for a 1-h (T0 and T60) trial period allowed measurement of vital capacity (VC), expired minute volume (VE), respiratory rate/tidal volume (f/VT) and maximal inspiratory pressure (MIP) using a one-way valve technique over 25 s.
Measurements And Main Results:
Over 7 months, 163 patients (62 females and 101 males; mean (SD) age 64(15) years) were considered. There were 91 surgical (18 with chronic obstructive pulmonary disease; COPD) and 72 medical (28 with COPD) patients. Ventilation was for > or = 1 day (median 5 days, range 1-31) in 115 [group I; APACHE II score 23(8)] and < or = 1 day in 48 [Group II; APACHE II score 17(6)]. Three patients (all Group I: 2 surgical, 1 medical) were reintubated within 24 h, an overall extubation failure rate of 1.8%. In group I, at T0, PaO2/FIO2 was 238(65), f/VT 50(26), MIP 44(21) cmH2O, VE 10.6(3.7) l/min, VC 13(5) ml/kg. Cardiorespiratory variables did not change significantly in either group, T0 to T60. For prediction of reintubation (n = 163), only VE (threshold > 10 l/min) and f/VT (threshold > 100) demonstrated moderate sensitivity and specificity at T60: 67 and 52% and 33 and 94%, respectively.
Conclusions:
Bedside clinical judgement of weaning and extubation produces satisfactory outcomes. As a routine, mechanical predictive indices have limited utility.
Related Concept Videos
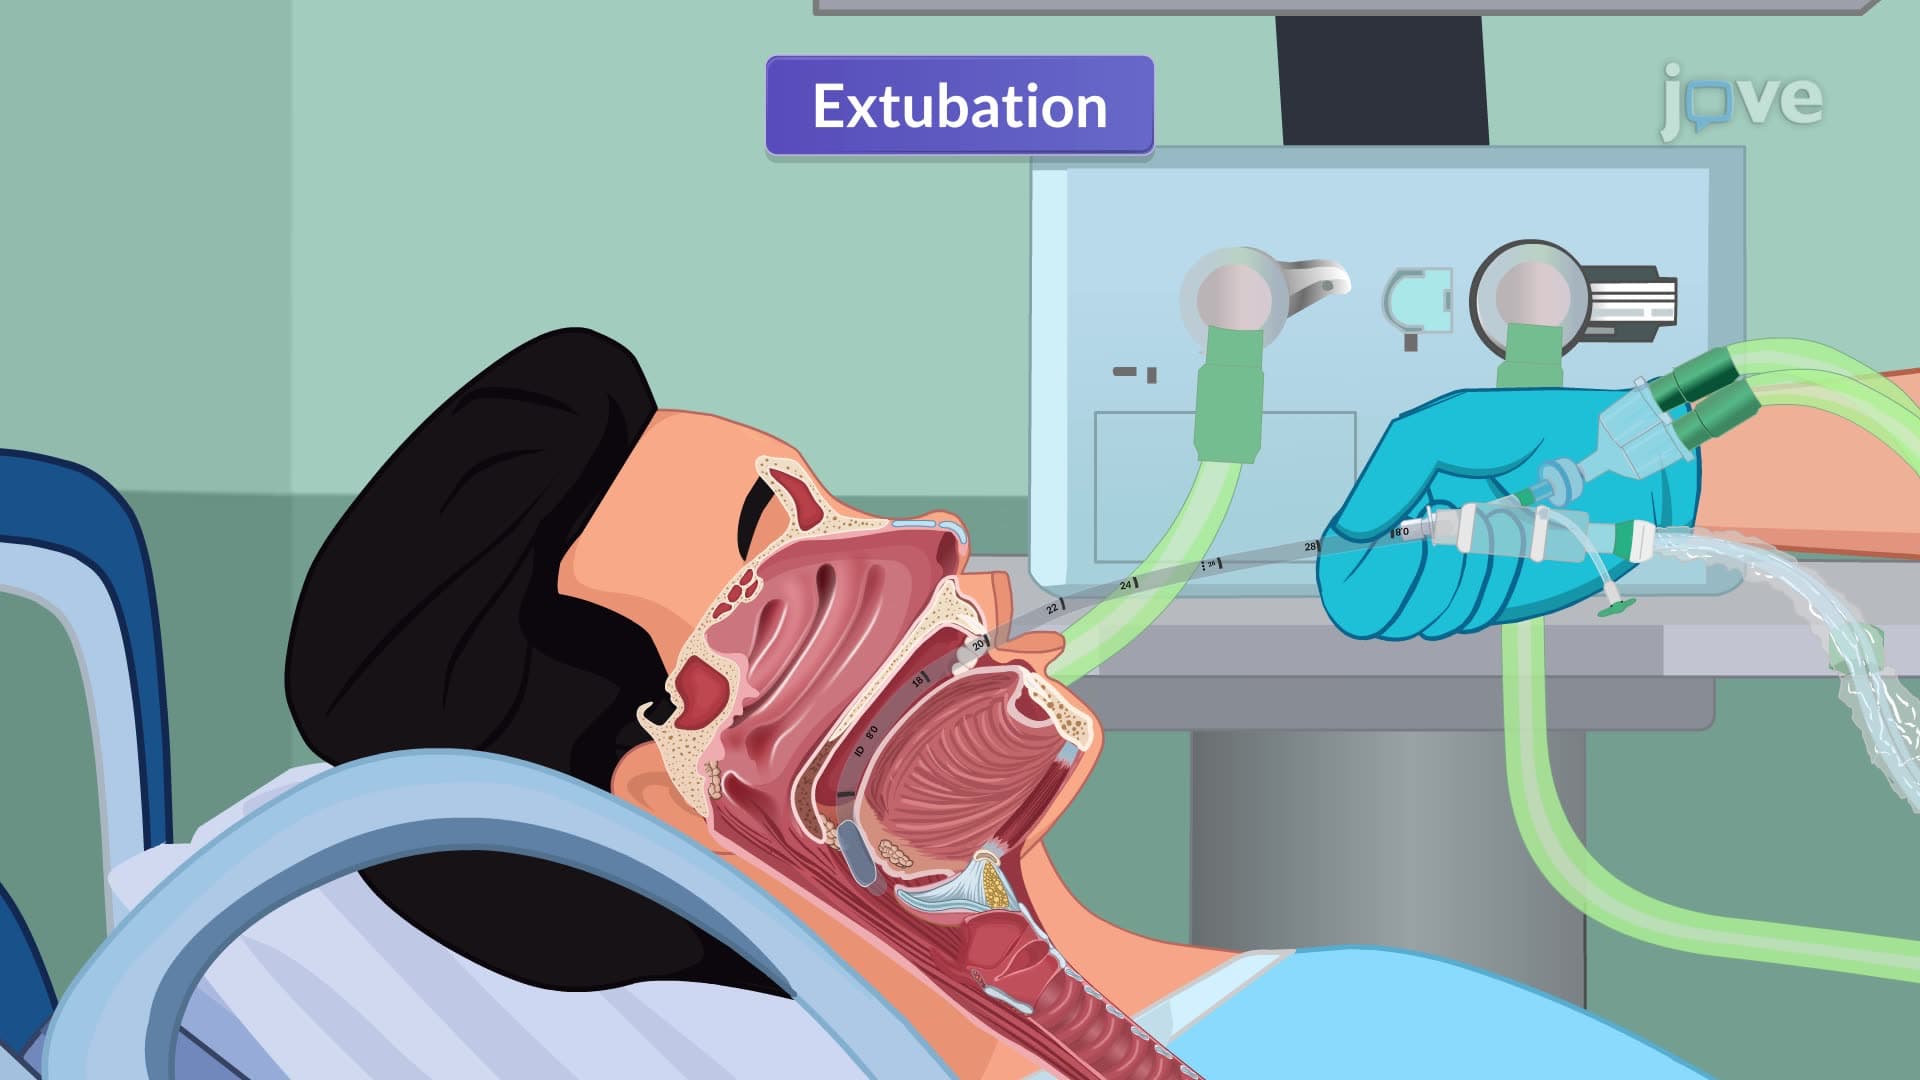 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
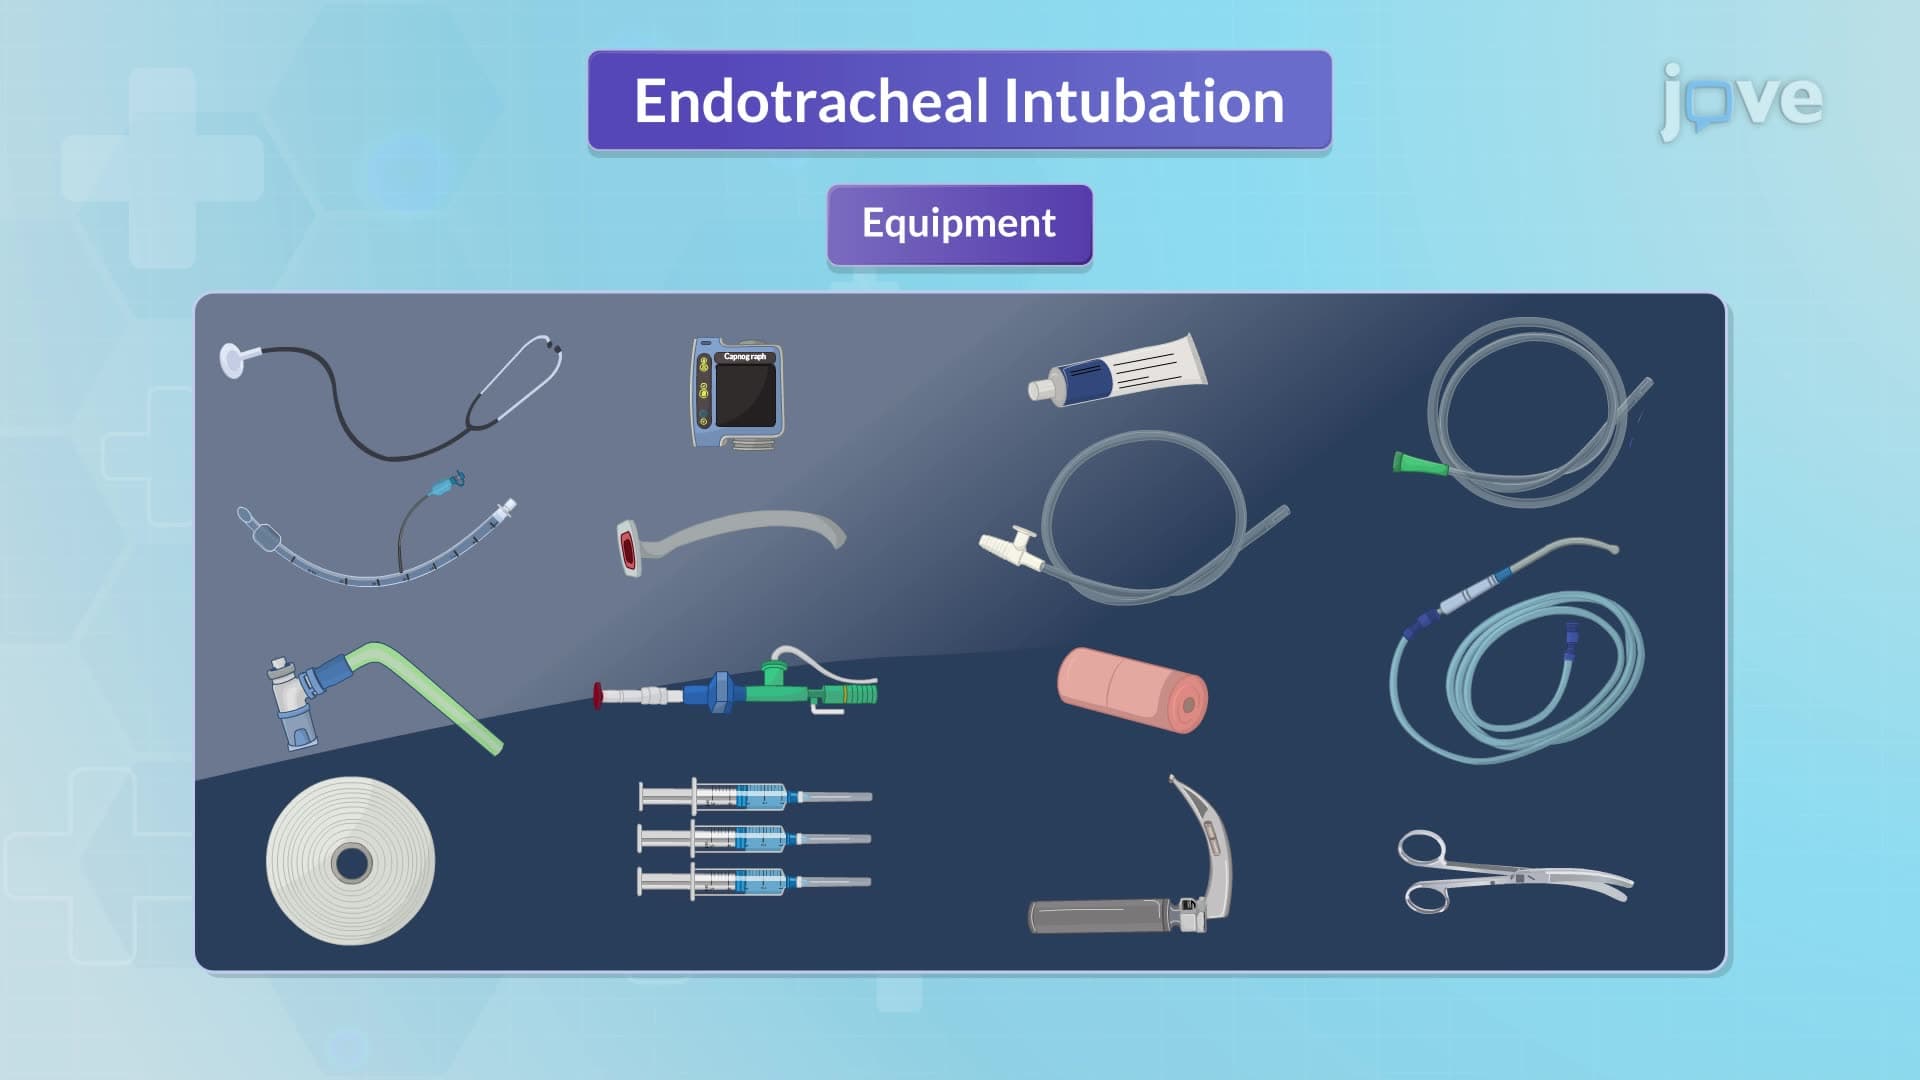 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
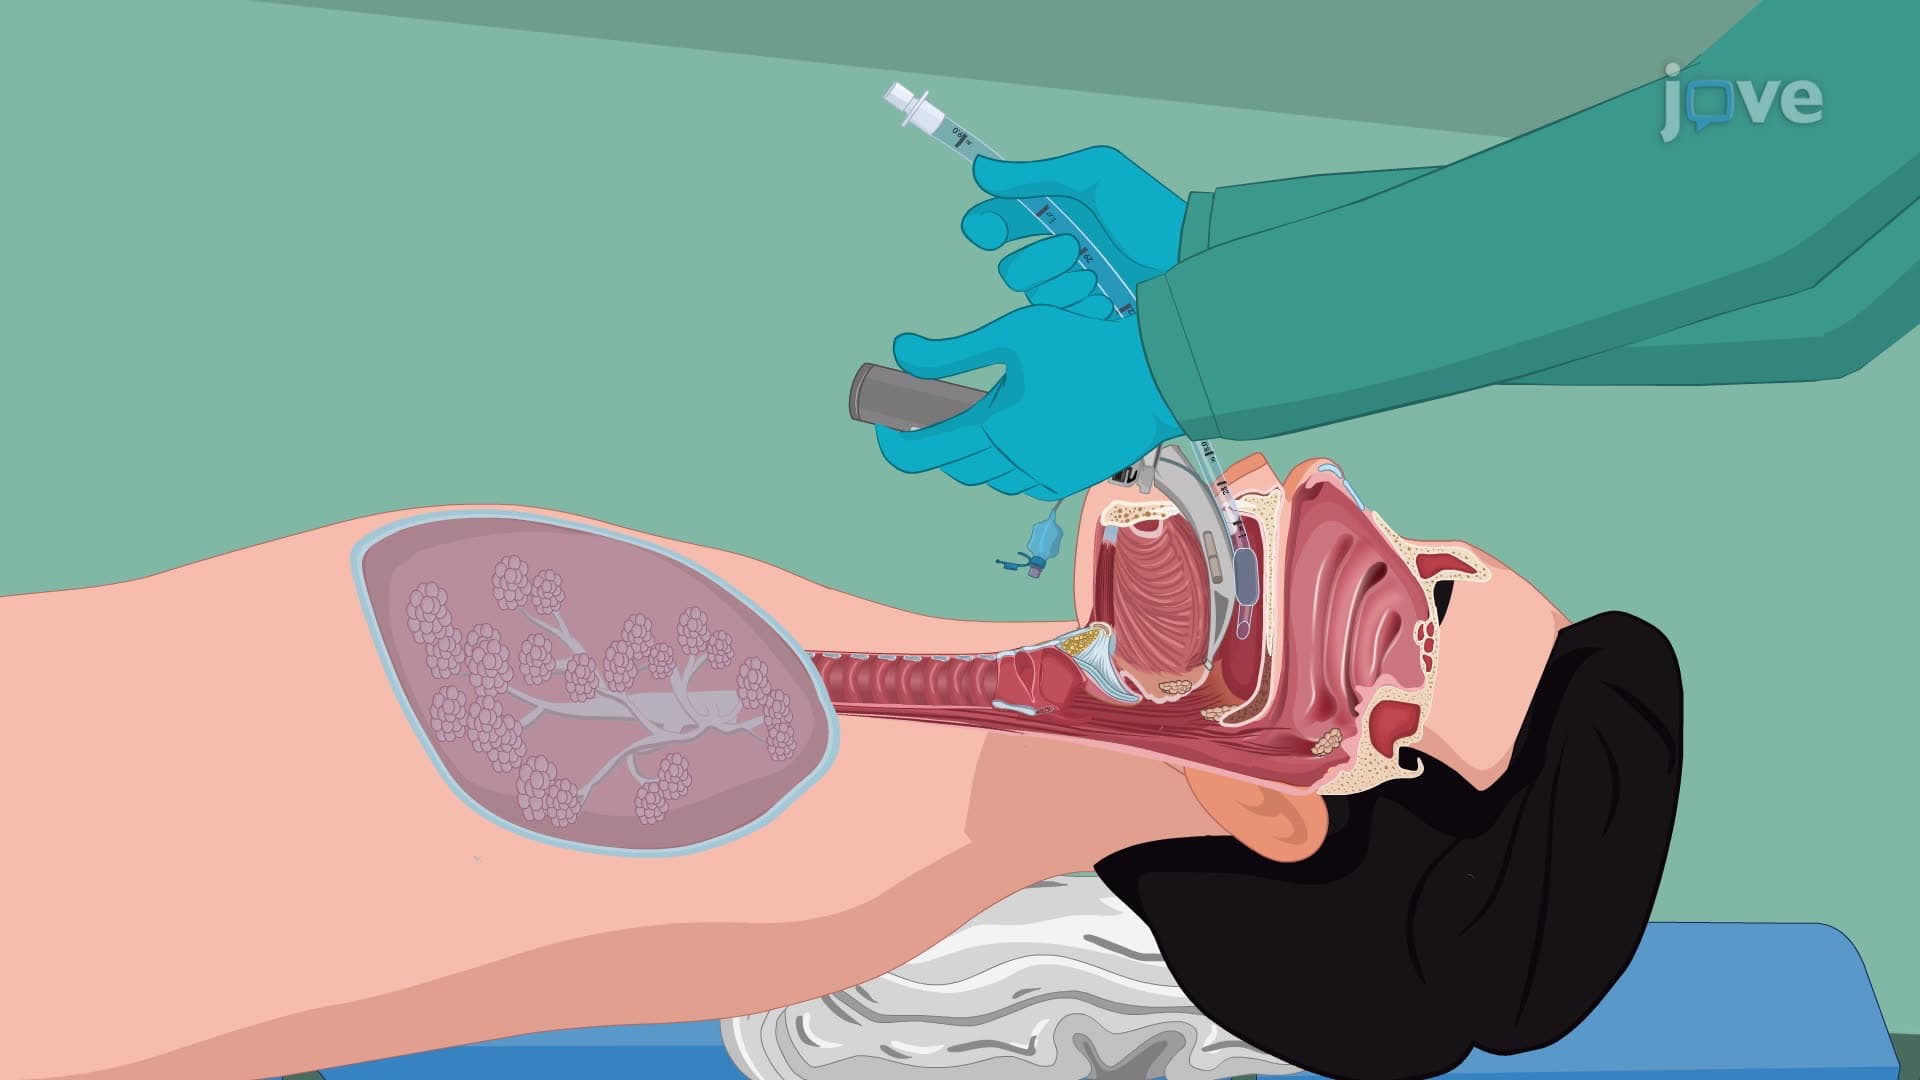 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)