Related Experiment Video
Updated: Jul 24, 2026


A General Method for Evaluating Deep Brain Stimulation Effects on Intravenous Methamphetamine Self-Administration
Published on: January 22, 2016
Methylphenidate dosing: twice daily versus three times daily
M A Stein1, T A Blondis, E R Schnitzler
1Department of Psychiatry, University of Chicago, Illinois, USA.

Objective:
To evaluate the short-term efficacy and side effects associated with two methylphenidate hydrochloride (MPH) dosing patterns.
Methods:
Twenty-five boys with attention deficit hyperactivity disorder (ADHD) participated in a 5-week, triple-blind, placebo-controlled, crossover evaluation of MPH administered twice (b.i.d.) versus thrice (t.i.d.) per day (mean dose = 8.8 +/- 5 mg, .30 +/- .1 mg/kg/dose). Four dosing conditions (placebo, titration [gradual increase to target dose], b.i.d., and t.i.d.) were used. Dependent measures obtained on a weekly basis included: parent and teacher ratings of child behavior, parent-child conflicts, parent report of stimulant side effects, child self-report of mood symptoms, a sleep log, laboratory measures of attention, and actigraphic recording of sleep activity.
Results:
All dosing conditions resulted in significant effects on ADHD symptoms when compared with baseline. Relative to placebo, t.i.d. dosing was characterized by improvement on the greatest number of behavioral measures, and both b.i.d. and t.i.d. were generally more effective than titration. Direct comparisons of b.i.d. and t.i.d. dosing revealed that t.i.d. was associated with greater improvement on the Conners Parent Rating Scale Impulsivity/Hyperactivity factor, with a similar marginally significant effect for the ADD-H Teacher Rating Scale Hyperactivity factor. The analysis of clinically significant change favored a three-times-a-day dosing schedule over placebo on both parent and teacher ratings of impulsivity/hyperactivity and attention. Compared with placebo, appetite suppression was rated, on average, as more severe in the t.i.d. and titration conditions, but not in the b.i.d. condition. However, the number of subjects who exhibited any or severe appetite suppression did not differ significantly between the b.i.d. and t.i.d. schedules. Although there was no difference in sleep duration for children on b.i.d. and t.i.d. schedules, total sleep time appeared to decrease slightly on t.i.d. relative to placebo according to both parent ratings and actigraphic assessment. There were no significant differences between b.i.d. and t.i.d. on any other side effects or sleep variables.
Conclusions:
For many children with ADHD, t.i.d. dosing may be optimal. There are few differences in acute side effects between b.i.d. and t.i.d. MPH dosing. The dosing schedule should be selected according to the severity and time course of ADHD symptoms rather than in anticipation of dosing schedule-related side effects.
More Related Videos
 07:51
A Protocol for Measuring Cue Reactivity in a Rat Model of Cocaine Use Disorder
Published on: June 18, 2018
 10:02
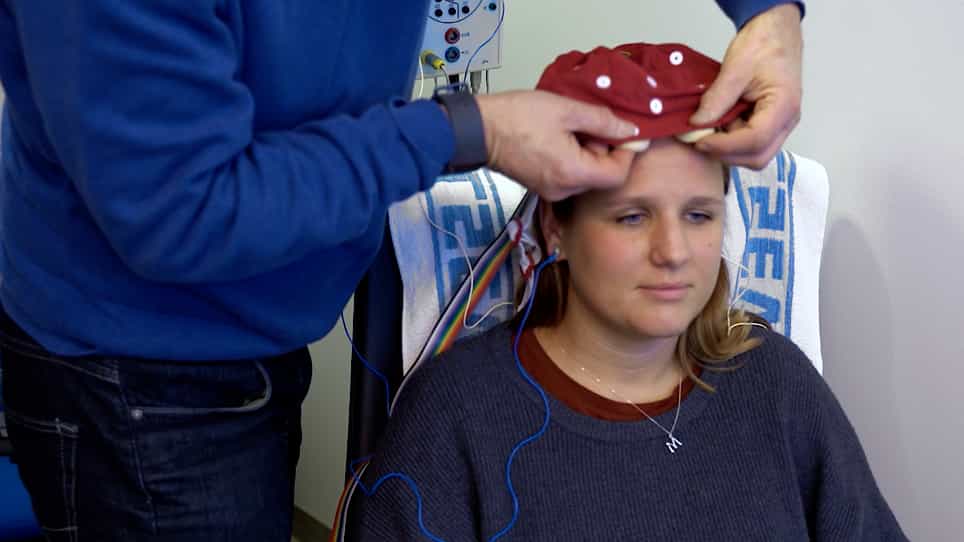
Event Related Potentials (ERPs) and other EEG Based Methods for Extracting Biomarkers of Brain Dysfunction: Examples from Pediatric Attention Deficit/Hyperactivity Disorder (ADHD)
Published on: March 12, 2020
Related Concept Videos
 01:01
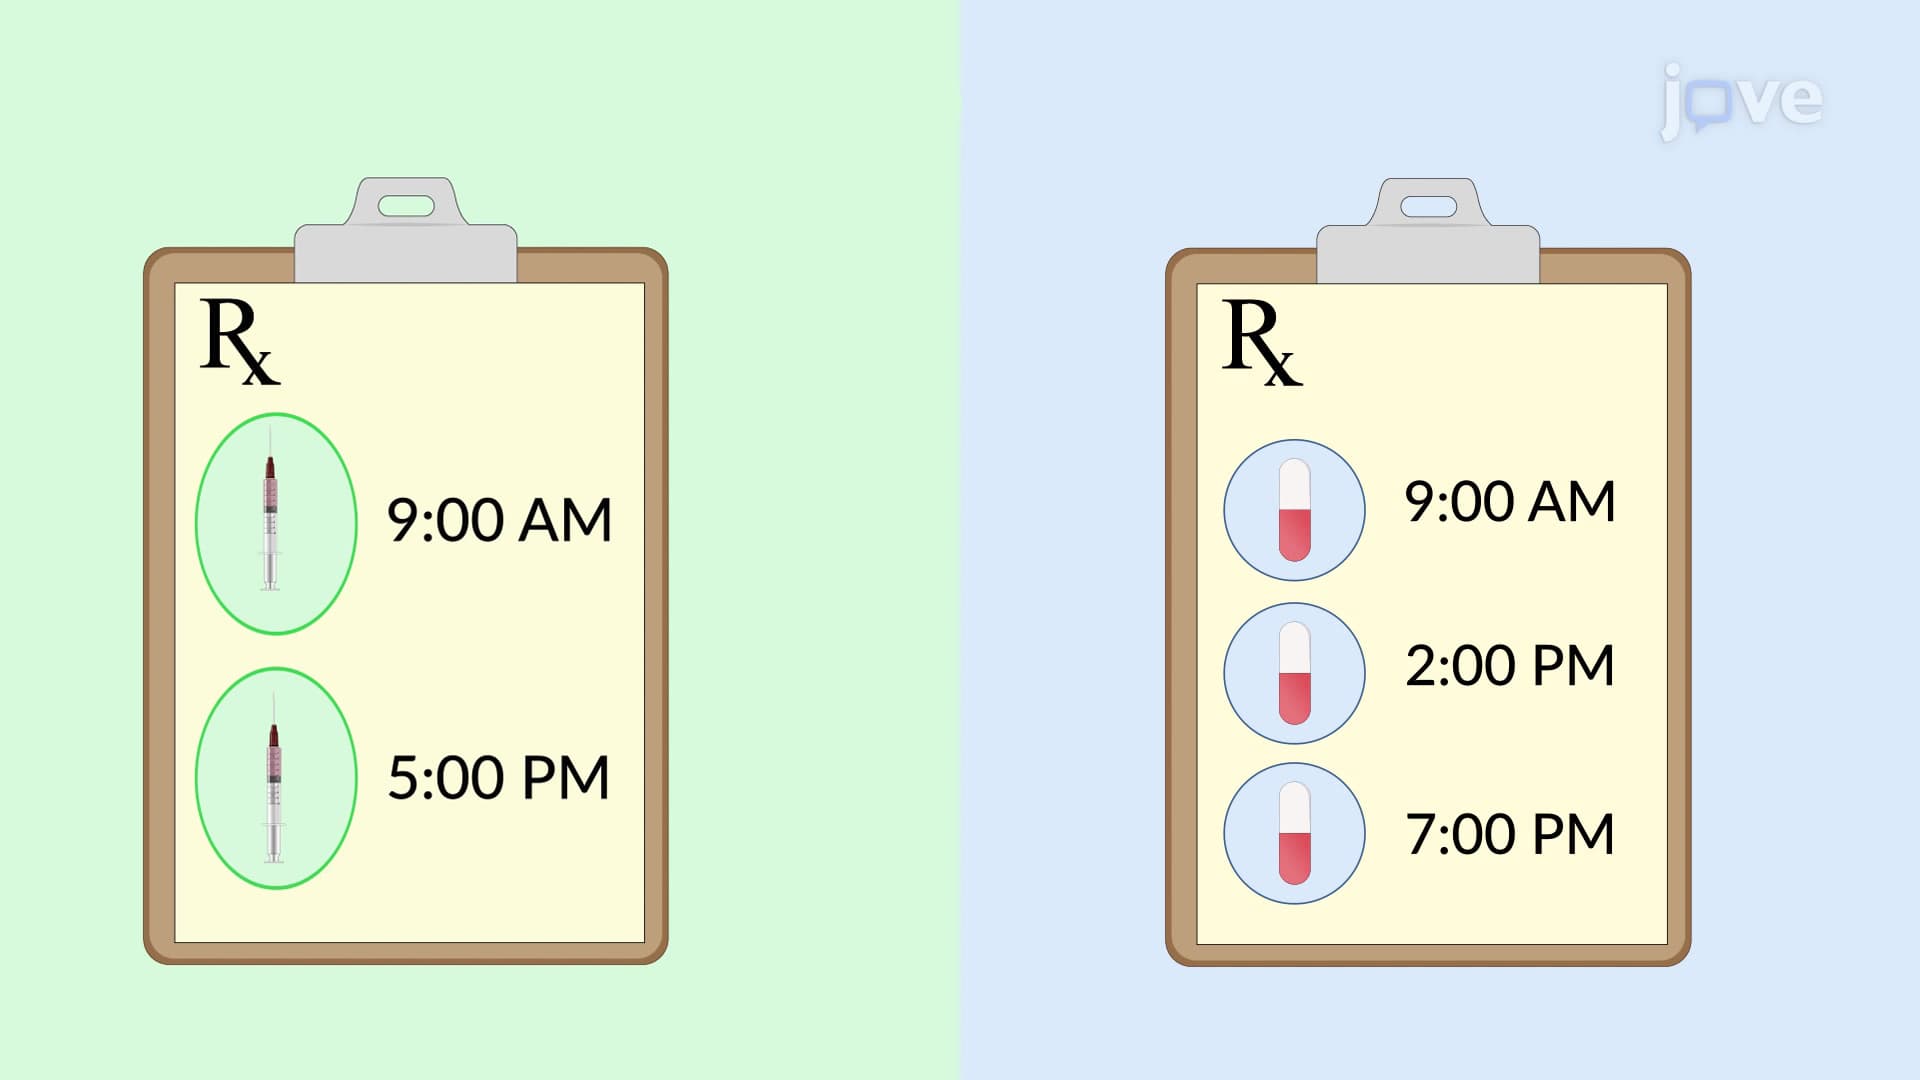
Dosage Regimen: Fixed Dose
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:28
Dosage Regimens: Designs and Approaches
 01:25
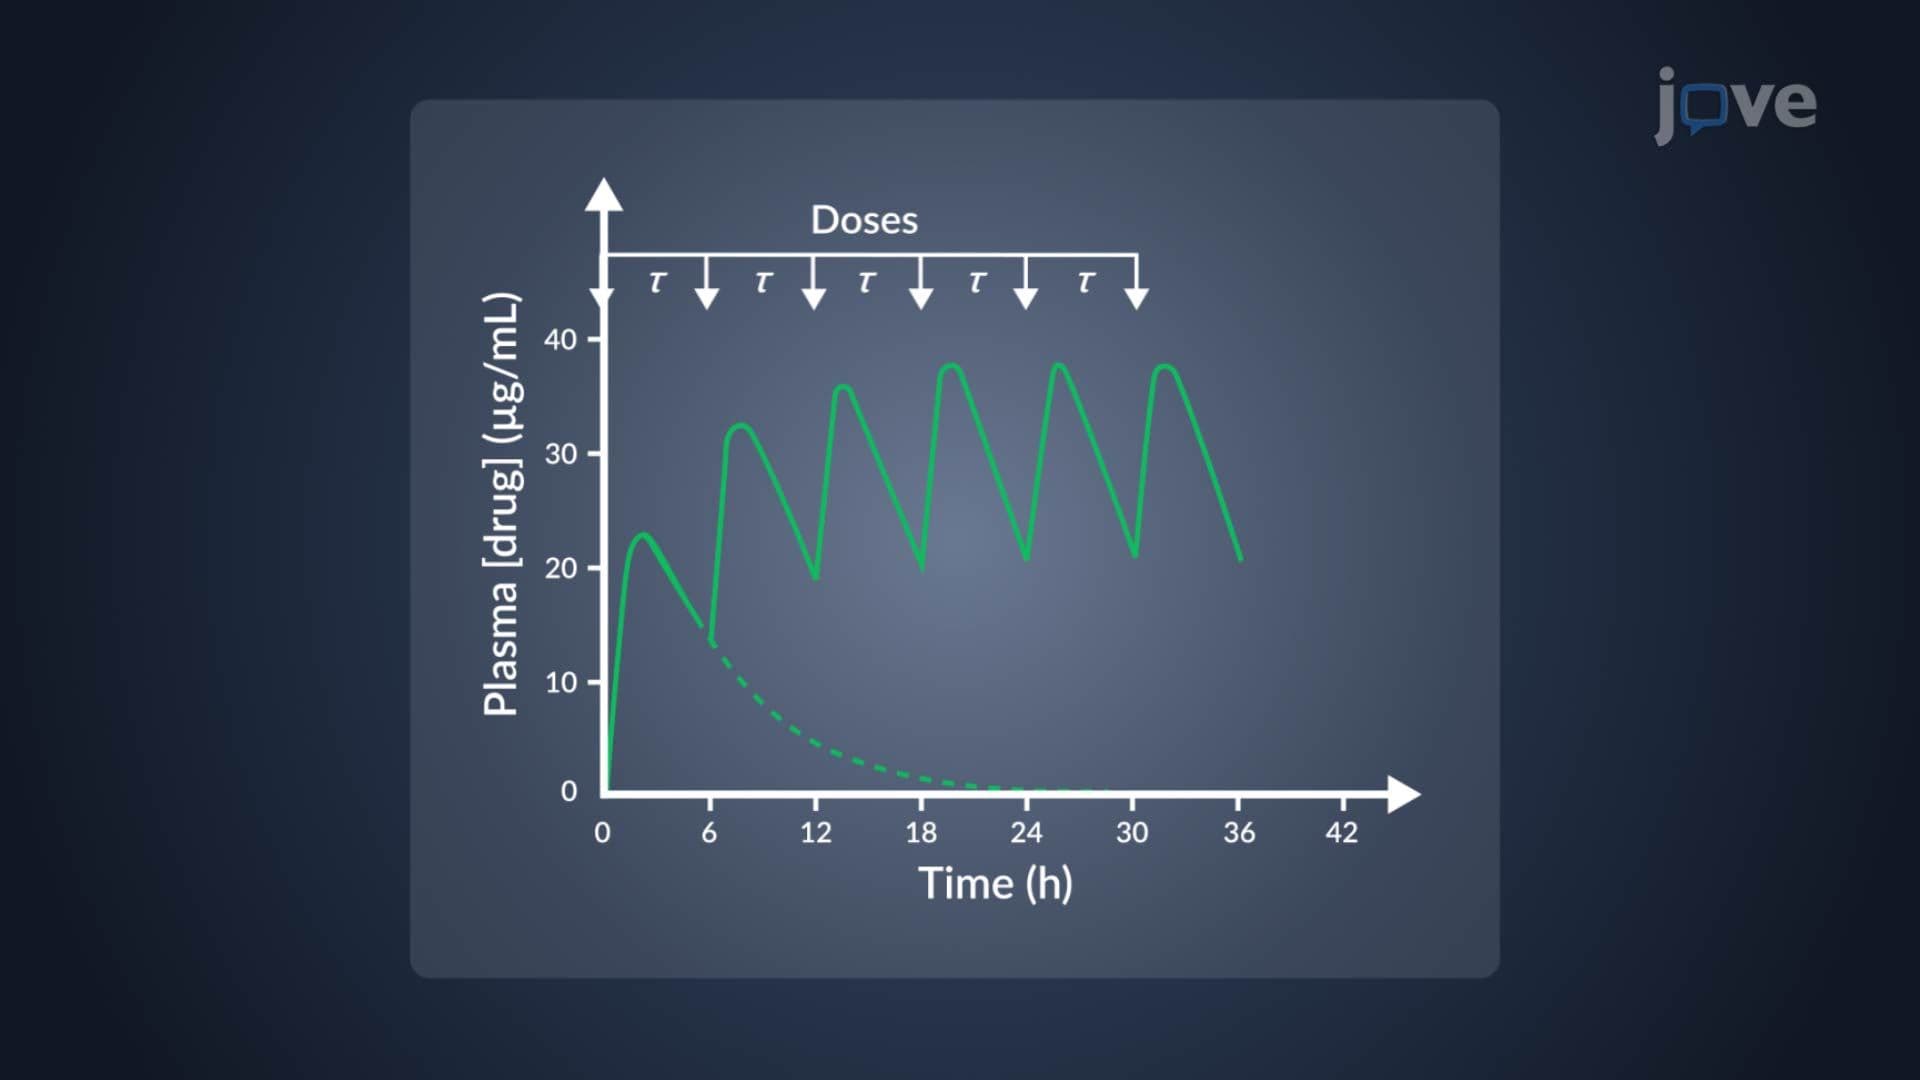
Dosage Regimen: Multiple Oral Dosage
 01:21
Dose Size and Dosing Frequency: Determination Methods
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:28
IV Infusion to Oral Dosing: Conversion Methods