Related Experiment Video
Updated: Oct 22, 2026
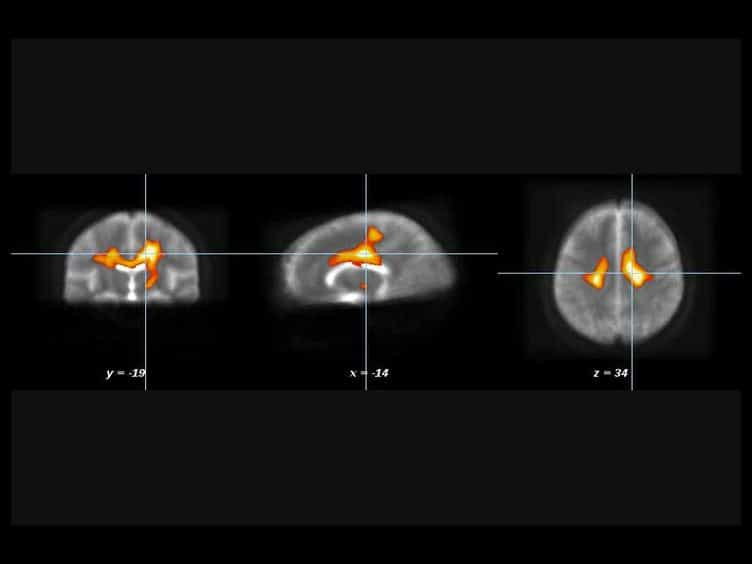
Diffusion Tensor Magnetic Resonance Imaging in the Analysis of Neurodegenerative Diseases
Published on: July 28, 2013
White matter magnetic resonance imaging hyperintensity in Alzheimer's disease: correlations with corpus callosum
P Vermersch1, J Roche, M Hamon
1Department of Neurology, CHU de Lille, France.

Abstract:
We have previously demonstrated with MRI that as well as marked white matter involvement in late-onset Alzheimer's disease (AD), atrophy of the corpus callosum may also be present. This finding prompted us to study possible correlations between atrophy of the corpus callosum and white matter hyperintensity (WMH) and between white matter lesions and the severity of the disease. We compared the corpus callosum and white matter lesions on MRI from 15 AD patients and 15 controls. The white matter lesions were scored according to the Scheltens' rating scale. We found a significant reduction of the area of the corpus callosum and more severe white matter lesions in AD patients than in controls. Both atrophy of the corpus callosum and the severity of lesions depended mainly on the diagnosis of senile dementia of the Alzheimer type and on age but not on the diagnosis of presenile AD. We demonstrated a negative correlation between white matter lesions scores and areas of corpus callosum in AD patients and no correlation between the white matter lesions and the severity of the disease. We demonstrated that white matter lesions including WMH and atrophy of the corpus callosum are more frequent in AD than in controls. The predominance of white matter lesions in senile AD may be explained by the combination of aging and disease processes.
Insights
Alzheimer's disease (AD) patients show more white matter lesions and corpus callosum atrophy than controls. These changes correlate with disease diagnosis and age, not disease severity.
Area of Science:
- Neuroimaging
- Neurology
- Gerontology
Background:
- Late-onset Alzheimer's disease (AD) is associated with white matter involvement.
- Corpus callosum atrophy has been observed in AD, prompting further investigation.
Purpose of the Study:
- To investigate correlations between corpus callosum atrophy, white matter hyperintensity (WMH), and disease severity in Alzheimer's disease.
- To compare MRI findings of corpus callosum and white matter lesions between AD patients and controls.
Main Methods:
- Magnetic Resonance Imaging (MRI) was used to compare 15 AD patients and 15 controls.
- White matter lesions were scored using the Scheltens' rating scale.
Main Results:
- AD patients exhibited significantly reduced corpus callosum area and more severe white matter lesions compared to controls.
- Corpus callosum atrophy and lesion severity were primarily linked to Alzheimer's type dementia diagnosis and age.
- A negative correlation was found between white matter lesion scores and corpus callosum area in AD patients.
Conclusions:
- White matter lesions, including WMH and corpus callosum atrophy, are more prevalent in AD patients.
- The increased white matter lesions in senile AD may result from combined aging and disease processes.

Related Concept Videos
 01:29
Alzheimer Disease l: Introduction
 01:23
Alzheimer Disease ll: Pathophysiology
 01:22
Dementia l: Introduction