Related Experiment Video
Updated: May 5, 2026

Methods to Assess Beta Cell Death Mediated by Cytotoxic T Lymphocytes
Published on: June 16, 2011
Autoantibodies to the insulin receptor. Effect on the insulin-receptor interaction in IM-9 lymphocytes

The serum of some patients with insulin-resistant "diabetes" contains antibodies that bind to and block the cell membrane receptors for insulin. In this report, we have characterized the effects of the antireceptor antibodies on the interaction of (125)I-insulin with its receptor on the human lymphoblastoid cell line IM-9. Up to 95% of specific insulin binding can be inhibited by pretreatment of the cells with these immunoglobulins. The onset of the inhibitory effect is time- and temperature-dependent, and the effect is reversed extremely slowly if the cells are suspended in a large excess of antibody-free buffer. These features of antibody binding can be easily distinguished from those for insulin binding to its receptor. The inhibitory effect of the antibodies can be reversed by exposure of the cells to conditions known to elute surface immunoglobulins. The three antireceptor sera studied appear to alter the insulin-receptor interaction in different ways. Two antisera markedly reduce receptor affinity through combined effects on the insulin association and dissociation rates, and, additionally, have smaller effects on available receptor number. A third antiserum primarily affects available receptor number and has little effect on receptor affinity. All three antisera inhibit the capacity of insulin to promote negatively cooperative site-site interactions among insulin receptors. The data suggest that these autoantibodies to the insulin receptor bind to different determinants on the receptor and may therefore be useful as unique probes of insulin receptor structure and function.
The serum of some patients with insulin-resistant "diabetes" contains antibodies that bind to and block the cell membrane receptors for insulin. In this report, we have characterized the effects of the antireceptor antibodies on the interaction of (125)I-insulin with its receptor on the human lymphoblastoid cell line IM-9. Up to 95% of specific insulin binding can be inhibited by pretreatment of the cells with these immunoglobulins. The onset of the inhibitory effect is time- and temperature-dependent, and the effect is reversed extremely slowly if the cells are suspended in a large excess of antibody-free buffer. These features of antibody binding can be easily distinguished from those for insulin binding to its receptor. The inhibitory effect of the antibodies can be reversed by exposure of the cells to conditions known to elute surface immunoglobulins. The three antireceptor sera studied appear to alter the insulin-receptor interaction in different ways. Two antisera markedly reduce receptor affinity through combined effects on the insulin association and dissociation rates, and, additionally, have smaller effects on available receptor number. A third antiserum primarily affects available receptor number and has little effect on receptor affinity. All three antisera inhibit the capacity of insulin to promote negatively cooperative site-site interactions among insulin receptors. The data suggest that these autoantibodies to the insulin receptor bind to different determinants on the receptor and may therefore be useful as unique probes of insulin receptor structure and function.


Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:28
Insulin: The Receptor and Signaling Pathways
 01:25
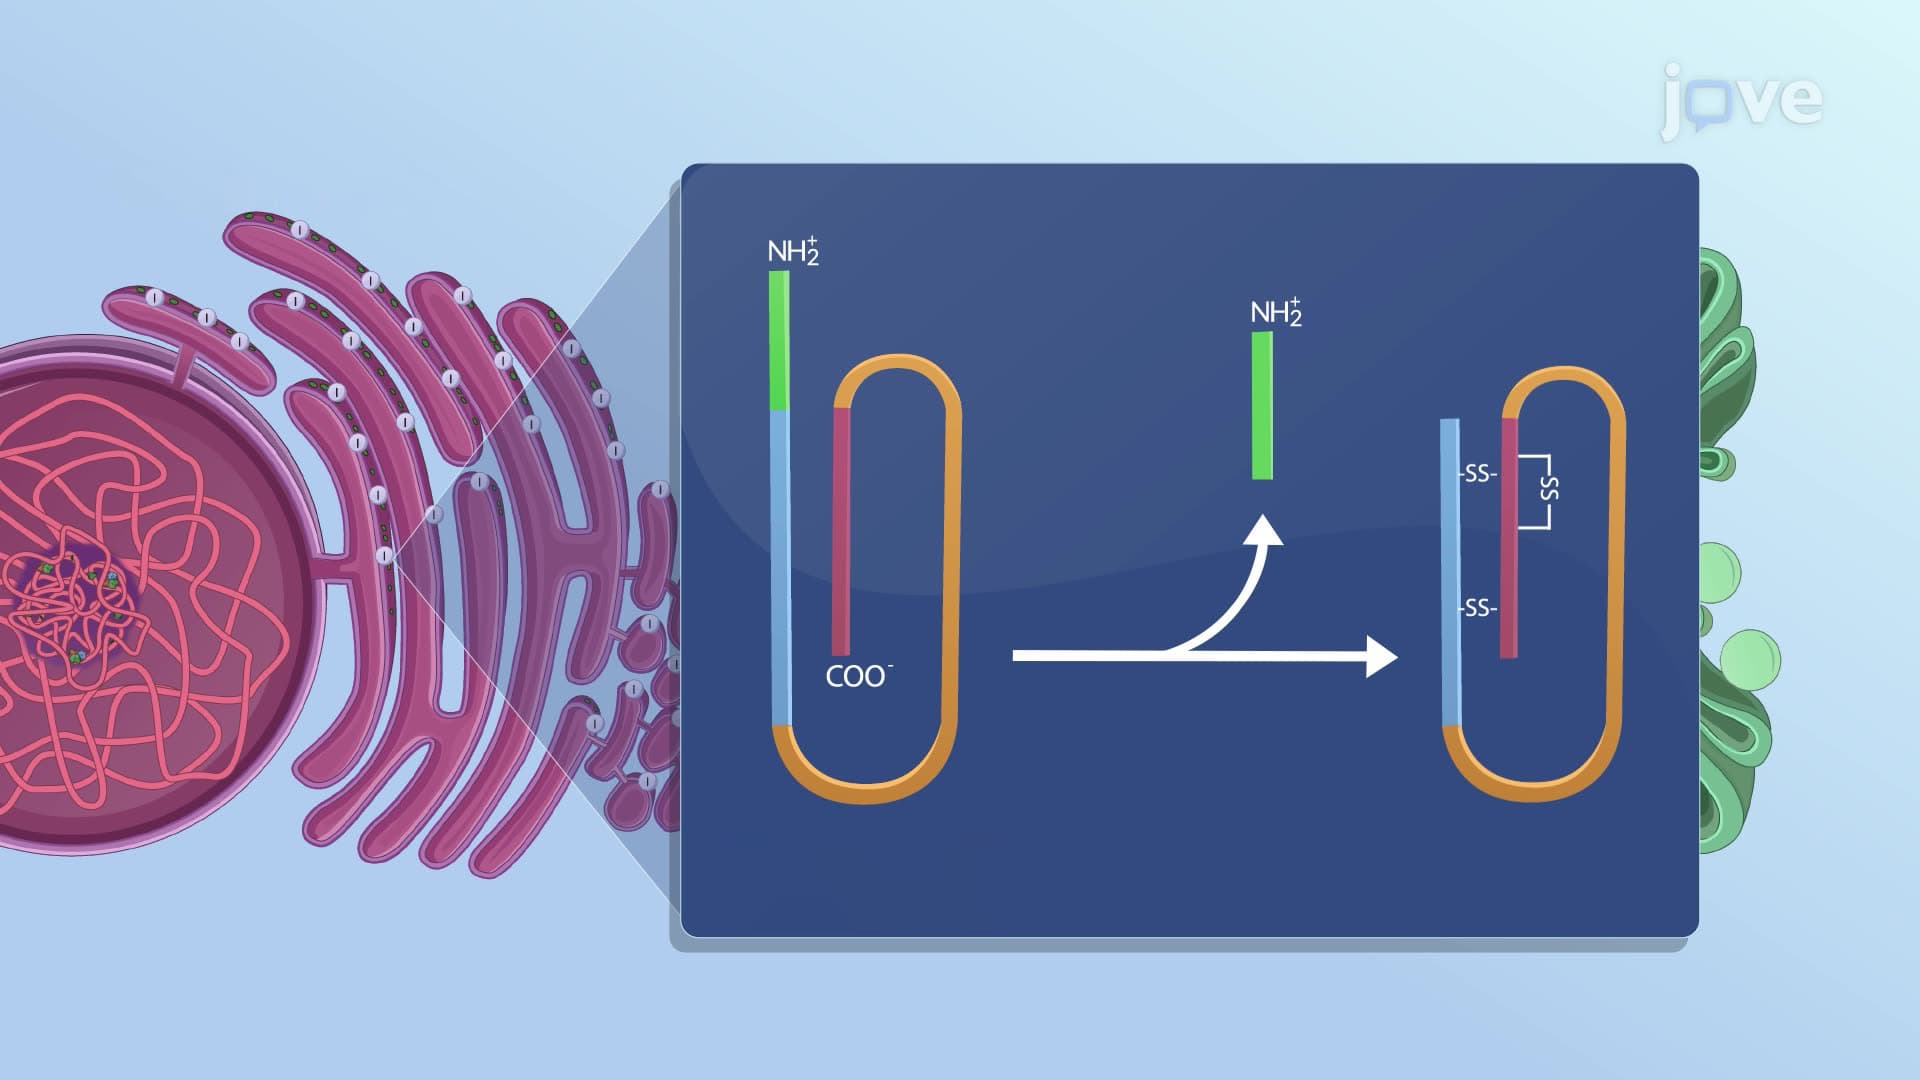
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:12
Type I Diabetes I: Introduction
 01:26
Type I Diabetes II: Pathophysiology