Residual postoperative paralysis. Pancuronium versus mivacurium, does it matter?
Related Experiment Video
Updated: Nov 3, 2026
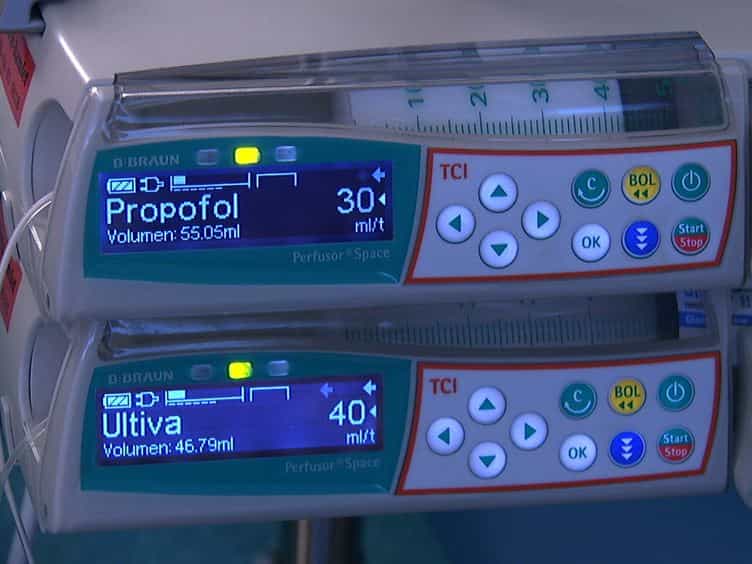
Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
1New York Medical College, Valhalla, USA. akopman@aol.com

Background:
Based on a train-of-four (TOF) ratio greater than 0.70 as the standard of acceptable clinical recovery, undetected postoperative residual paralysis occurs frequently in postanesthesia care units. In most published studies, detailed information regarding anesthetic management is not provided. The authors reexamined the incidence of postoperative weakness after the administration of long- and short-acting neuromuscular blockers because few, if any, such comparative studies are available.
Methods:
Ninety-one adult patients were studied. In group 1 (mivacurium, n = 35), anesthesia was induced with propofol/ fentanyl and maintained with nitrous oxide, desflurane, and opioid supplementation. The response of the adductor pollicis to ulnar nerve stimulation was estimated by palpating the thumb. Mivacurium (0.20 mg/kg) was administered for tracheal intubation, and an infusion was adjusted to maintain the TOF count at 1. When surgery was completed, the infusion was discontinued. When a second twitch could be detected, 7.0 micrograms/kg atropine and then 0.5 mg/kg edrophonium were administered. At 5 and 10 min, the mechanical TOF response was measured. Additional measurements were recorded if possible. Patients were tracheally extubated and discharged from the operating room when they could respond to verbal commands and no TOF fade was palpable. In group 2 (pancuronium-desflurane anesthesia, n = 29), the protocol was identical to that of group 1, except that 0.07 mg/kg pancuronium was administered for tracheal intubation. Additional increments (0.5 to 1 mg) were given as needed. Antagonism was accomplished with 0.05 mg/kg neostigmine and 0.01 mg/kg glycopyrrolate. In group 3 (pancuronium propofol-opioid, n = 27), the protocol was identical to that of group 2, except that anesthesia was maintained with nitrous oxide and a propofol-alfentanil infusion. In all groups, patients were assessed until a TOF ratio of 0.90 or more was achieved.
Results:
All of the patients in group 1 had TOF ratios greater than 0.80 on arrival in the postanesthesia care unit. Twenty of 35 patients had TOF ratios 0.90 or more while they were still in the operating room. Thirty-three of 35 patients had TOF ratios 0.90 or more within 30 min of reversal, and this value was reached in all patients by 45 min. Recovery parameters in groups 2 and 3 did not differ from each other. Hence data from these groups were pooled. Fifty-four of 56 patients who received pancuronium had TOF values of 0.70 or more, the remaining two patients had values of 0.6 to 0.7. In contrast to the mivacurium group, however, only four patients achieved a TOF ratio of 0.90 or greater while still in the operating room. Finally, eight of these patients did not achieve this degree of recovery within 90 min of reversal.
Conclusions:
These results suggest that if nondepolarizing neuromuscular blockers are administered using tactile evaluation of the TOF count as a guide, critical episodes of postoperative weakness in the postanesthesia care unit should occur infrequently even with long-acting relaxants. Nevertheless, if full recovery is defined as return to a TOF ratio of 0.90 or more, then short-acting agents would appear to offer a wider margin of safety.
Insights
Postoperative residual paralysis is common, but using tactile train-of-four (TOF) monitoring can reduce its incidence. Short-acting neuromuscular blockers offer a wider margin of safety for full recovery.
Area of Science:
- Anesthesiology
- Pharmacology
- Critical Care Medicine
Background:
- Postoperative residual paralysis (POP) is a frequent complication in postanesthesia care units (PACUs).
- Existing studies often lack detailed anesthetic management information.
- Comparative studies on long- and short-acting neuromuscular blockers are scarce.
Purpose of the Study:
- To reexamine the incidence of postoperative weakness after administering long- and short-acting neuromuscular blockers.
- To compare the recovery profiles of mivacurium and pancuronium.
- To evaluate the effectiveness of tactile train-of-four (TOF) monitoring in guiding neuromuscular blockade reversal.
Main Methods:
- Ninety-one adult patients were divided into three groups receiving mivacurium or pancuronium.
- Anesthesia was induced and maintained using various agents including propofol, fentanyl, desflurane, and nitrous oxide.
- Neuromuscular blockade was monitored using tactile TOF stimulation, with reversal agents administered based on twitch response.
Main Results:
- All patients receiving mivacurium achieved TOF ratios greater than 0.80 in the PACU, with many reaching 0.90 in the operating room.
- Patients receiving pancuronium showed slower recovery, with some not reaching a TOF ratio of 0.90 within 90 minutes of reversal.
- Recovery parameters did not differ between pancuronium-desflurane and pancuronium-propofol anesthesia groups.
Conclusions:
- Tactile TOF monitoring can minimize postoperative weakness in the PACU, even with long-acting neuromuscular blockers.
- Full recovery (TOF ratio ≥ 0.90) is more consistently achieved with short-acting agents like mivacurium.
- Nondepolarizing neuromuscular blockers require careful monitoring for safe patient recovery.
Related Concept Videos
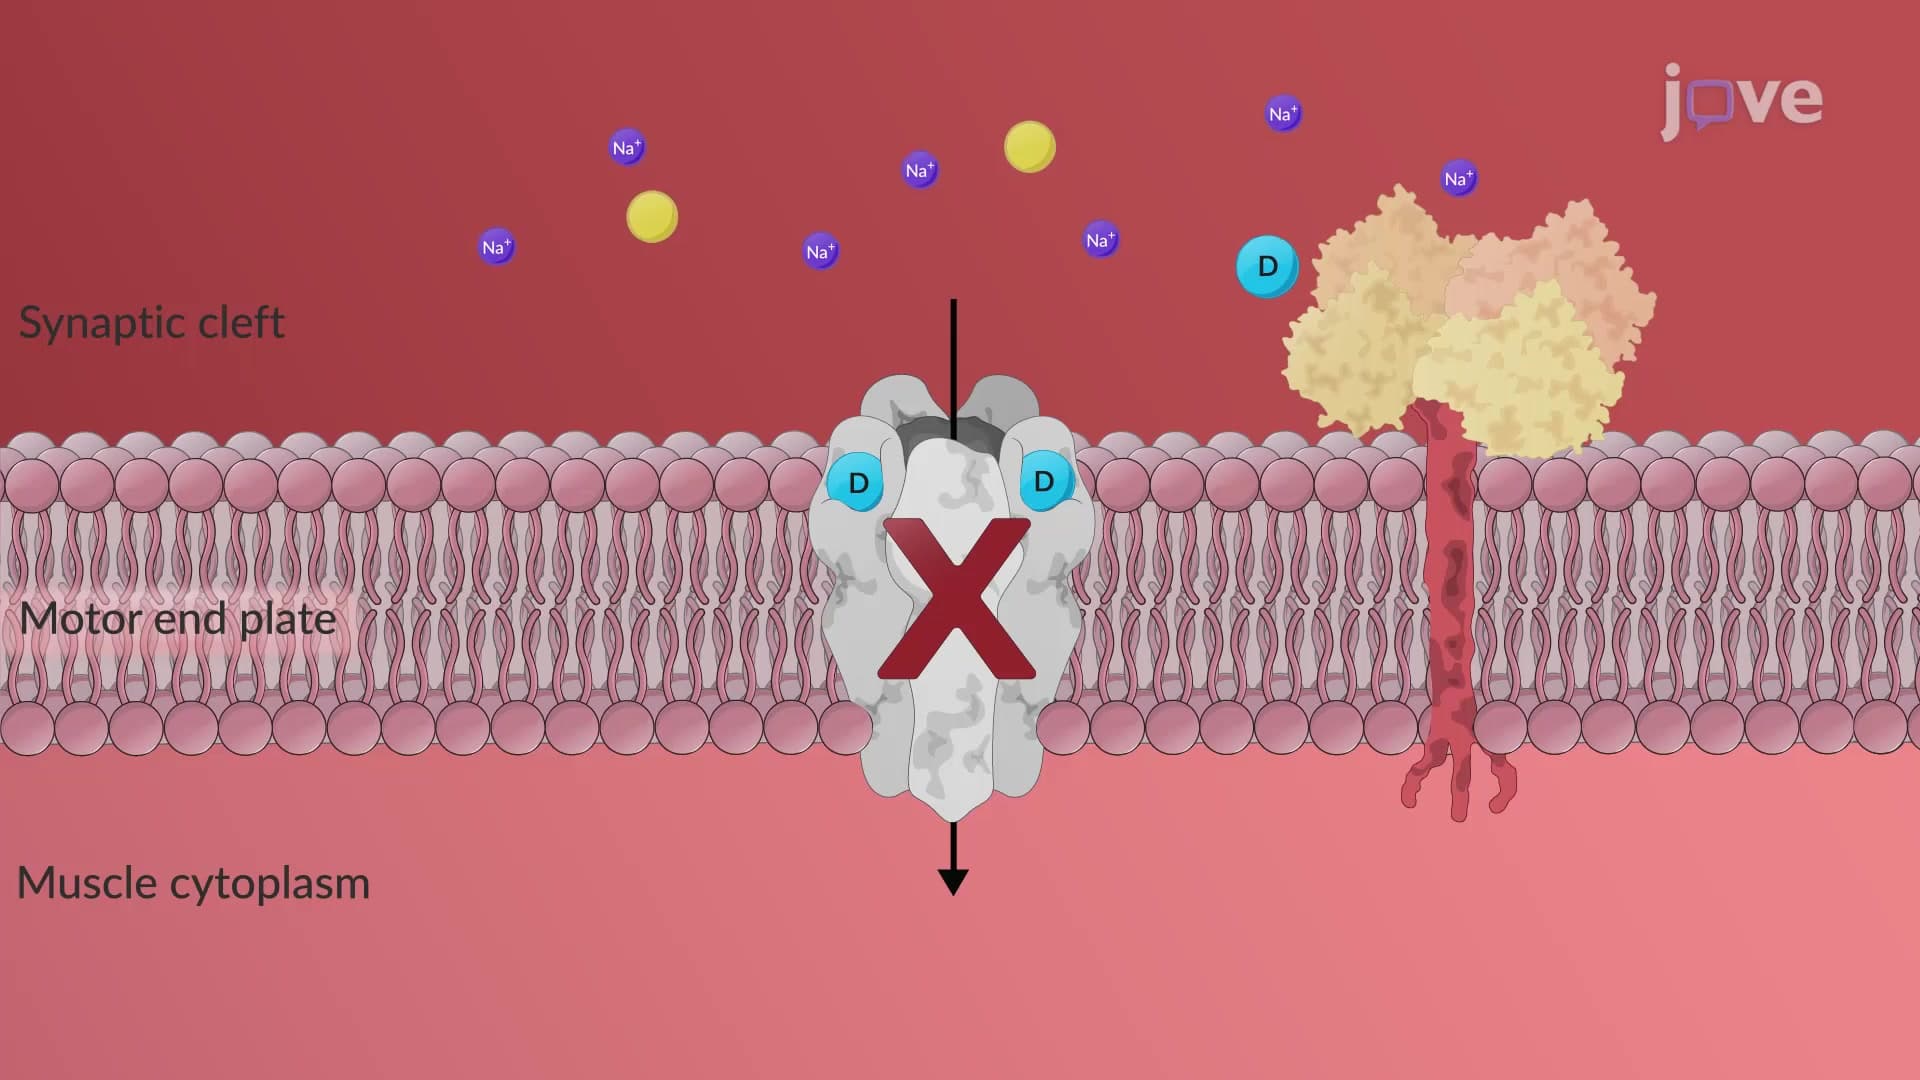 01:17
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
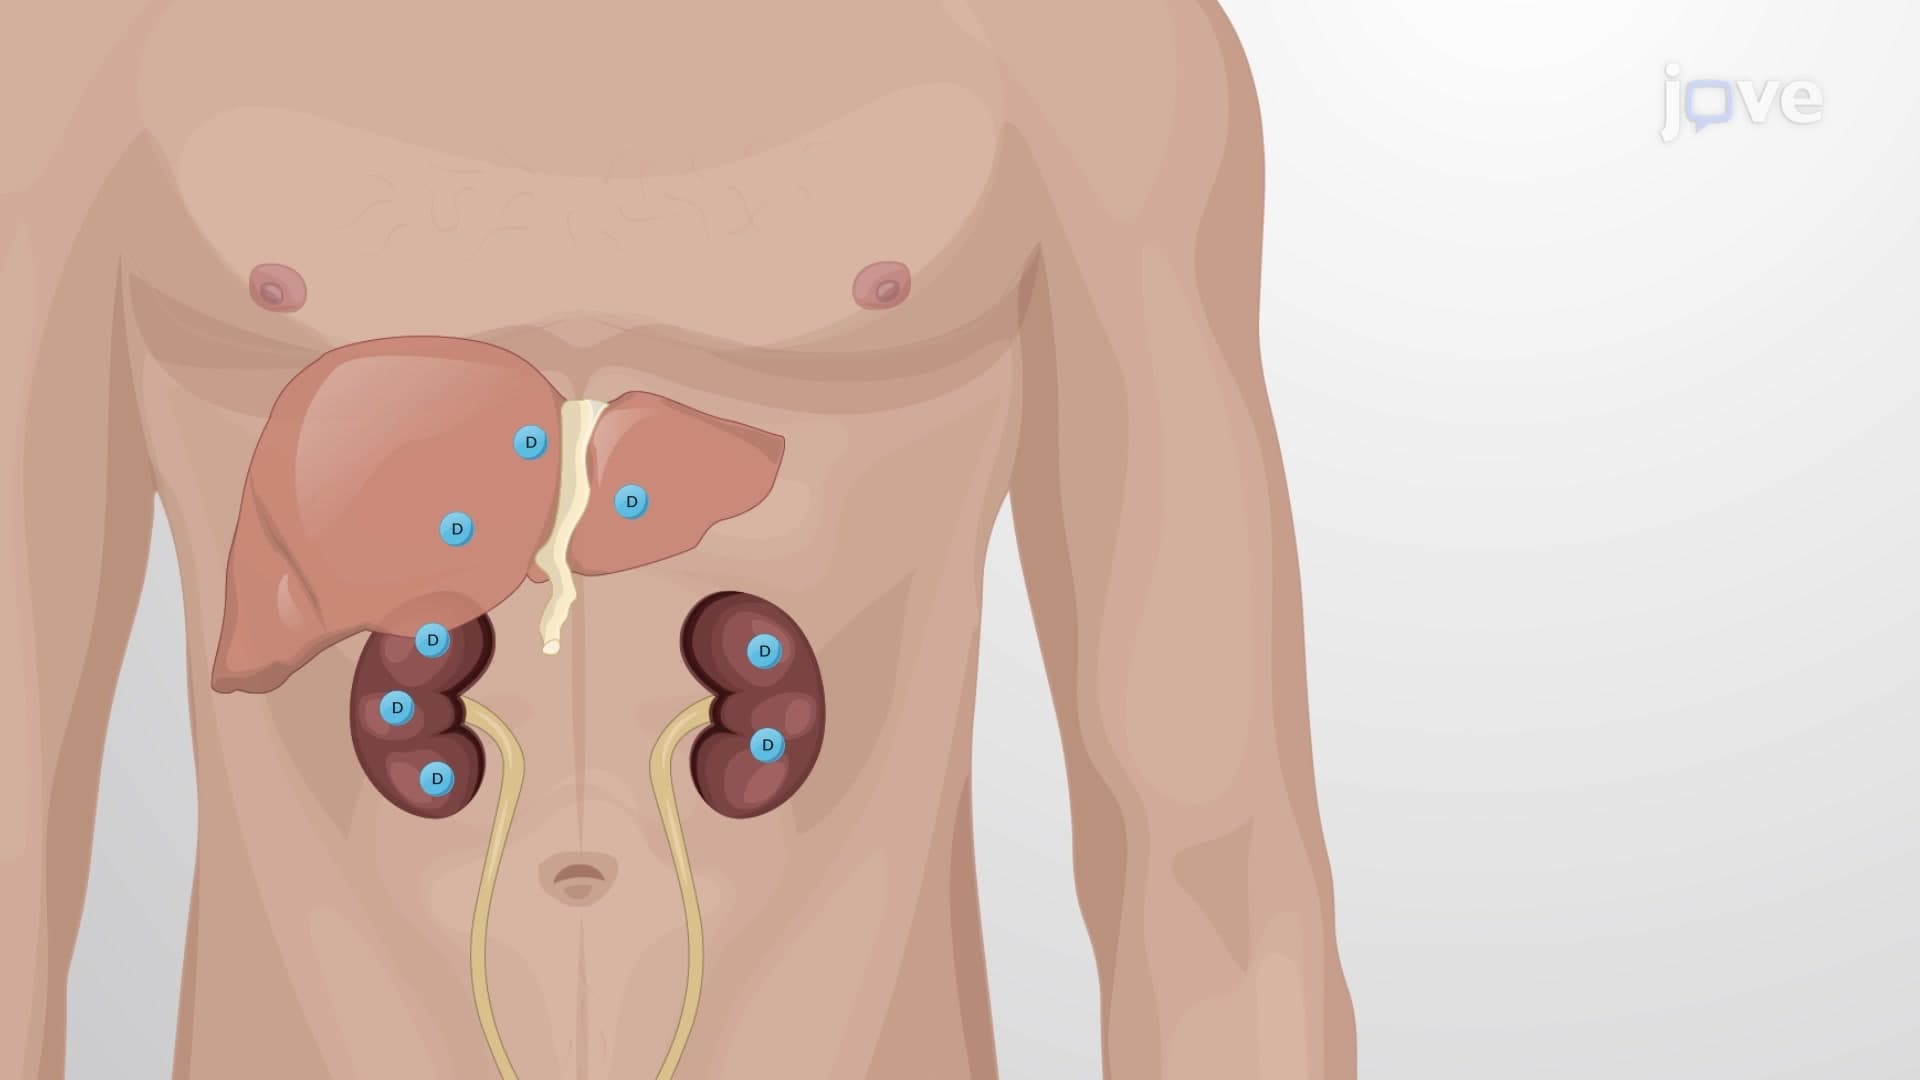 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
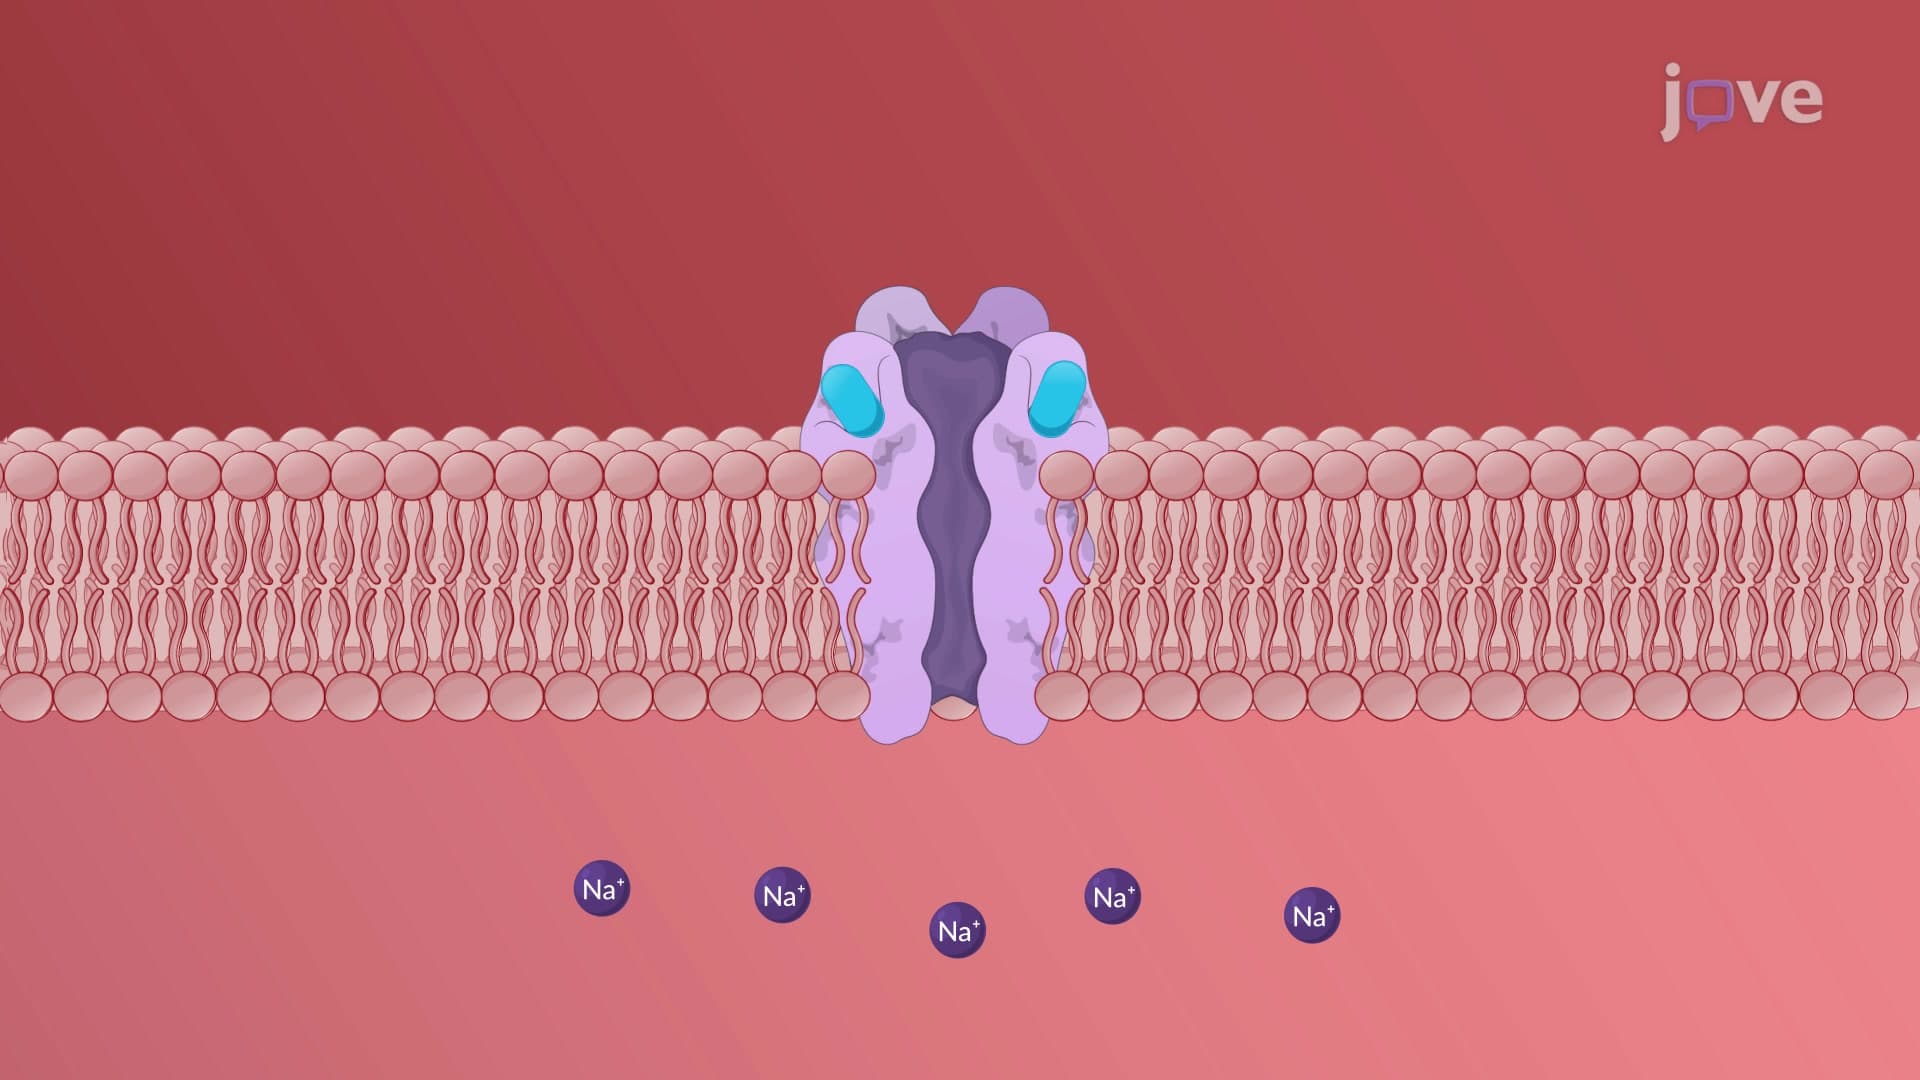 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics