Related Experiment Video
Updated: Jul 30, 2026


Quantitative Assessment of Cortical Auditory-tactile Processing in Children with Disabilities
Published on: January 29, 2014
Interviewing young children about body touch and handling

Abstract:
Children aged 3-6 years were interviewed following a scheduled pediatric clinic visit to assess the efficacy of two independent variables--interview strategy and number of interviews--on the accuracy, completeness, and consistency of children's reports. Four experimental interviews were created--a verbal interview and three interviews enhanced with anatomically detailed cues (dolls, line drawings, and computer graphics), photographs, and props. Initially, 130 children were interviewed after the clinic event. One month later, 124 were interviewed again, and 74 were interviewed a third time after 6 months. Children's reports were compared to videotapes and medical records of their pediatric visit in order to create three dependent reporting variables--accuracy, completeness, and consistency. In addition, the predictive power of four sets of covariates on reporting was assessed: (1) age and gender, (2) ethnicity, medical history, family stress, and mother's education; (3) number of invasive medical procedures, number of body touches, health status, and child's pain judgments; and (4) number of outpatient and inpatient visits between the initial and the follow-up interviews at 1 and 6 months. Initially, children's spontaneous reports of body touch were highly accurate, but sparse. After a 1-month delay, accuracy and completeness dropped significantly: accuracy was stable from 1 to 6 months; completeness rebounded at 6 months. Three-year-olds' reports of body touch were less complete and less consistent, but rarely less accurate, than those of older age groups. After 1- and 6-month delays, consistently reported information was more accurate than new information. Children's pain ratings contributed positively to predictions of completeness at the initial and 1-month interviews and to completeness and accuracy at 6 months. Complex events were reported more accurately but less consistently. Anatomically detailed cues in the three enhanced interviews increased completeness of reporting of total body and genital touch. Photos elicited more useful information for identification of persons and places than did questions, while medical props initially offered no advantage and subsequently led to errors. Children's feelings also influenced reporting: higher ratings of anger, sadness, and fright were positively related to reporting of extremely painful touch, while some children who failed to report painful, invasive medical procedures displayed shame when interviewed. The relative privacy of the computer-assisted interview holds promise for disclosure of sexual topics.

Related Concept Videos
 02:30
Naturalistic Observations
 01:14
Assessing Body Temperature - Oral
Step 1:
Start by practicing proper hand hygiene to prevent the spread of microorganisms.
Step 2:
Take the thermometer out of the charging unit, switch it on, and wait for the ready sign.
Step 3:
Gently slide the probe cover until a click is heard. This simple action prevents cross-contamination and ensures the correct placement of the probe cover.
Step 4:
Instruct the patient to open their mouth and place...
 01:27
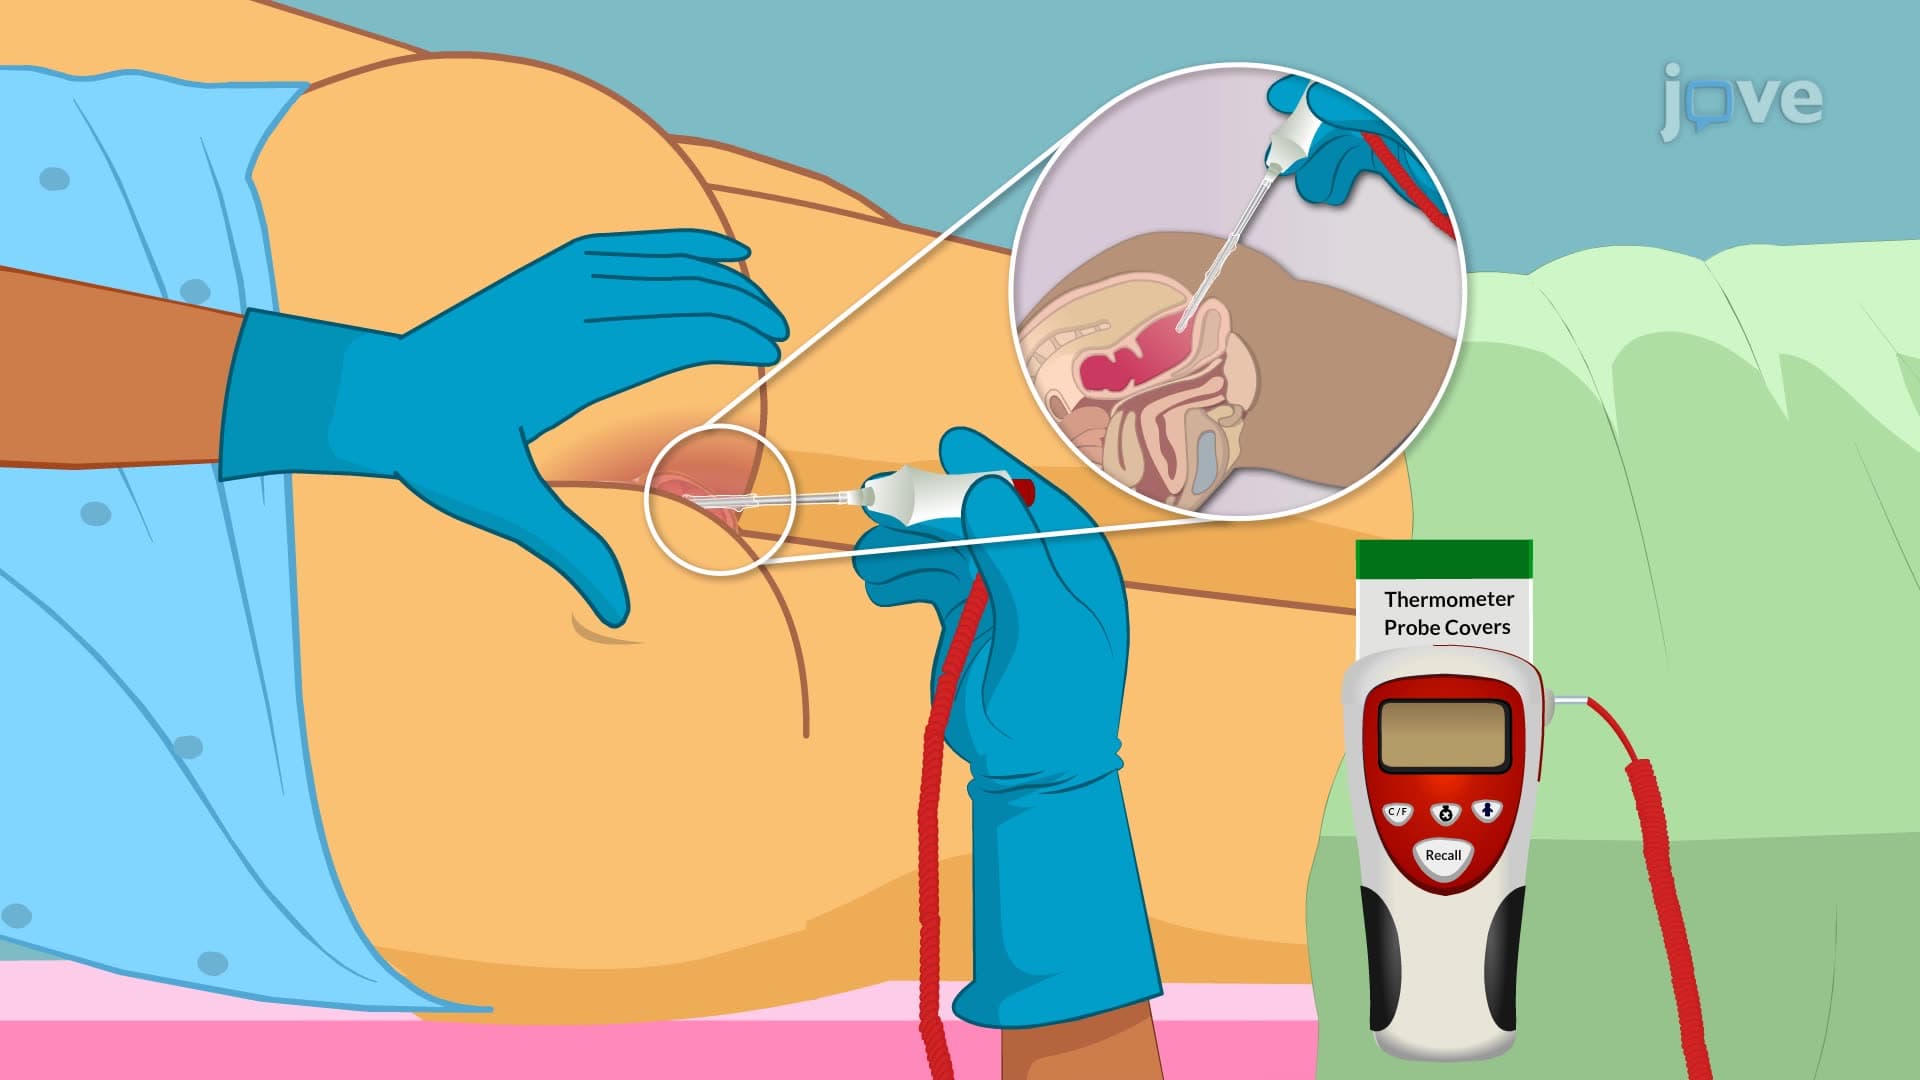
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:14
Assessing Body Temperature - Axilla
Step 1: Perform hand hygiene and put on clean gloves to maintain infection control and prevent cross-contamination.
Step 2: Prepare the patient by explaining the procedure to ensure understanding and cooperation. Ensure privacy, expose the axilla, and inform the patient that minimal movement is crucial for an accurate reading.
Step 3: Adjust the patient’s clothing to expose only the axilla. It minimizes...
 01:15
Techniques of therapeutic communication I: Active Listening, Sharing Observations, Validation, and Using Touch
Therapeutic communication is not the same as social interaction. Social interaction has no goal or purpose and consists of casual information sharing, whereas therapeutic communication has a plan or purpose for the conversation. Therapeutic...
 01:20
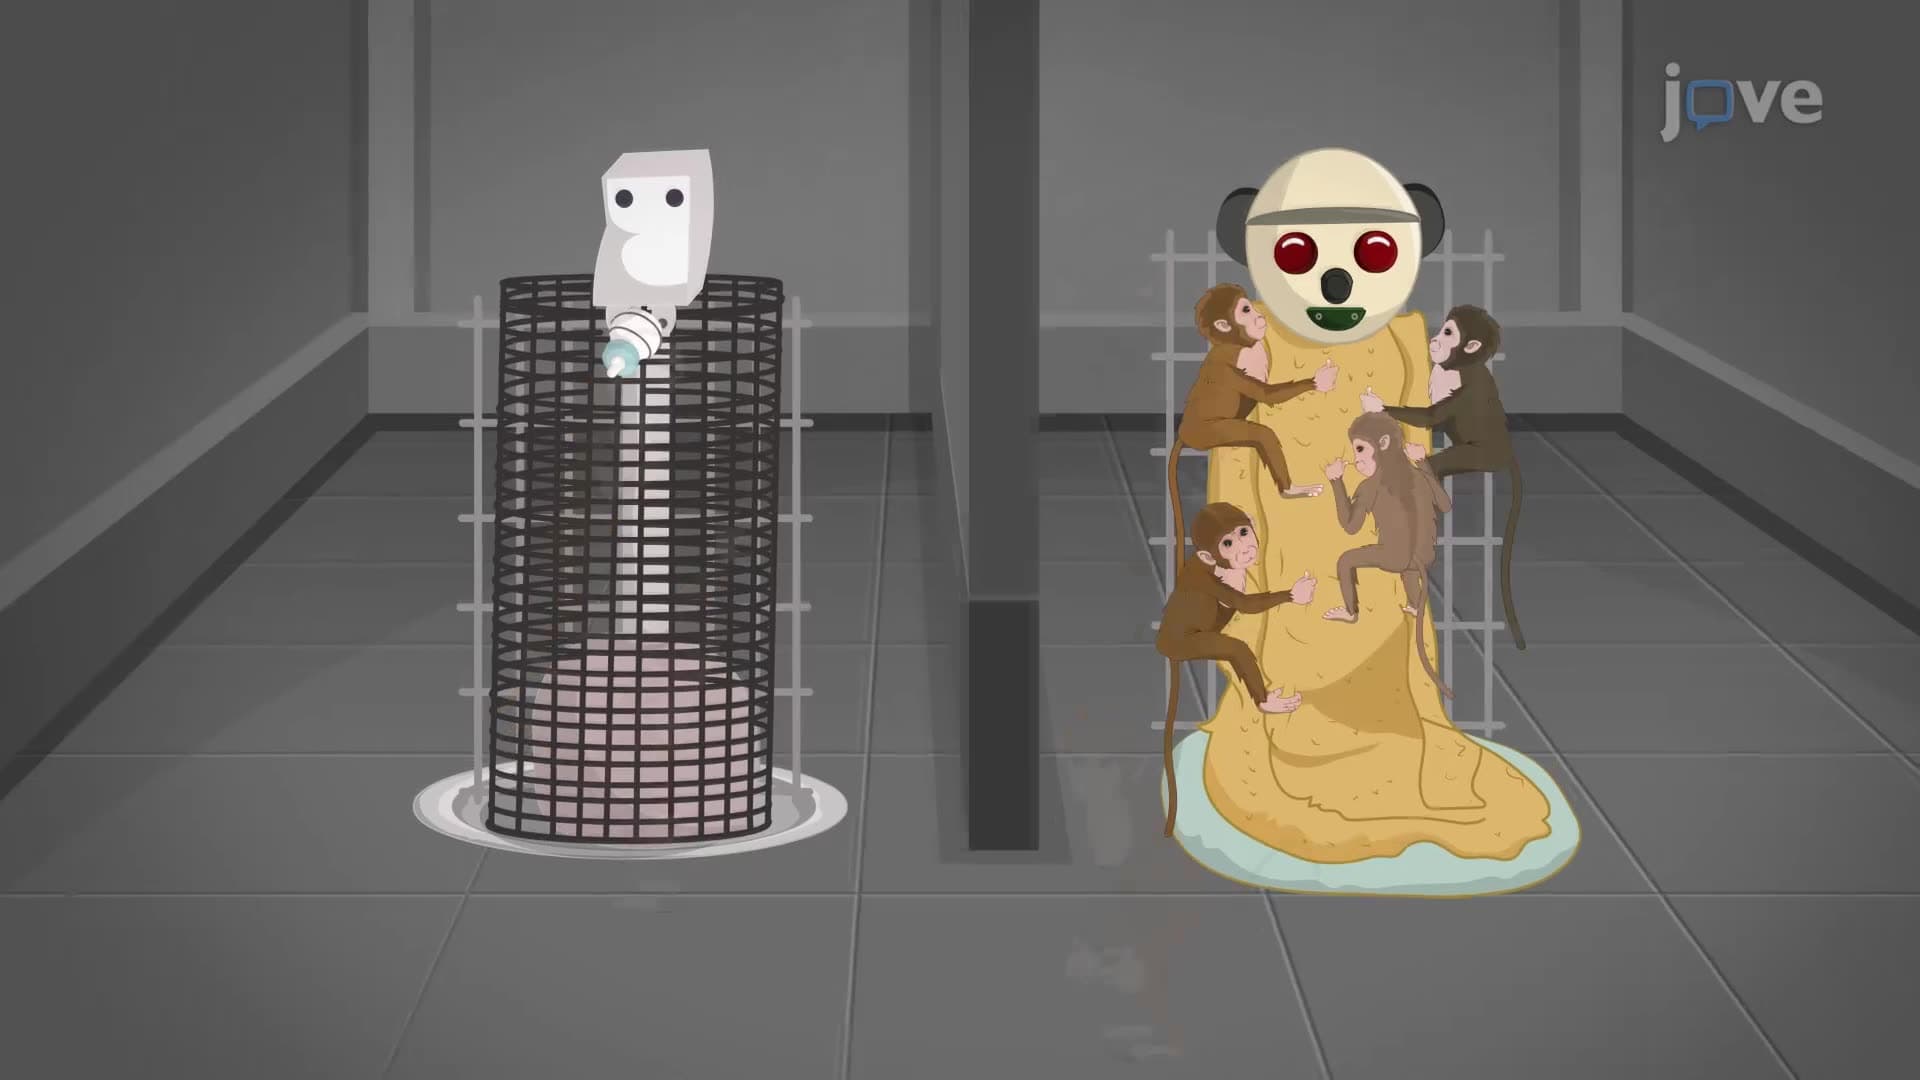
Attachment