Related Experiment Video
Updated: Jul 21, 2026
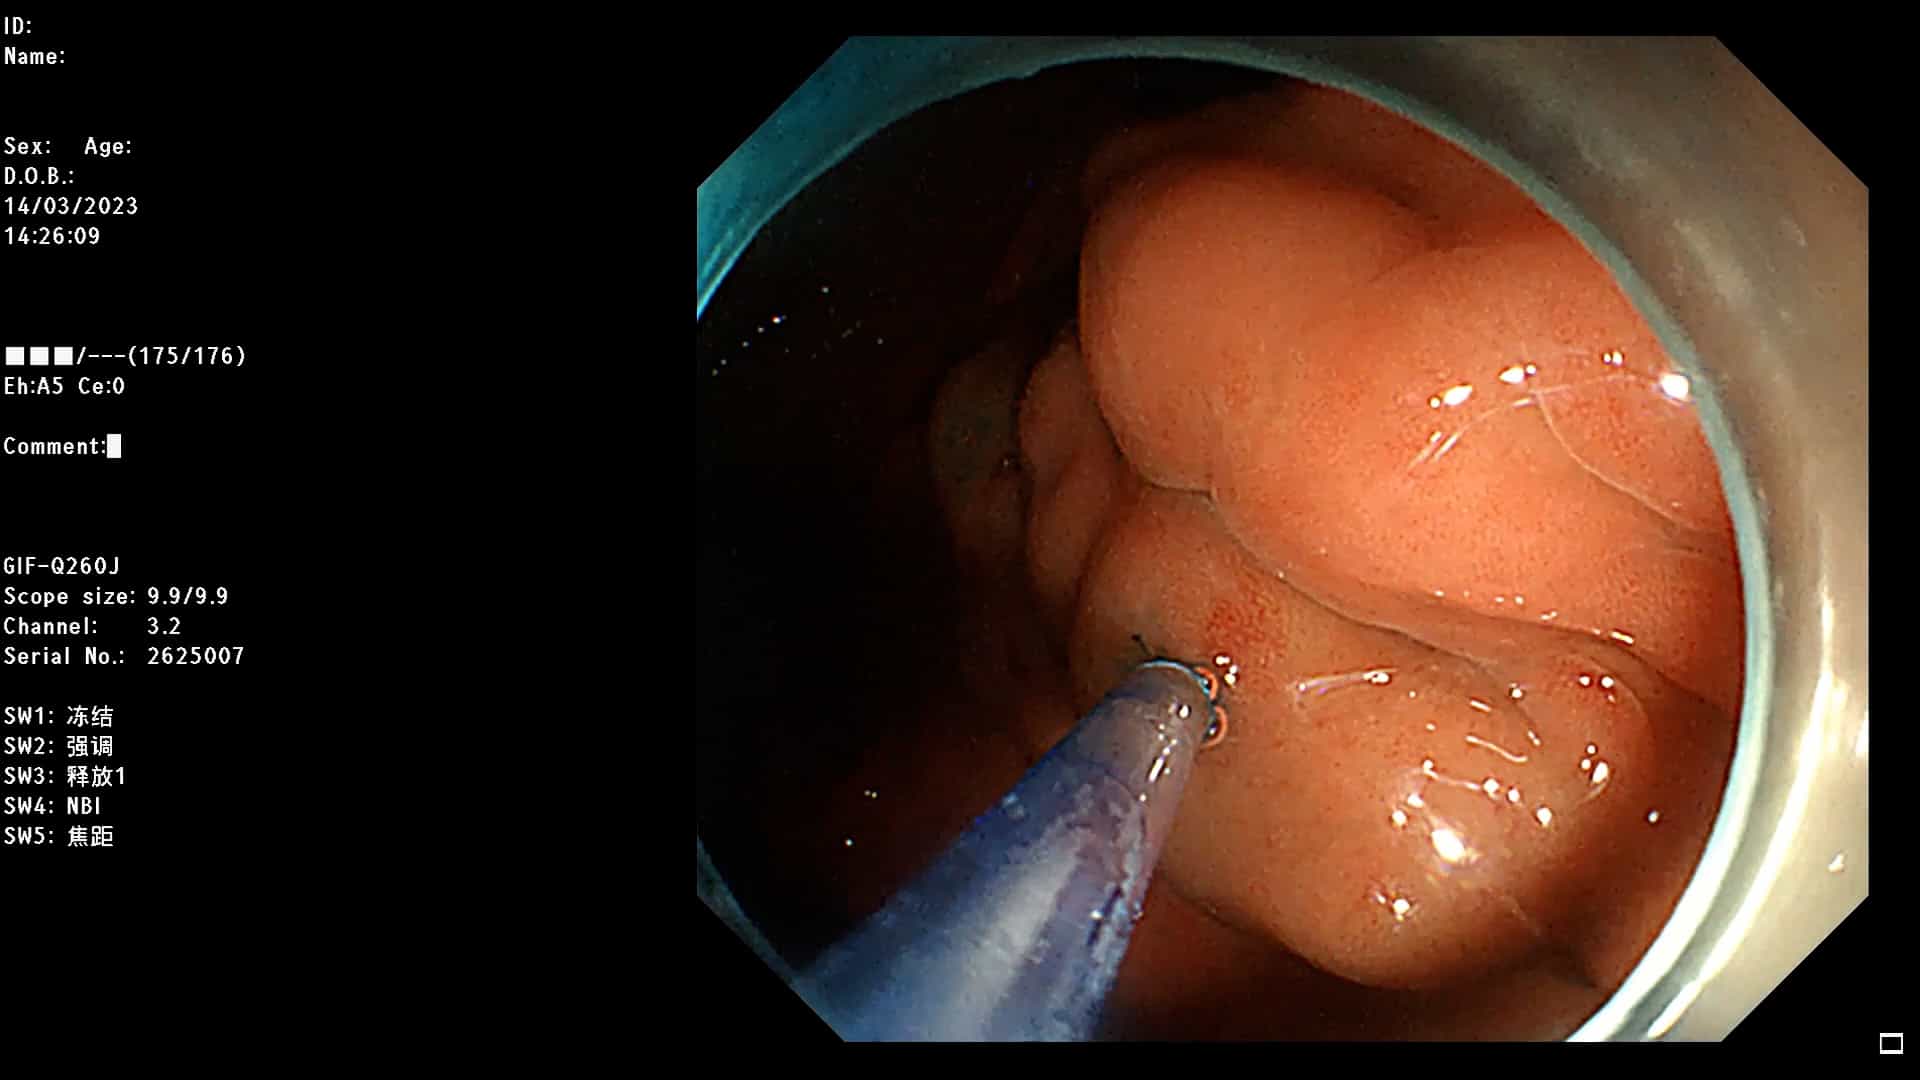
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Factors related to the failure of endoscopic injection therapy for bleeding gastric ulcer

Background:
Although endoscopic injection therapy is effective in controlling initial haemorrhage from peptic ulcer, between 10% to 30% of patients suffer rebleeding.
Aim:
To assess the factors that may predict the failure of endoscopic injection in patients bleeding from high risk gastric ulcer.
Subjects:
One hundred and seventy eight patients admitted for a gastric ulcer with a bleeding or a non-bleeding visible vessel were included.
Methods:
Patients received endoscopic therapy by injection for adrenaline and polidocanol. Twelve clinical and endoscopic variables were entered into a multivariate logistic regression model to ascertain their significance as predictive factor of therapeutic failure.
Results:
Eighty seven per cent (155 of 178) of patients had no further bleeding after endoscopic therapy. Endoscopic injection failed in 23 (13%) patients: 20 (12%) continued to bleed or rebleed, and three (1%) patients could not be treated because of inaccessibility of the lesion. Logistic regression analysis showed that therapeutic failure was significantly related to: (1) the presence of hypovolaemic shock (p = 0.09, OR 2.38, 95% CI: 0.86, 6.56), (2) the presence of active bleeding at endoscopy (p = 0.02, OR 2.98, 95% CI: 1.12, 7.91), (3) ulcer location high on the lesser curvature (p = 0.04, OR 2.79, 95% CI: 1.01, 7.69), and (4) ulcer size larger than 2 cm (p = 0.01, OR 3.64, 95% CI: 1.34, 9.89).
Conclusion:
These variables may enable identification of those patients bleeding from gastric ulcer who would not benefit from injection therapy.
Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease I: Introduction
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications