Prolonged induced hypertension in the management of incipient cerebral infarction

Surgical Neurology
|September 1, 1977
PubMed

Insights

Metaraminol effectively managed incipient cerebral infarction in a patient with a carotico-cavernous fistula by raising blood pressure. This intervention may aid in preventing post-operative complications for intracranial aneurysms and angiography.

Area of Science:

  • Neurology
  • Vascular Surgery
  • Pharmacology

Background:

  • Carotid-cavernous fistulas require surgical intervention, carrying risks of cerebrovascular complications.
  • Cerebral infarction is a potential post-operative complication following such procedures.
  • Maintaining adequate blood pressure is crucial for preventing ischemic events.

Observation:

  • A patient undergoing surgery for a carotid-cavernous fistula developed early signs of cerebral infarction.
  • Metaraminol was administered to therapeutically elevate blood pressure.
  • Treatment with metaraminol continued for eight days.

Findings:

  • The use of metaraminol successfully elevated the patient's blood pressure.
  • This intervention appeared to prevent the progression of the incipient cerebral infarction.
  • The patient's neurological status stabilized following blood pressure management.

Implications:

  • Metaraminol may be a valuable therapeutic agent for managing or preventing cerebral infarction in the post-operative period of neurovascular surgeries.
  • This approach could be relevant for patients recovering from intracranial aneurysm surgery or post-angiography complications.
  • Further research is warranted to establish the efficacy and safety of metaraminol in these specific clinical scenarios.

Related Concept Videos

Ischemic Stroke ll: Pathophysiology01:15

Ischemic Stroke ll: Pathophysiology

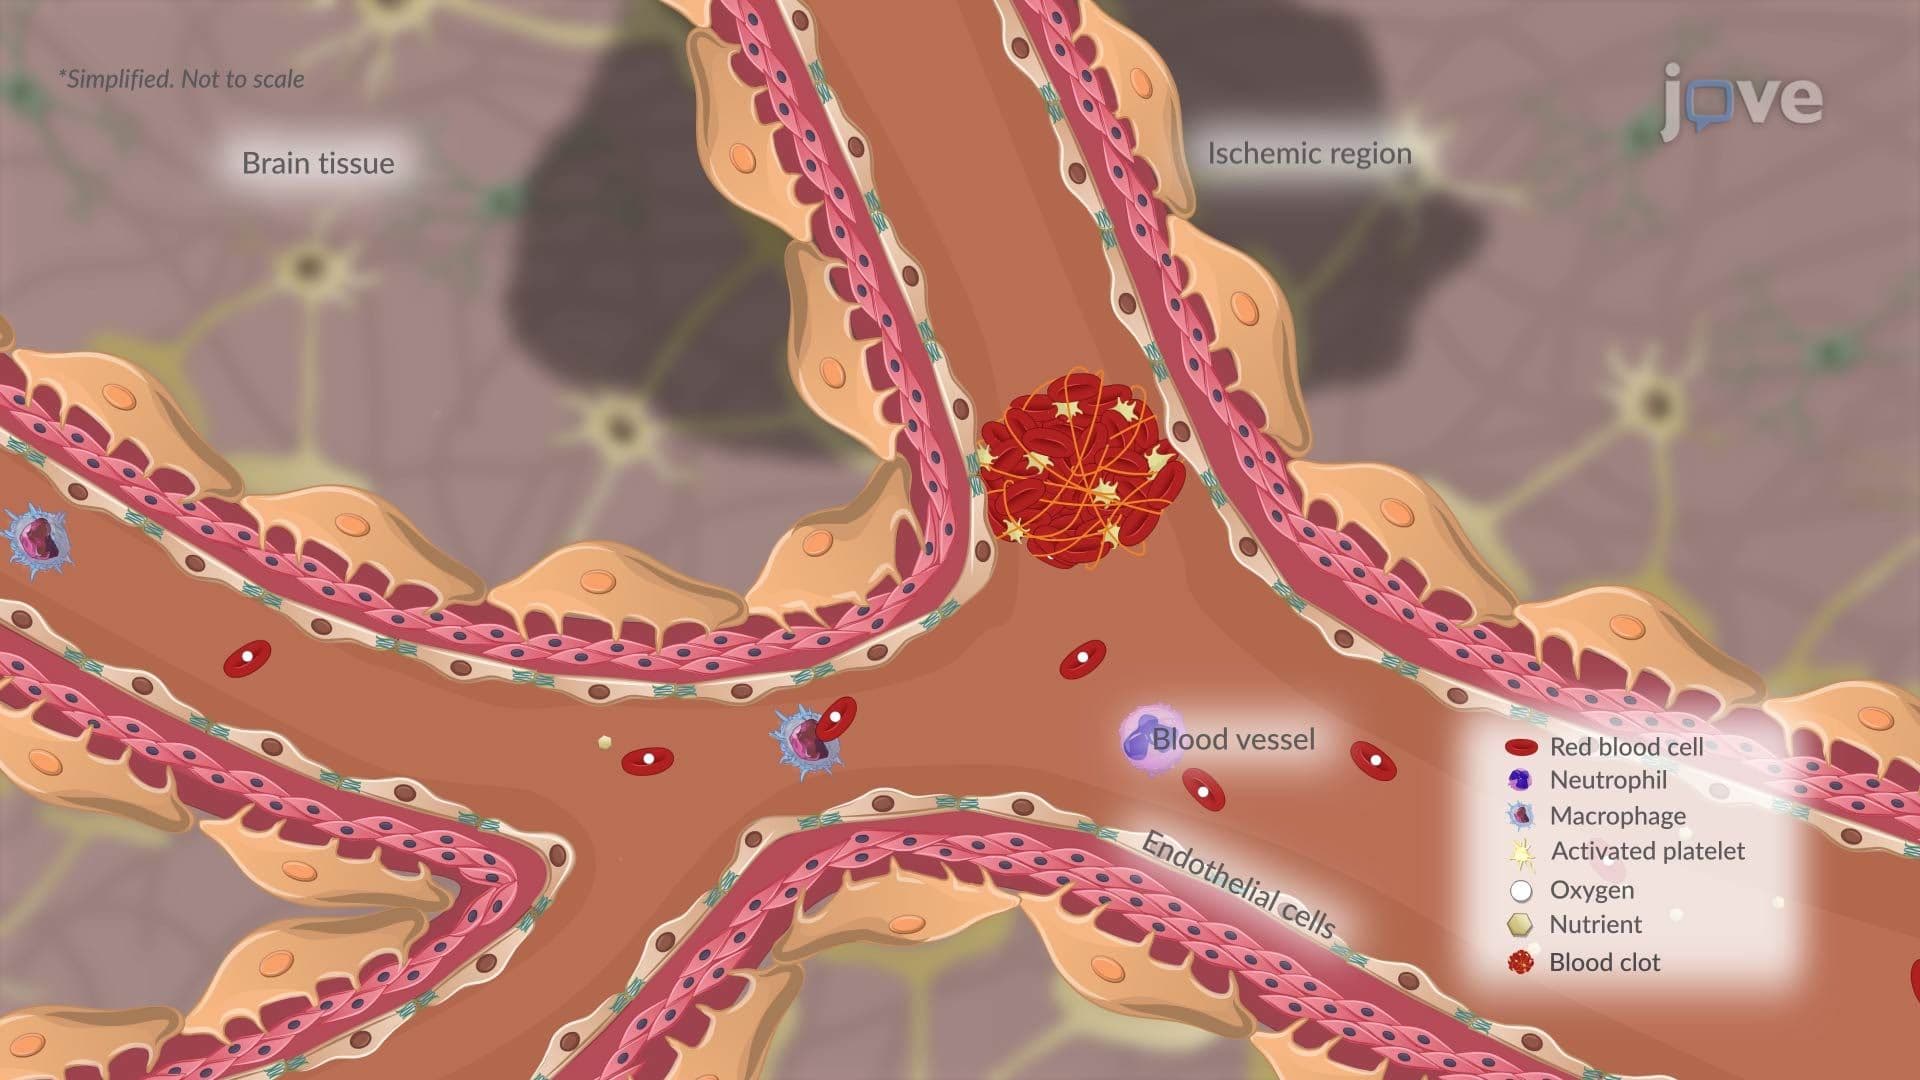
An ischemic stroke occurs when a cerebral blood vessel becomes obstructed, most often by a thrombus or embolus, interrupting the delivery of oxygen and glucose to brain tissue. Because neurons rely on continuous aerobic metabolism, energy failure begins within minutes of reduced perfusion. The region receiving the least blood flow becomes the infarct core, an area of irreversible cellular death. Surrounding this core lies the penumbra, a zone of hypoperfused but still viable tissue that is...
Hemorrhagic Stroke ll: Pathophysiology01:29

Hemorrhagic Stroke ll: Pathophysiology
A hemorrhagic stroke develops when a cerebral blood vessel ruptures, allowing blood to escape into the surrounding brain tissue, as in intracerebral hemorrhage (ICH), or into the subarachnoid space, as in subarachnoid hemorrhage (SAH). Because the skull is a rigid compartment, the sudden presence of extravascular blood rapidly increases intracranial pressure and compresses adjacent neural structures, leading to immediate tissue injury and impaired cerebral perfusion.Mass Effect and Primary...
Transient Ischemic Attack l: Introduction01:26

Transient Ischemic Attack l: Introduction

A transient ischemic attack (TIA) is a brief episode of neurological dysfunction caused by a temporary, focal reduction in cerebral blood flow. Although symptoms resemble those of an ischemic stroke, the interruption in perfusion is short-lived and does not cause permanent infarction. TIAs are clinically important because they often serve as early warning events for future stroke.Mechanisms of Transient Cerebral IschemiaTransient cerebral ischemia may arise through several mechanisms. One...
Increased Intracranial Pressure l: Introduction01:14

Increased Intracranial Pressure l: Introduction

Intracranial hypertension is a sustained elevation of intracranial pressure (ICP) above 22 mm Hg. In supine adults, normal ICP is ~7–15 mm Hg.The rigid, nonexpandable cranium contains three components—brain tissue, blood, and cerebrospinal fluid (CSF)—that total ~1,700 mL in a typical adult: 1,400 mL brain (~80%), 150 mL blood (~10%), and 150 mL CSF (~10%). According to the Monro–Kellie doctrine, total intracranial volume is effectively fixed. When one component expands, CSF and venous blood...
Increased Intracranial Pressure ll: Pathophysiology01:29

Increased Intracranial Pressure ll: Pathophysiology

Increased intracranial pressure (ICP) refers to a potentially life-threatening rise in pressure inside the skull. This usually happens when there is a major change in the volume of brain tissue, blood, or cerebrospinal fluid (CSF) — the three components inside the skull. According to the Monro-Kellie doctrine, if the volume of one component increases, the volumes of the other components must decrease to maintain normal pressure. If this does not happen, ICP rises.The process often begins with...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...


