Related Experiment Video
Updated: Aug 19, 2026

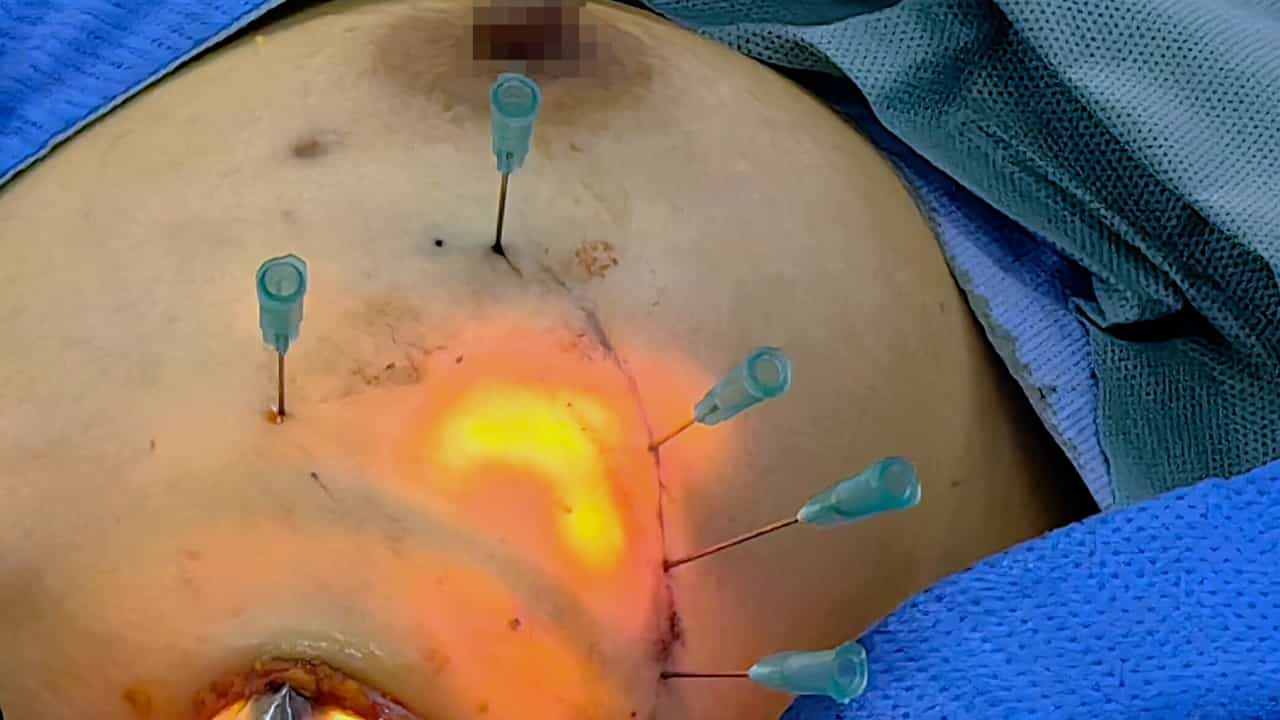
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Traditional and future management of nonpalpable breast cancer
1Deaconess Hospital and Harvard Medical School, Boston, Massachusetts 02215, USA.

Abstract:
Under the impact of mammographic screening, sizeable proportions of breast cancer patients today are nonpalpable with either a very small invasive breast cancer (T1a or T1b) or ductal carcinoma in situ. At the Deaconess Hospital in Boston between 1989 and 1993, 29 per cent of all invasive cancers were T1a or T1b (1 cm or smaller). The median maximum diameter of all invasive breast cancer in that 5-year period was only 1.5 cm. The dramatic downward slope of the maximum size clearly reflects the impact of widespread mammographic screening. Within a decade, the median maximum diameter of all invasive breast cancer will be 1 cm. Thus, modifications of contemporary therapy need to be investigated by trials, but they can be practiced in selected patients now. While standard therapy in 1996 includes routine radiotherapy with breast conservation, many small, low-grade, or mammographically discovered cancers can safely, efficiently, and with minimum morbidity be treated by local excision only with careful follow-up; highly selective use of systemic and local adjuvant therapies (i.e., radiotherapy) should also be practiced. Recent reports summarizing adjuvant radiotherapy and axillary dissection in invasive breast cancer do not recognize the changing presentation of invasive breast cancer under the impact of mammographic screening.