Related Experiment Video
Updated: Oct 13, 2026
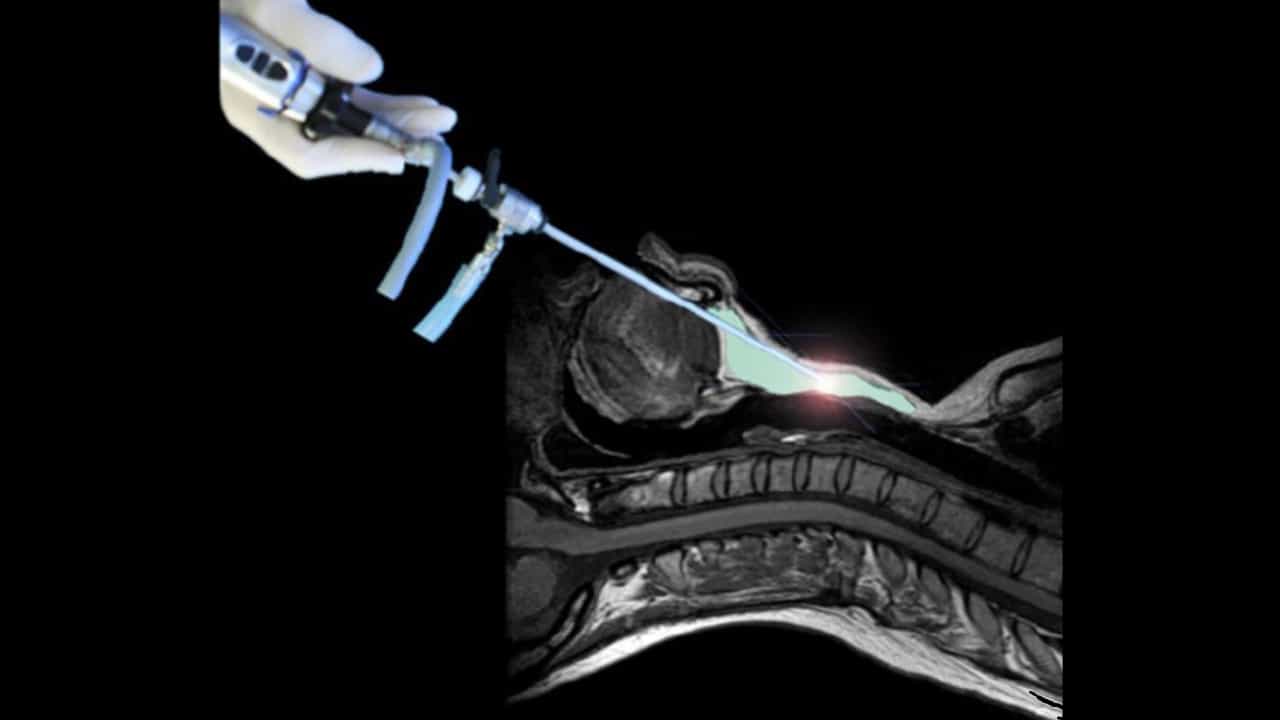
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Surgical complications after total thyroidectomy and resections for differentiated thyroid carcinoma

Abstract:
Differentiated thyroid carcinoma often has a favourable prognosis. However, there is no unanimity about the surgical procedure used. In this analysis we evaluated the surgical complications of 178 patients operated on for differentiated thyroid carcinoma during a 12-year period. 110 of the patients were operated in one session and 68 in two. Total thyroidectomy was performed in 106 patients and ipsilateral lobectomy together with contralateral subtotal resection in 72 patients. Tumour was bilateral or multicentric in 59 patients (33%). Hypoparathyroidism occurred in eight patients (4%), without differences between total thyroidectomies and lobectomy plus subtotal resections. Hypoparathyroidism tended to be more common after completion resection than after completion thyroidectomy (4/28 vs 1/40; P = 0.08). Accidental injury to the recurrent laryngeal nerve occurred in one patient (0.6%) during a contralateral resection. During a median follow-up of 4.5 years, tumour recurrence was detected in 22 patients (12%). In papillary carcinoma it was more common in patients who had underwent lobectomy plus contralateral resection than after total thyroidectomy (11/60 vs 3/88; P < 0.01). However, the median follow-up times were unequal. In conclusion, total thyroidectomy and even completion thyroidectomy is as safe as less radical lobectomy together with contralateral resection. Thus, total thyroidectomy should be offered to all patients with differentiated thyroid carcinoma until there is a reliable method to recommend for those patients who can be treated with less radical procedures.
Related Concept Videos
 01:24
Healing II: Complications
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:27
Goiter
 01:23
Hypothyroidism II: Pathophysiology