Related Experiment Video
Updated: Aug 31, 2026
Receptor Autoradiography Protocol for the Localized Visualization of Angiotensin II Receptors
Published on: June 7, 2016
The cardiac beta-adrenoceptor-mediated signaling pathway and its alterations in hypertensive heart disease
1Scienze Mediche, Universita degli Studi di Brescia, Italy.

Insights
Beta-adrenergic desensitization may drive the progression from compensated cardiac hypertrophy to heart failure in hypertension. Early intervention targeting sympathetic activity could prevent this transition.
Area of Science:
- Cardiology
- Molecular Biology
- Hypertension Research
Background:
- Hypertension-induced cardiac hypertrophy predicts heart failure development.
- Cellular markers for progression from compensated hypertrophy to failure remain unclear.
- Heart failure involves signal transduction defects, including adenylate cyclase desensitization.
Purpose of the Study:
- Investigate cellular mechanisms linking hypertension, cardiac hypertrophy, and heart failure.
- Determine the role of beta-adrenergic desensitization in the transition to heart failure.
- Explore potential therapeutic targets for preventing heart failure in hypertensive patients.
Main Methods:
- Review of studies on rat models of hypertension and heart failure.
- Analysis of signal transduction pathways, including G protein alterations and beta-adrenoceptor function.
- Comparison of mechanisms in acquired versus genetic hypertension models.
Main Results:
- Heterologous adenylyl cyclase desensitization occurs in hypertensive heart disease, similar to heart failure.
- Common findings include Gi protein alterations and beta-adrenoceptor downregulation across models.
- Sympathetic activation, rather than genetic defects, is the likely mechanism for desensitization in established hypertension.
Conclusions:
- Beta-adrenergic desensitization may contribute to the progression from hypertrophy to heart failure.
- Further research is needed to determine if hypertensive patients developing heart failure are prone to desensitization.
- Early intervention to reduce sympathetic activity may prevent or delay the transition to overt heart failure.
Abstract:
Hypertension-induced cardiac hypertrophy is a predictor of the development of cardiac failure. It is unknown which cellular markers contribute to the progression from compensated hypertrophy to failure. In heart failure, several signal transduction defects leading to adenylate cyclase desensitization have been demonstrated, such as beta-adrenoceptor downregulation, increase of inhibitory G protein expression, and uncoupling of beta-adrenergic receptors, presumably by an increase of receptor kinase activity. In hypertensive heart disease, most studies have been performed in rat models of hypertension. As in heart failure, heterologous adenylyl cyclase desensitization occurs. The mechanisms are often different between the heterogeneous models for acquired and genetic hypertension, but Gi protein alterations and beta-adrenoceptor downregulation have been observed frequently. The underlying mechanism for desensitization is most likely a sympathetic activation in established hypertension rather than genetic alterations of signal transduction proteins. The data available suggest that beta-adrenergic desensitization could represent a mechanism that contributes to the progression from hypertrophy to failure. The key question remains whether those hypertensive patients who develop heart failure are more prone to beta-adrenergic desensitization or whether early intervention to reduce sympathetic activity is more effective in preventing or delaying the transition from compensated hypertrophy to overt failure.
Related Concept Videos
 01:26
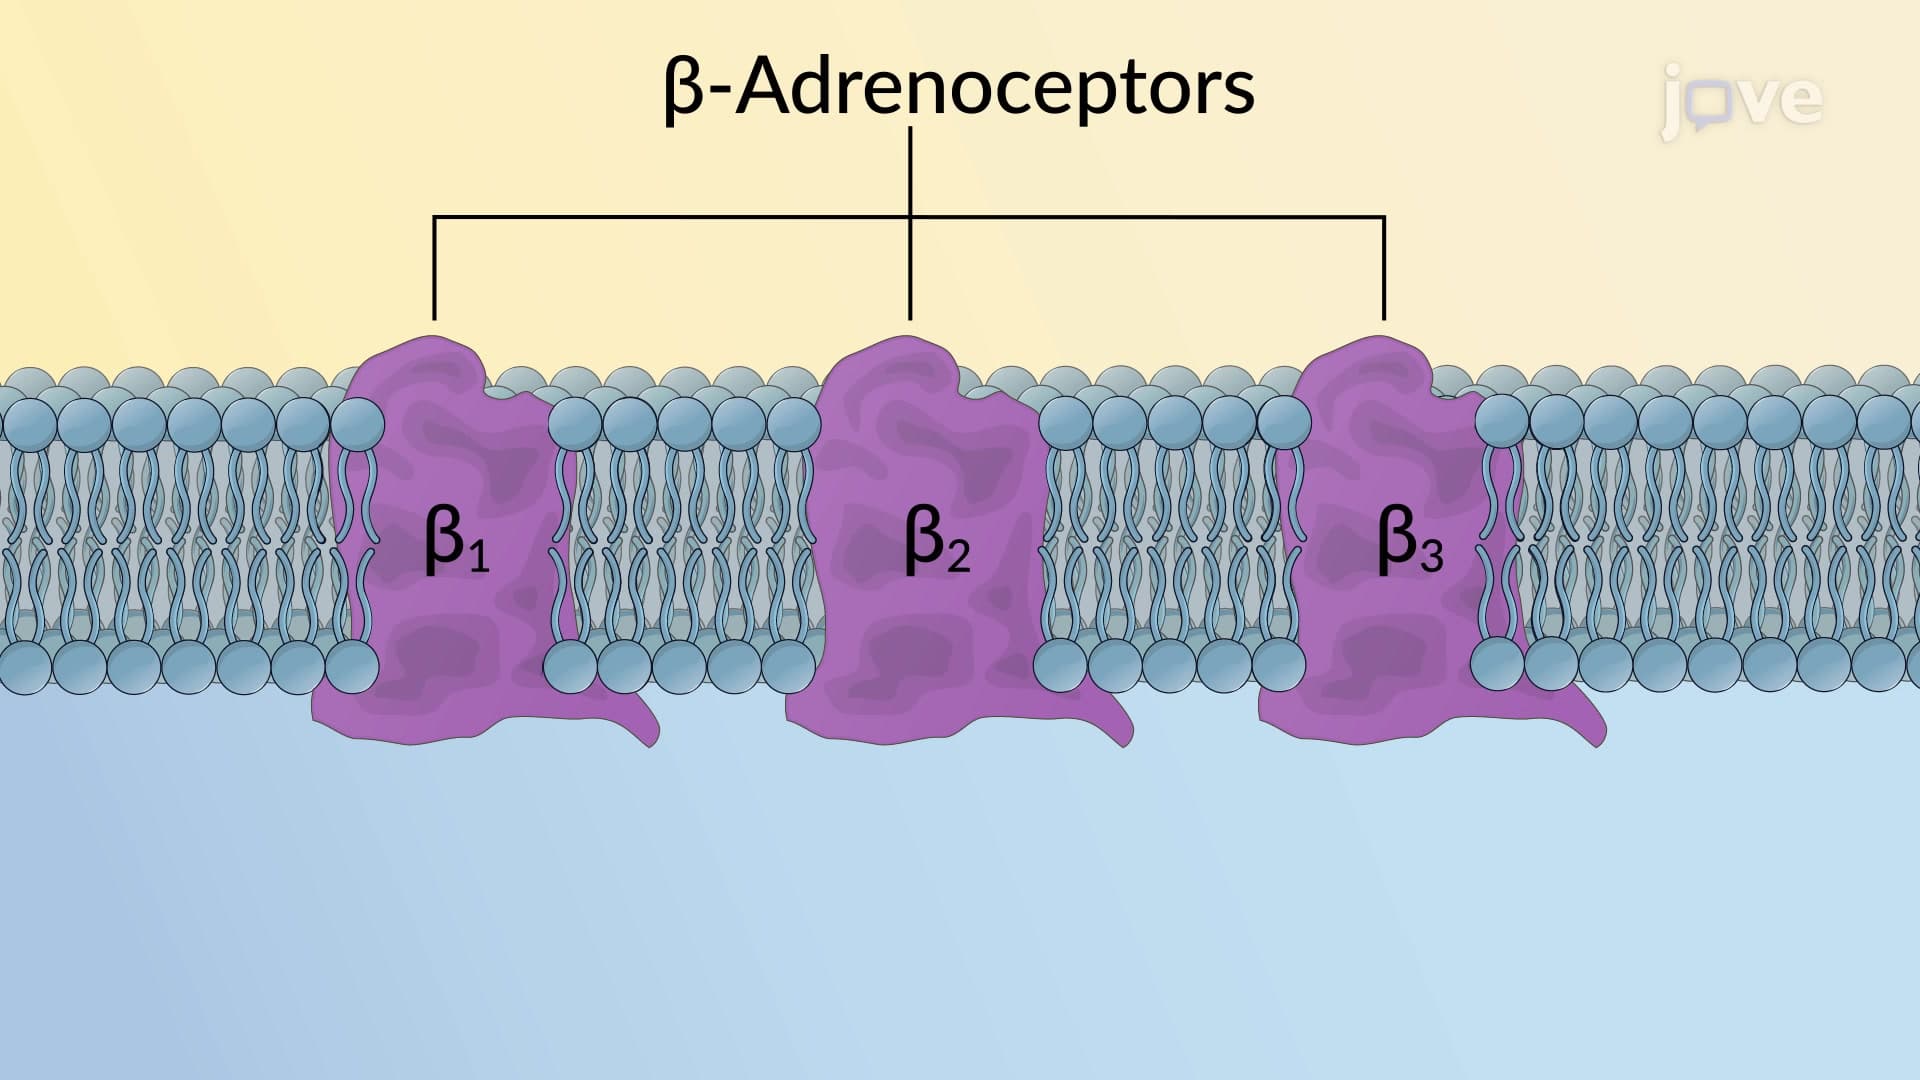
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
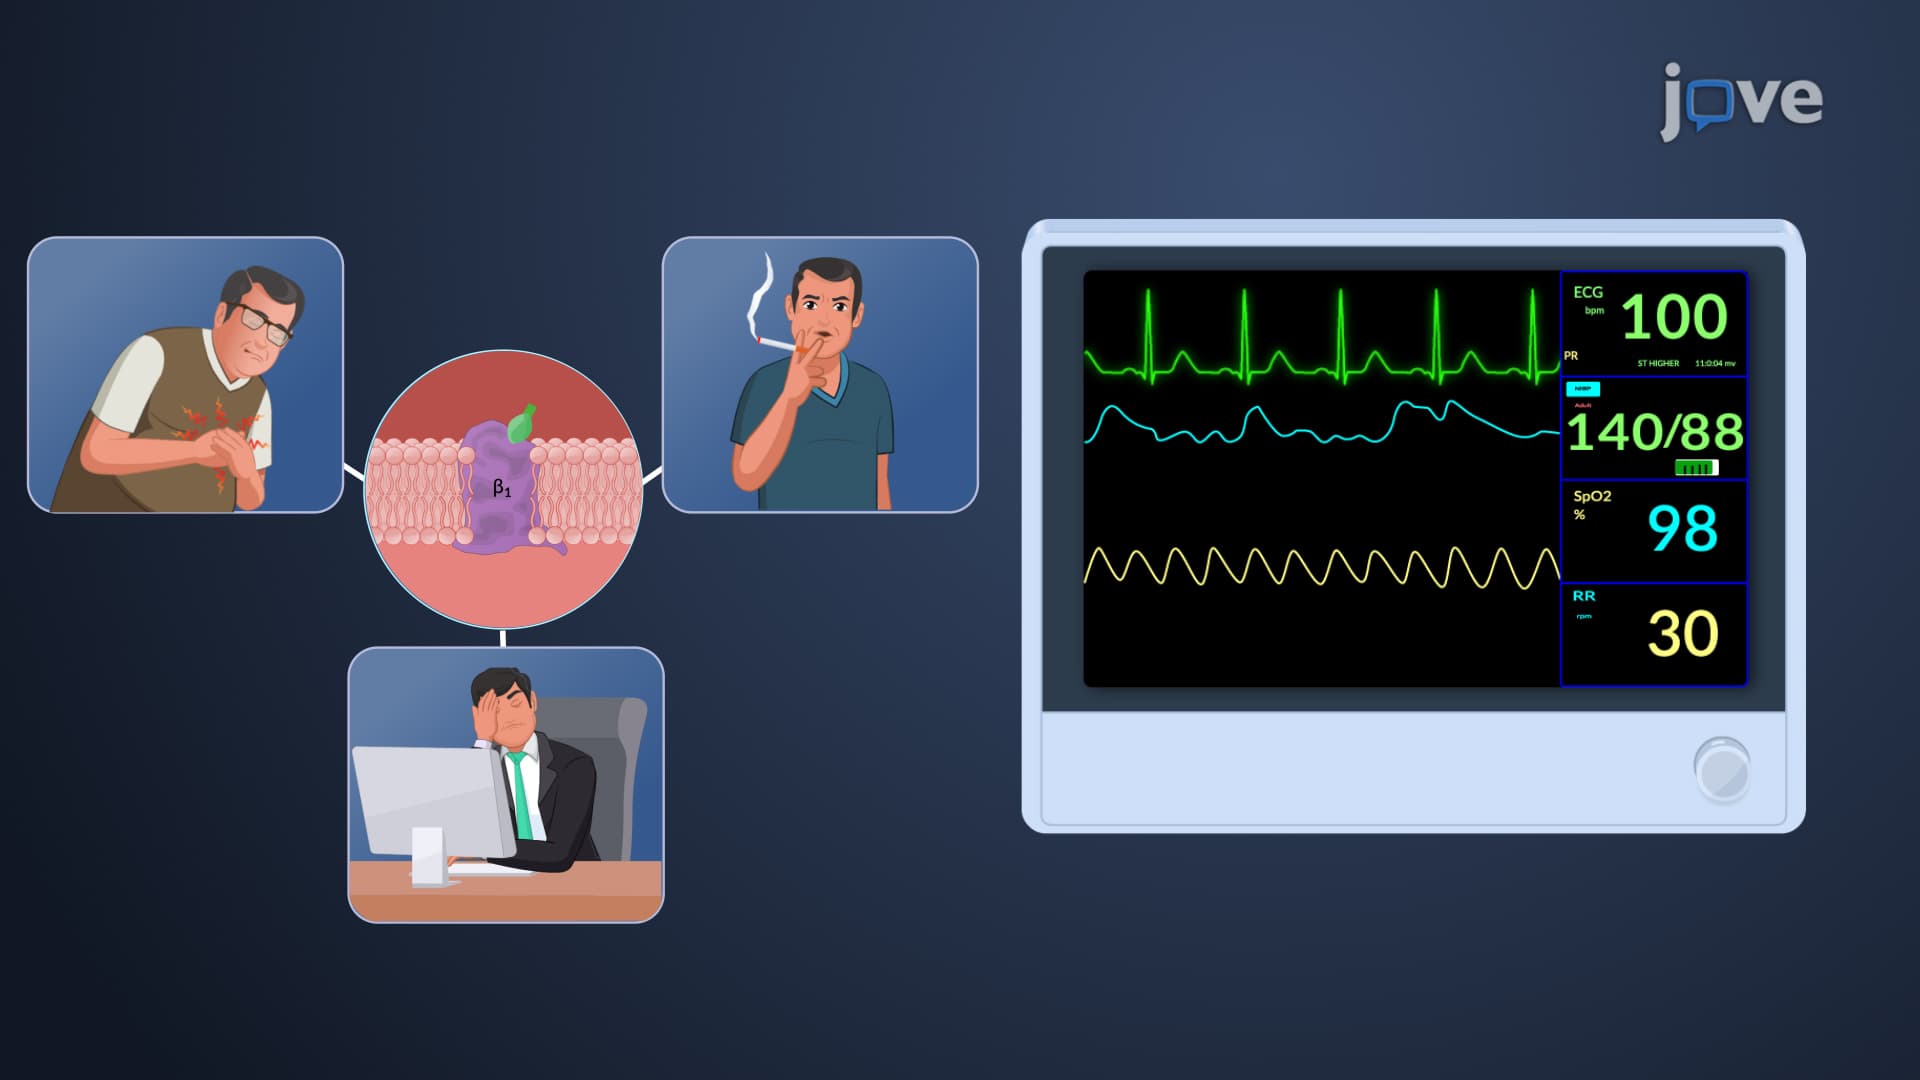 01:17
Antihypertensive Drugs: Action of β1 Blockers
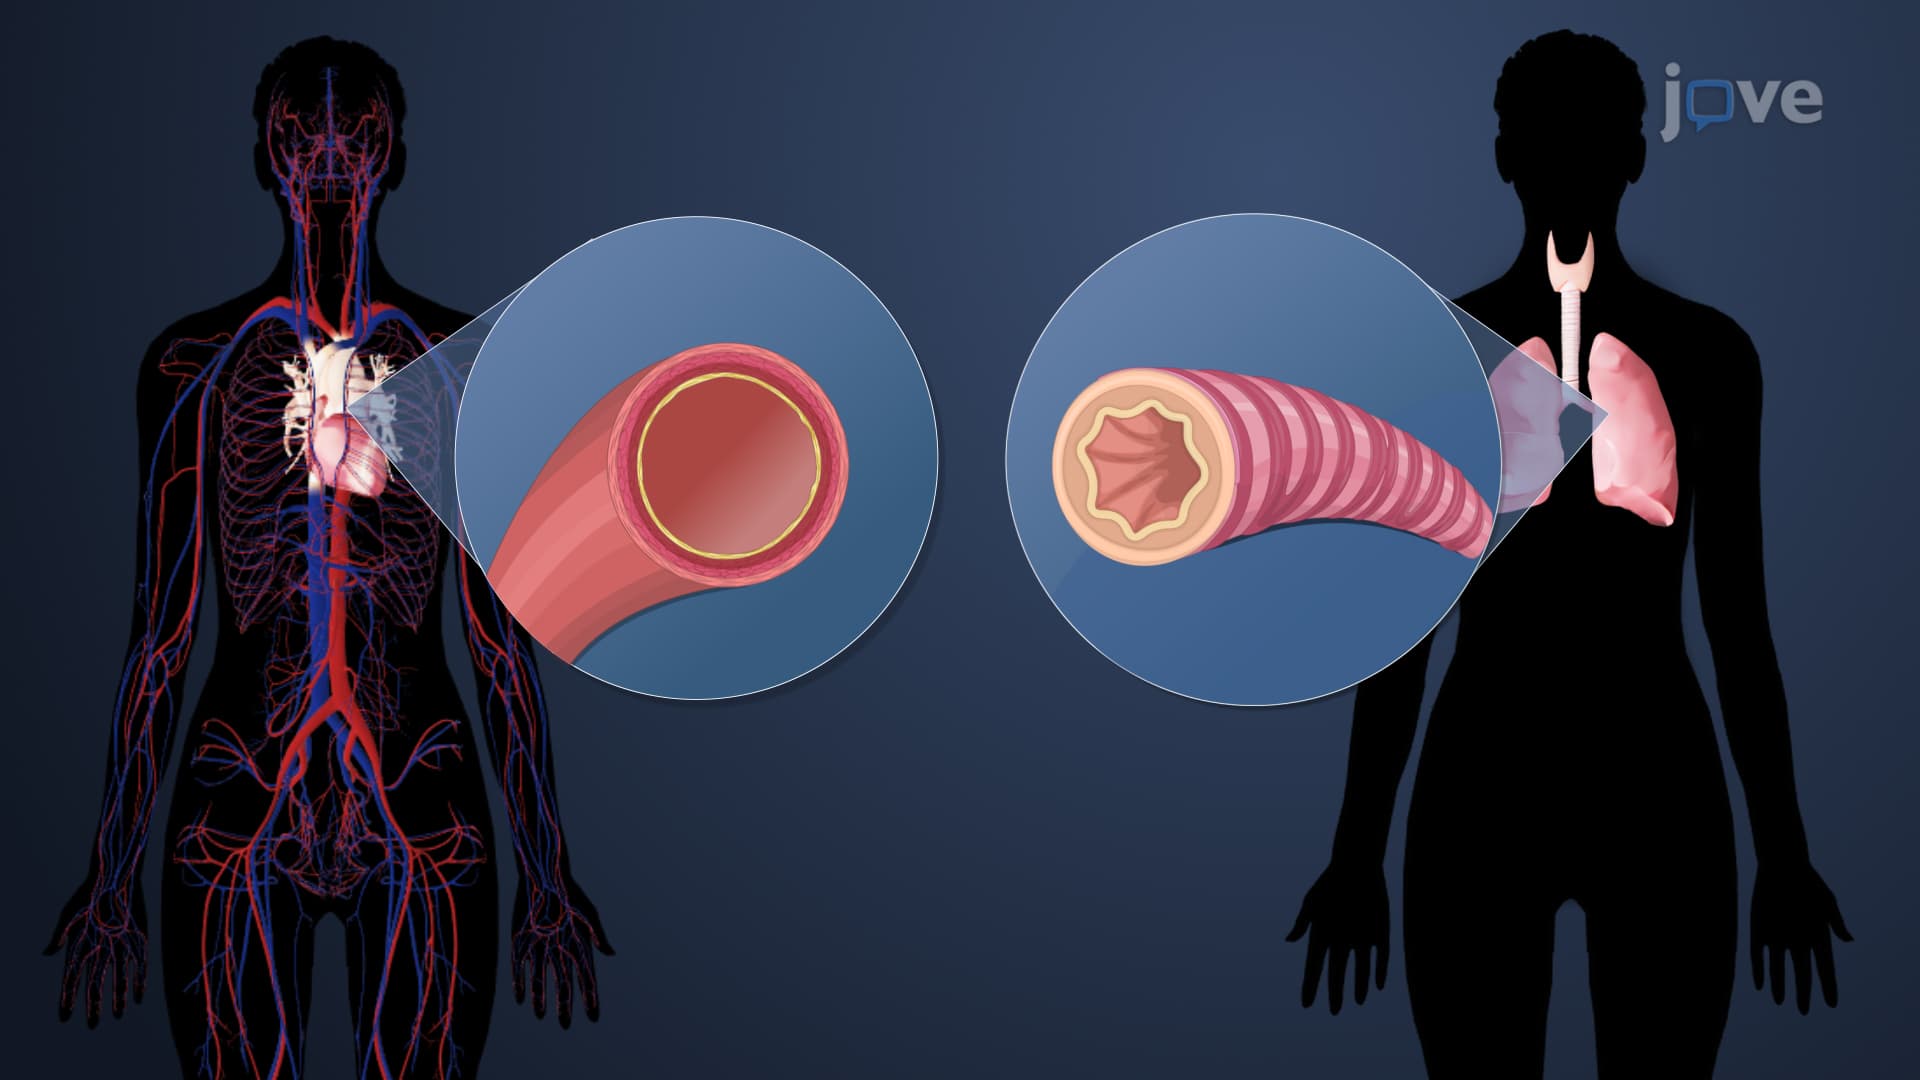 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:29
Heart Failure II: Pathophysiology