[Current ascites therapy]
Related Experiment Video
Updated: Nov 2, 2026
Endoscopic Vacuum Therapy for the Treatment of Anastomotic Leakage after Total Gastrectomy with Esophagojejunostomy
Published on: August 22, 2025

Abstract:
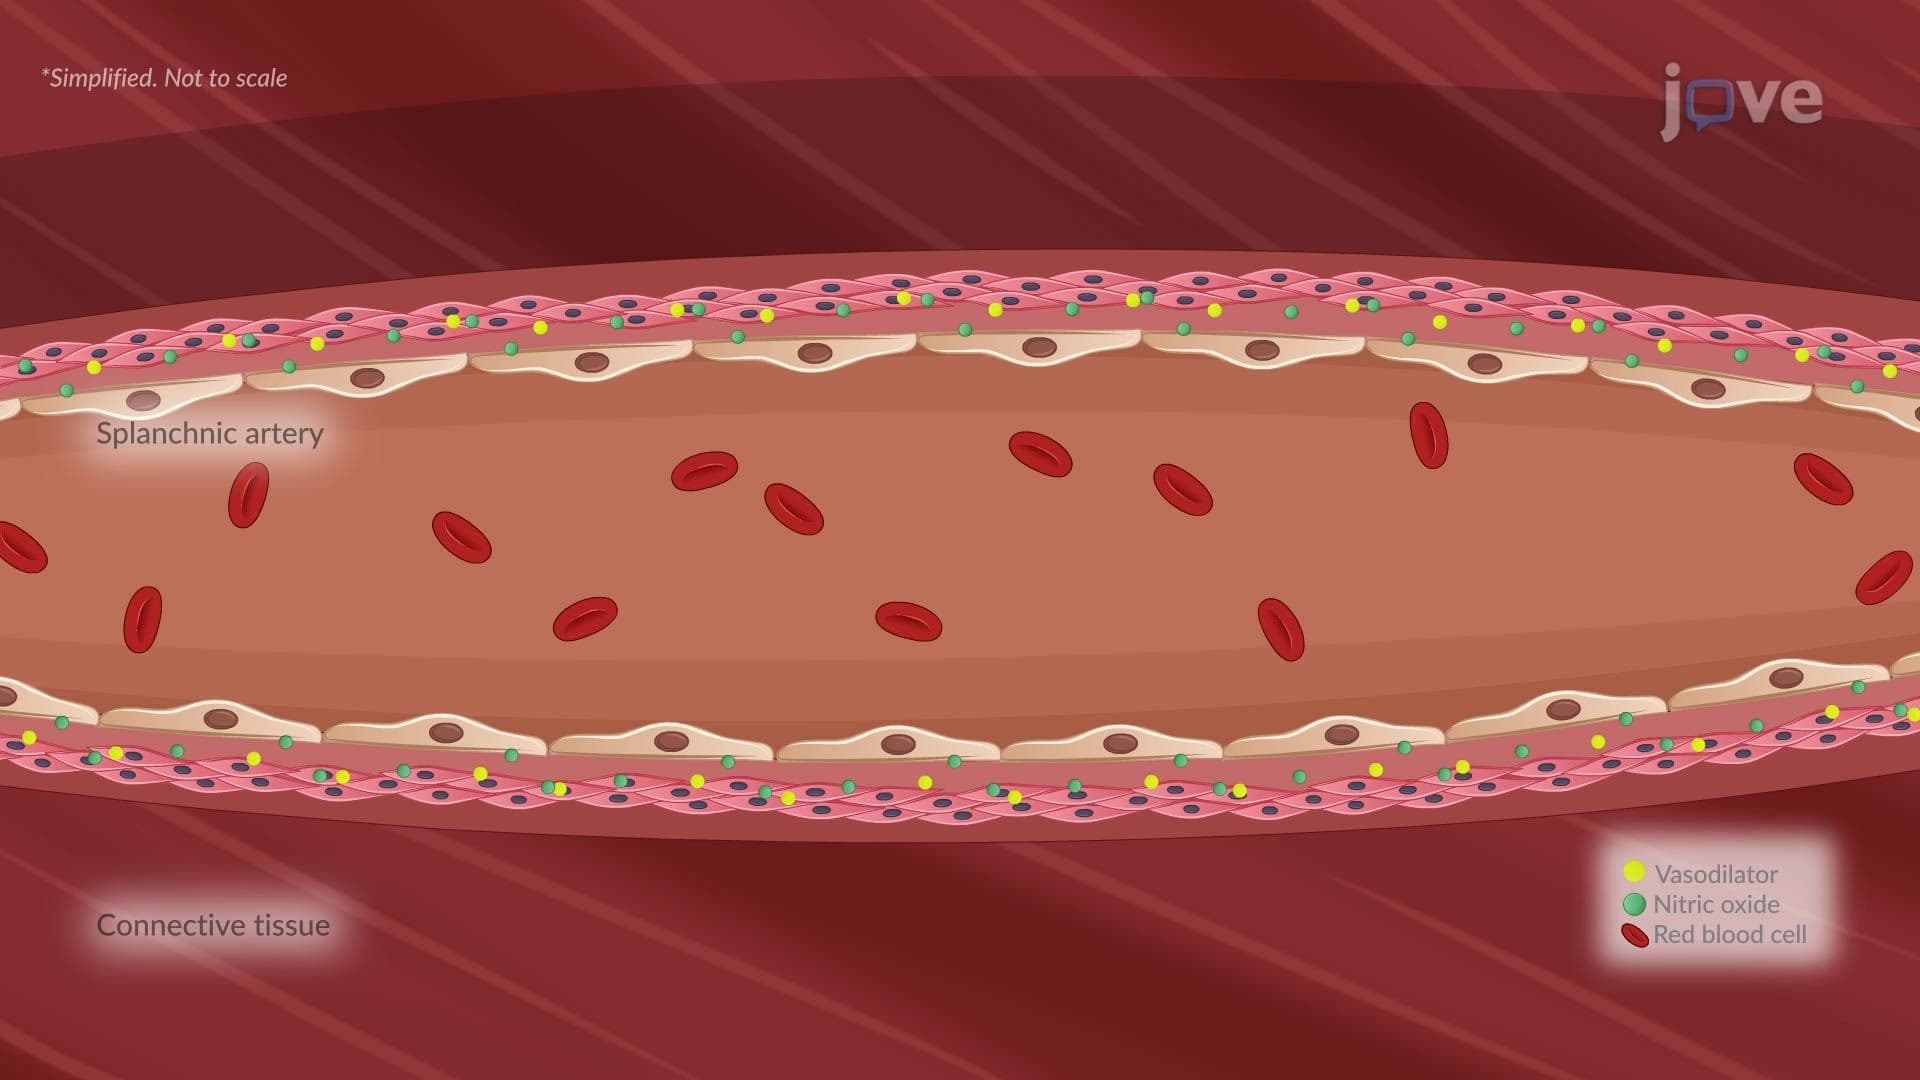
Ultrasonography detects ascites easily even in trace amounts. 80% of the cases are caused by hepatic disease, in the remaining 20% cancer, inflammation, pancreatic, renal, or cardiac disease can be found. The underlying disease should be investigated by few inexpensive laboratory test from serum, urine and ascites and by abdominal sonography. Hepatic ascites is caused by portal hypertension and disturbances of humoral factors. Sodium retention, peripheral, vasodilation, hyperdynamic circulation and progressive renal vasoconstriction lead to a stepwise deterioration of patients condition. Treatment with diuretics (furosemide, torsemide, or xipamide and spironolactone) and sodium-restriction (< 60 mval per day) control 85-90% of the cases with hepatic ascites. If this regimen fails, non-compliance, spontaneous bacterial peritonitis, hyponatremia or additional complications such as renal failure, Budd-Chiari syndrome or tumor should be considered. Ten to 15% of the patients develop refractory ascites and finally hepatorenal syndrome and have a poor prognosis. Early liver transplantation should be considered. Large volume paracentesis with albumin substitution is a therapeutic option in these patients. The transjugular intrahepatic portosystemic stent-shunt (TIPS) may be superior for patients with concurrent esophageal varices or hepatorenal syndrome. If TIPS is considered the patient should be referred to an experienced center. The peritoneo-venous shunt is restricted to rare indications. In the future, new drugs such as antagonists of endothelins or of the antidiuretic hormone may offer new therapeutic options.
Related Concept Videos
 01:19
Ascites
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:22
Heart Failure VI: Adjunct Therapies
 01:24
Nephrotic Syndrome III : Nursing Management
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:22
Aneurysm IV: Nursing Management