A practical guide to the management of bleeding ulcers
Related Experiment Video
Updated: Oct 24, 2026
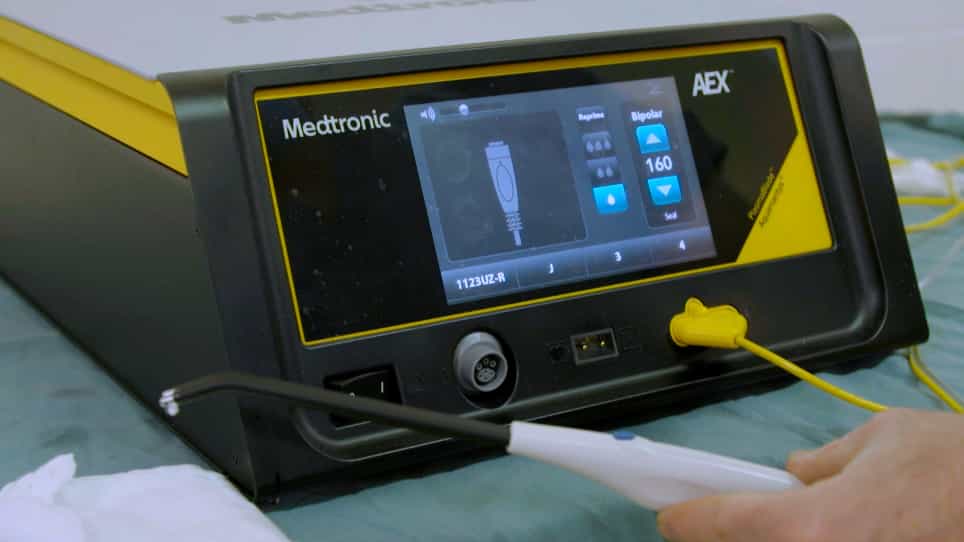
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
1Department of Gastroenterology, Hospital de la Santa Creu i Sant Pau, Barcelona, Spain.

Abstract:
In patients with acute haemorrhage from peptic ulcers, emergency endoscopy should be performed as soon as safely possible after resuscitation to detect the bleeding lesion, to define stigmata of recent haemorrhage, and to perform endoscopic therapy when required. Subsequent management will be determined by the results of diagnostic endoscopy. Ulcers with a clean base or with flat blood spots will not require endoscopic therapy: the patient can be discharged early after resuscitation and the institution of treatment to promote ulcer healing. Ulcers in which endoscopy discloses active arterial bleeding or a nonbleeding visible vessel should be treated, as these signs denote a high risk of an unfavourable outcome, and the efficacy of endoscopic therapy has been demonstrated when these signs are identified. In keeping with the available data, antisecretory therapy, vasoconstrictor drugs and tranexamic acid cannot be recommended as treatment for an acute ulcer bleeding episode. On the other hand, it has been shown in controlled trials that endoscopic therapy significantly reduces the incidence of further bleeding and the requirement for emergency surgery in patients with ulcers with active arterial bleeding or a nonbleeding visible vessel. Meta-analyses of these studies have also shown a significant decrease in mortality with endoscopic therapy. Among the available endoscopic methods for haemostasis, injection therapy is a valid choice since its efficacy has been similar to that of thermal methods in comparative studies, while its simplicity, tolerability and low cost are great advantages. A second endoscopic treatment can be attempted in patients with further haemorrhage after the initial endoscopic therapy, and permanent haemostasis can be achieved in half of these cases. However, the decision to perform this second endoscopic treatment should be taken individually, as the routine use of such a procedure could increase mortality by delaying surgery.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications