Related Experiment Video
Updated: Aug 15, 2026
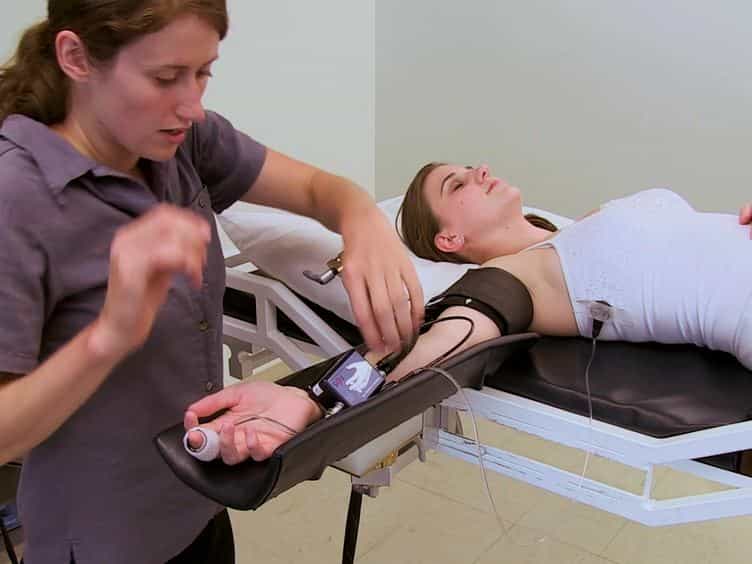

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Detecting incipient vasovagal syncope: intraventricular acceleration
M Brignole1, C Menozzi, G Corbucci
1Section of Arrhythmology, Ospedali Riuniti, Lavagna, Italy.

Abstract:
The peak endocardial acceleration (PEA) caused by ventricular isometric contraction can be measured with an implantable microaccelerometer located inside the tip of a normal unipolar pacing lead. It has been shown that PEA correlates with myocardial contractility and the maximum rate of rise of ventricular pressure (peak dP/dt) of the left ventricle. A PEA measuring system was temporarily inserted into the apex of the right ventricle in seven patients affected by syncope of uncertain origin. Each patient subsequently underwent 60 degrees tilt testing with three different protocols: without pharmacological challenge (baseline); potentiated with sublingual trinitroglycerin (at a dose of 0.3 mg); and with isoproterenol infusion (at a dose of 3 micrograms/min). Each phase lasted 20 minutes. Syncope was induced in 1 patient during the baseline phase, in 3 patients during the trinitrin phase, and in 4 patients during the isoproterenol phase. Six patients had a negative response during the baseline phase and served as a control group. From the beginning of upright posture to the time of maximum heart rate, PEA increased by about the same amount in both positive and negative patients, but absolute values were from two- to three fold higher with isoproterenol (from 1.2 +/- 0.5 G to 1.6 +/- 0.8 G, from 0.8 +/- 0.2 G to 1.2 +/- 0.4 G, and from 2.8 +/- 1.8 G to 3.6 +/- 1.8 G, respectively, for negative, positive baseline or trinitrin, and positive isoproterenol tests). At the time of syncope, PEA values fell to baseline values. PEA changes were inversely correlated with blood pressure changes and directly correlated with heart rate changes. Thus, tilt induced syncope occurred both at low and high levels of left ventricular contractility. Whether spontaneous syncopes occur at low or high PEA behavior remains to be established. Since heart rate correlates well with changes in PEA and is far easier to measure, it is unlikely that a PEA measurement system or, in general, a contractility-based system, might become an ideal sensing parameter for the introduction of devices to combat vasovagal syncope.

Related Concept Videos
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for:
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:30
Dysrhythmias V: Evaluating Dysrhythmias