Related Experiment Video
Updated: Sep 15, 2026

The 4 Mountains Test: A Short Test of Spatial Memory with High Sensitivity for the Diagnosis of Pre-dementia Alzheimer's Disease
Published on: October 13, 2016
Cognitive models that predict physician judgments of capacity to consent in mild Alzheimer's disease
D C Marson1, L Hawkins, B McInturff
1Department of Neurology, University of Alabama at Brimingham, 35294, USA.

Objective:
To identify cognitive measures that predict consent capacity of normal and demented older adults as judged by experienced physicians. This study is a companion to the physician competency judgment research reported in this issue.
Design:
Predictor models for competency judgments of individual physicians were developed using independent patient neuropsychological test measures and discriminant function analyses (DFA).
Setting:
University medical center.
Participants:
Subjects were 16 normal older controls and 29 patients with mild AD (MMSE > or = 20). Five experienced medical center physicians were recruited as competency decision-makers.
Measurements:
Subjects were videotaped responding to a standardized consent capacity interview (SCCI) designed to evaluate capacity to consent to treatment. Interview subjects were also independently administered (off videotape) a battery of neuropsychological measures theoretically and empirically linked to competency function. Study physicians blinded to subject diagnosis and neuropsychological test performance individually viewed each SCCI videotape and made a judgment of competent or incompetent to consent to treatment. Stepwise DFA identified neuropsychological predictors of each physician's competency judgments for the full sample (N = 45). Classification DFAs determined how accurately these predictor models classified competency outcomes assigned by the individual physician.
Results:
Cognitive models differed across individual physicians and were related to stringency of judgments for AD patients. Under stepwise DFA, delayed verbal recall (R2 = .57, P < .0001) predicted judgments of Physician 1 (incompetency rate of 90% for AD patients), short term verbal recall (R2 = .43, P < .0001) predicted judgments of Physician 2 (incompetency rate of 52%), phonemic word fluency (R2 = .27, P < .001) predicted judgments of Physician 3 (incompetency rate of 24%), and visuomotor tracking/sequencing (R2 = .31, P < .001) predicted judgments of Physician 4 (incompetency rate of 14%). (No predictor model was available for Physician 5 as this physician found all subjects to be competent). These single predictor solutions correctly classified 93%, 87%, 87%, and 96% of cases for Physicians 1-4, respectively. Use of two predictor solutions achieved successful classification rates between 98% and 100%.
Conclusions:
We identified two cognitive models of consent capacity as judged by physicians: (1) verbal recall and (2) simple executive function. The verbal recall model predicted judgments of physicians likely to find mild AD patients incompetent, whereas the executive function model predicted judgments of physicians likely to find mild AD patients competent. Assessment of verbal recall and simple executive functions may provide important information in the clinical evaluation of capacity to consent to treatment.


Related Concept Videos
 01:30
Cognitive Enhancers: Cholinesterase Inhibitors and NMDA Receptor Antagonists
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:30
Dementia
The progression of dementia is generally gradual.
 01:30
Cognitive Development During Adulthood
 01:29
Alzheimer Disease l: Introduction
 01:22
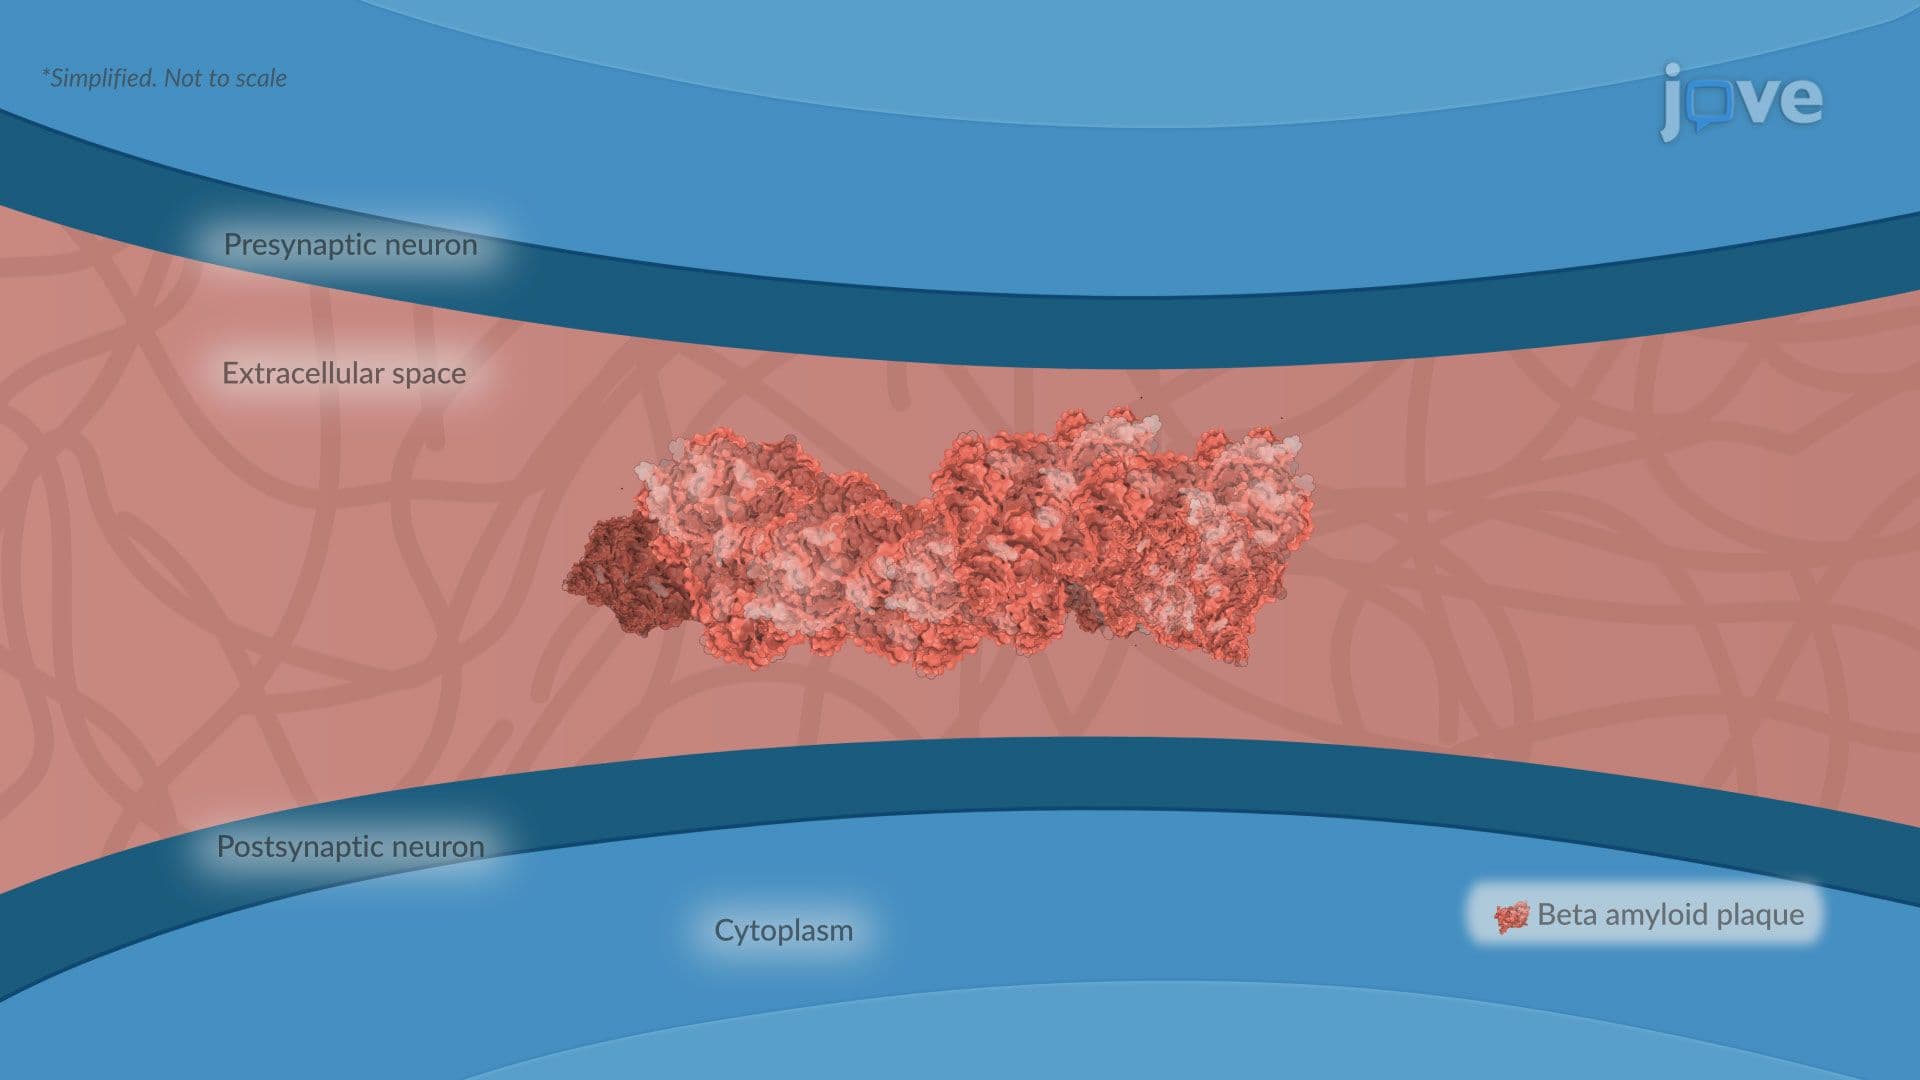
Dementia l: Introduction