Related Experiment Video
Updated: Aug 13, 2026
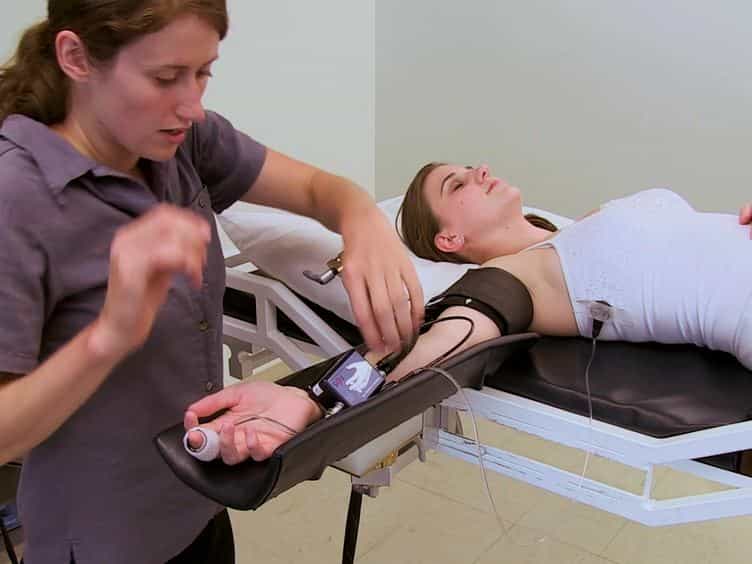

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
[Orthostatic hypotension and postprandial hypotension]
1Department of Neurology, Saitama Medical School.

Abstract:
Both orthostatic hypotension (OH) and postprandial hypotension (PPH) may result from lesions in any part of the baroreflex arc, which comprises central autonomic network, afferent pathways, efferent pathways, and neuro-vascular junction. Nonetheless, most attention has been centered to the efferent pathways to date. In the present report, I discussed on the contribution of neuro-vascular junction and central autonomic network to the development of OH and PPH. I also referred to the essential difference in pathophysiology between OH and PPH. (1) Difference between OH and PPH: Essential difference is in triggers inducing the initial blood pressure fall. The trigger in OH is gravity, while that in PPH is abnormal release of vasodilative gastroenteric peptides; the former is equally delivered to all persons living on earth, but the latter varies from person to person. (2) Neuro-vascular junction: Previous studies, in which catecholamine drip infusion tests were carried out on patients with OH, suggested that all of cardiovascular alpha-, beta 1, and beta 2 adrenoceptors gain denervation supersensitivity in OH. This view does, however, underestimate the blood pressure buffering effect of baroreflex. Because long-standing alteration in blood pressure by drip infusion of catecholamine necessarily provokes baroreflex, it is reasonable that augmented cardiovascular responses in OH are largely due to baroreflex failure. We performed bolus infusion tests of noradrenaline and isoprenaline on patients with OH, and found that alpha-adrenoceptor-mediated rise in blood pressure was comparable to control, beta 1-mediated increase in heart rate was blunted, and beta 2-mediated fall in blood pressure was enhanced in OH. It is, therefore, likely that beta 2-mediated vasodilation exceeds alpha-mediated vasoconstriction in OH. In such condition, noradrenaline may produce a paradoxical hypotensive effect, which contributes to the development of OH or PPH. (3) Central autonomic network (CAN): Clinical symptoms due to lesions within CAN are usually not manifested when the efferent sympathetic pathways are highly impaired, as in multiple system atrophy. Some variants of OH and PPH may result from lesions within CAN, however. For example, we have experienced a case of sympathotonic OH associated with herpes simplex encephalitis, in which the efferent pathways do not seem to be involved.


Related Concept Videos
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart beats)...
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:26
Cardiac Catheterization IV: Nursing Management
 01:29
Hypertension II: Pathophysiology
 01:26
Hypoglycemia