Related Experiment Video
Updated: Aug 13, 2026

Advanced Imaging of Lung Homing Human Lymphocytes in an Experimental In Vivo Model of Allergic Inflammation Based on Light-sheet Microscopy
Published on: April 16, 2019
Idiopathic interstitial lung disease: anatomoradiologic pathogenesis
1Servizio di Anatomia Patologica, Casa di Cura S. Anna, Brescia, Italy.

Abstract:
Interstitial lung disease encompasses a large number of clinical disorders that affect the epithelium, the endothelium or both cell surfaces of alveolar wall and satellite structures including terminal and respiratory bronchioles. Causative factors are over 200 from bacteria, fungi, viruses, protozoans, to collagen disease, hypersensitivity and inorganic pneumoconiosis. Clinical and histological findings of open lung and transbronchial biopsies from 50 patients are reported, 18 patients were affected by diffuse alveolar damage (DAD), 15 patients by usual interstitial pneumonia (UIP), 8 patients by non specific interstitial pneumonia-fibrosis (NSIP-F), 9 patients by bronchiolitis obliterans organizing pneumonia (BOOP) correlated with conventional chest radiography in 30 patients and with HRCT in 31 patients. Interstitial lung disease other than histiocytosis X share anatomoradiologic features indicative for activity, chronic progression, chronic quiescence, chronic advanced and irreversible disease. In general, the histologic features correlate with radiographic patterns and even if radiologic findings do not always supply definitive diagnosis, some HRCT patterns are highly suggestive and usually classified into 4 categories: normal; with ground glass attenuation; linear, nodular or reticulo-nodular; honeycombing, suggestive for end-stage fibrosis. Correlation of HRCT with histologic findings in 31 patients with idiopathic interstitial fibrosis (IIF) allowed assessment of disease activity, follow-up and therapeutic result. HRCT definitely better than conventional radiology detects the presence, type and extent of parenchymal alterations, differentiating potential reversible lesions (inflammatory) from potentially irreversible (fibrotic) lesions. In IIF, for diagnostic accuracy the specimen of open lung (the gold standard), transbronchial or video-thoracoscopic biopsy must be preoperative, HRCT-assisted and centered on ground glass opacties (or nodules in suspected histiocytosis X) since a diagnostically reliable biopsy correlates with HRCT morphology of histologic specimen. Interstitial lung disease includes benign as well as malignant forms, thus only a multidisciplinary approach can prevent long term hazardous effects as severe cor pulmonale or a fatal outcome. The histologic HRCT-assisted assessment of "active" lesions is crucial for correct careful treatment of these patients.
More Related Videos


Related Concept Videos
 01:29
Pneumonia II: Pathophysiology
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:23
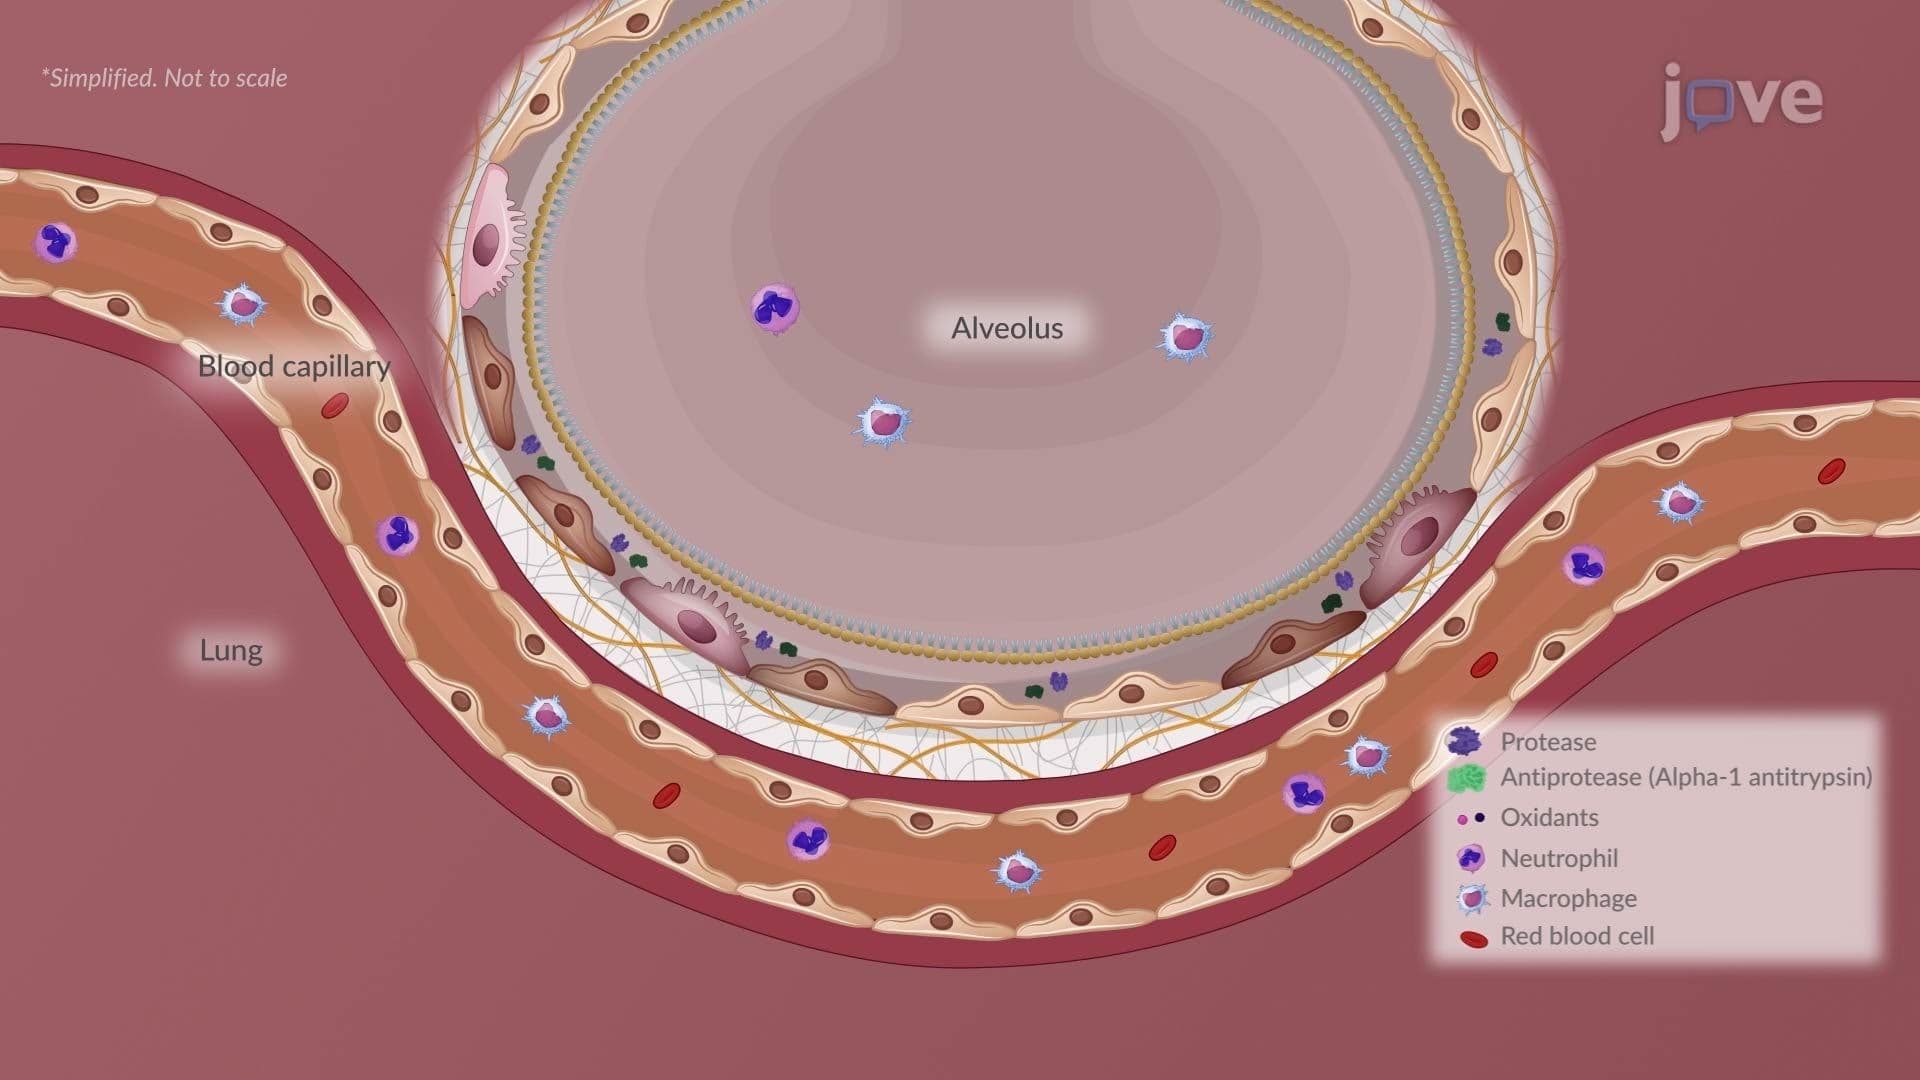
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:29
Pneumonia I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology