Related Experiment Video
Updated: Aug 3, 2026
Non-invasive Optical Measurement of Cerebral Metabolism and Hemodynamics in Infants
Published on: March 14, 2013
Cerebral metabolic rate for glucose after neonatal hypoglycaemia
A Kinnala1, P Nuutila, U Ruotsalainen
1Department of Pediatrics, University of Turku, Finland.

Insights
Neonatal hypoglycemia did not affect glucose metabolism in the brain or skeletal muscle. Further studies are needed to confirm these findings in larger patient groups with more severe hypoglycemia.
Area of Science:
- Neonatal Medicine
- Neuroscience
- Metabolic Research
Background:
- Neonatal hypoglycemia is a common condition in newborns.
- Understanding its long-term effects on brain metabolism is crucial.
Purpose of the Study:
- To investigate the impact of neonatal hypoglycemia on the local cerebral metabolic rate for glucose (LCMRglc).
- To compare glucose metabolism in the brain and skeletal muscles of hypoglycemic infants to controls.
Main Methods:
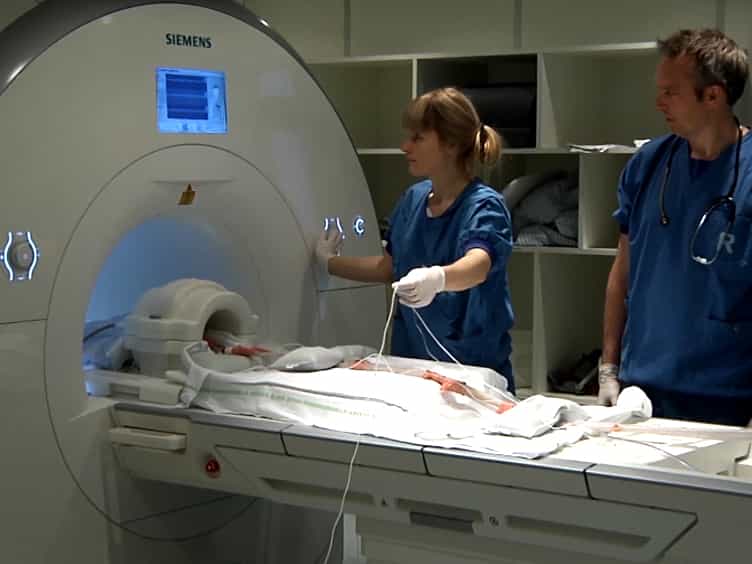
- Positron emission tomography (PET) with 2-[18F]Fluoro-2-deoxy-D-glucose (FDG) was used.
- LCMRglc was quantified in the whole brain, five cerebral regions, and skeletal muscles of eight hypoglycemic infants.
- PET studies were conducted during normoglycemia and compared to age-adjusted controls.
Main Results:
- Age-adjusted LCMRglc in the whole brain was comparable between hypoglycemic and control infants.
- Metabolic rate for glucose (MRglc) in skeletal muscles was also similar in both groups.
Conclusions:
- Neonatal hypoglycemia does not appear to alter glucose metabolism in the brain or skeletal muscle.
- Larger studies with more severe hypoglycemia cases are required for definitive conclusions.
Objective:
We studied the effect of neonatal hypoglycaemia on the local cerebral metabolic rate for glucose (LCMRglc).
Materials And Methods:
Eight newborn infants with neonatal hypoglycaemia were studied. The LCMRglc in the whole brain, in five cerebral regions and in skeletal muscles were quantitated using positron emission tomography (PET) and 2-[18F]Fluoro-2-deoxy-D-glucose (FDG). The PET studies were performed at the age of 5.3 +/- 6.2 days during normoglycaemia. The LCMRglc of these infants were compared to the age-adjusted LCMRglc of eight infants with suspected hypoxic-ischaemic brain injury but with normal neurological development.
Results:
After neonatal hypoglycaemia the age-adjusted LCMRglc in the whole brain was not lower than LCMRglc of the control infants (5.33 +/- 0.60 mumol/100 g/min vs. 6.71 +/- 0.60 mumol/100 g/min). Also the metabolic rate for glucose (MRglc) in the skeletal muscles was similar in hypoglycaemic and control infants (5.56 +/- 2.48 mumol/100 g/min vs. 6.99 +/- 2.41 mumol/100 g/min).
Conclusion:
MRglc in brain and in skeletal muscle seems to be normal after neonatal hypoglycaemia, although larger group of patients with more severe hypoglycaemia are needed to confirm this finding.