Related Experiment Video
Updated: Oct 22, 2026

Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
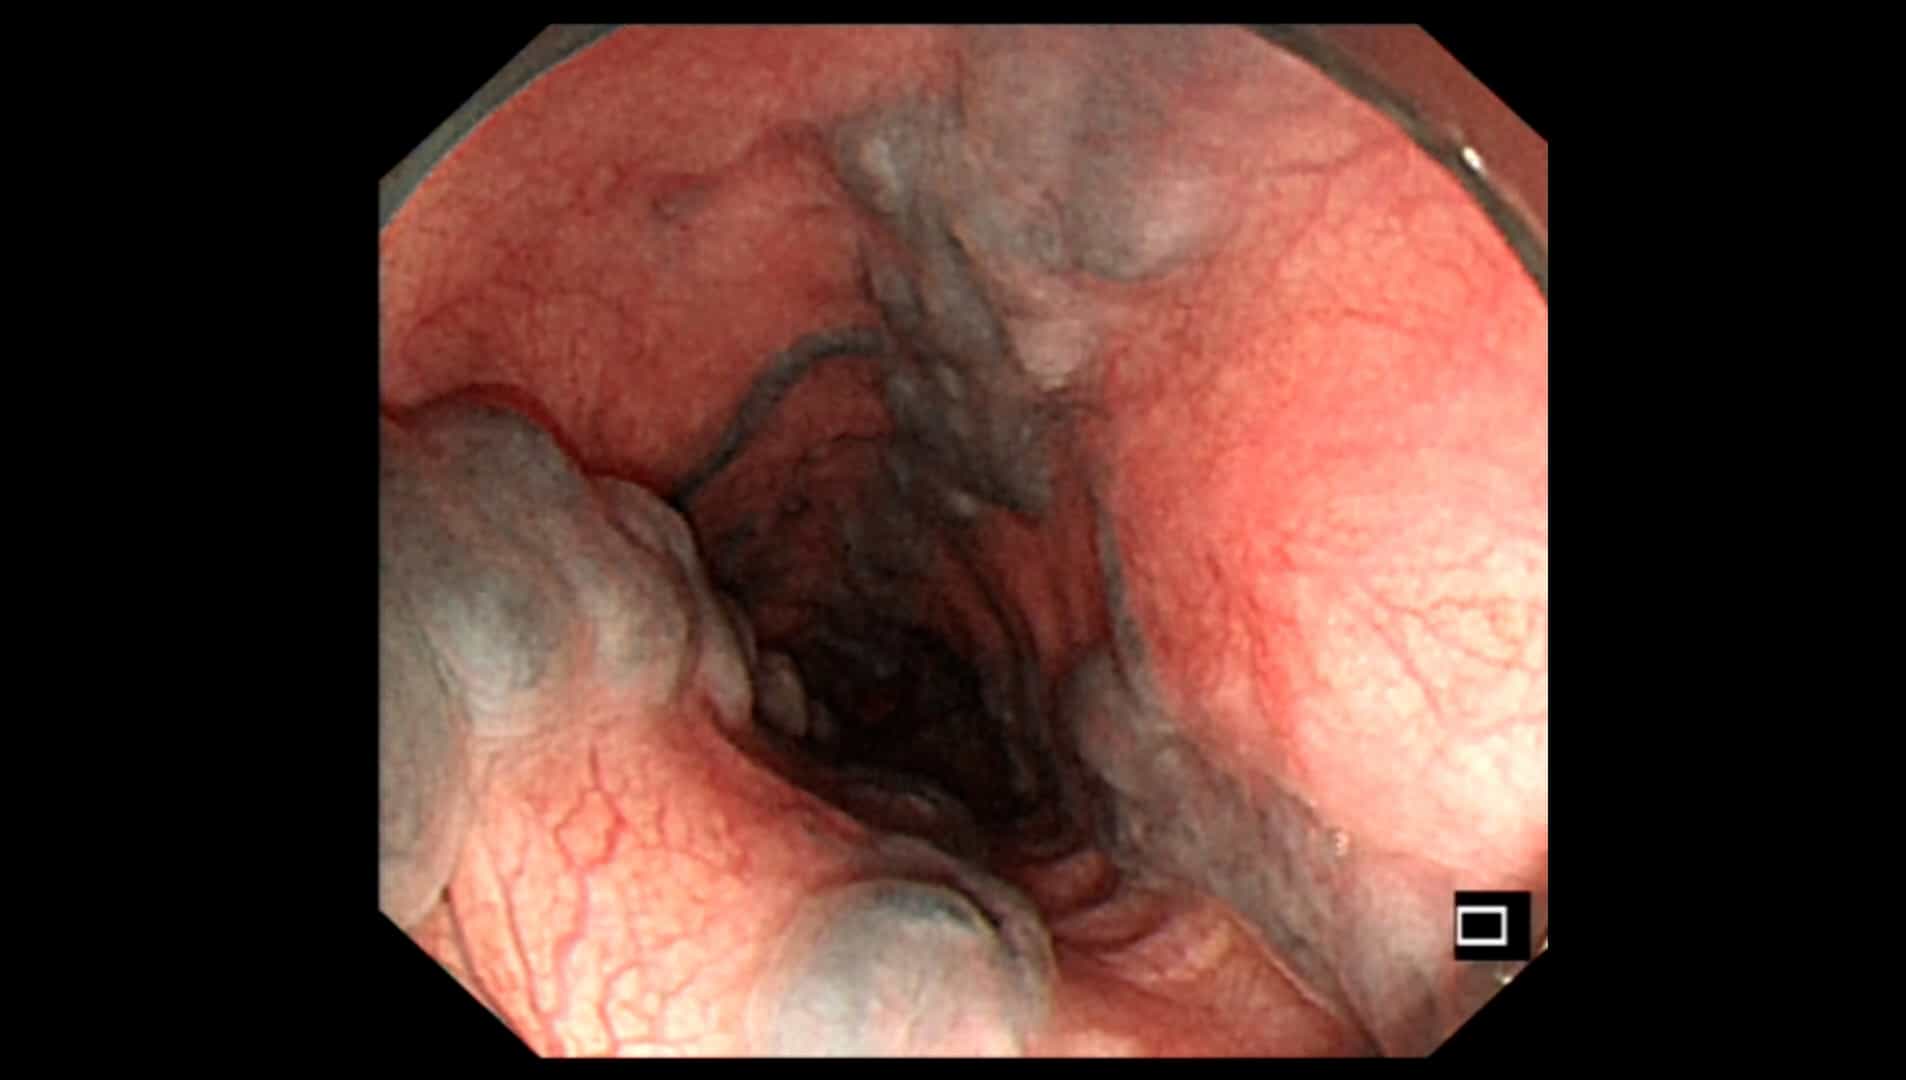
[Complete gastric wall necrosis after endoscopic sclerotherapy for a gastric ulcer with visible arterial stump]
W Scharnke1, M H Hust, B Braun
1Medizinische Klinik, Kreiskrankenhaus Reutlingen.

History And Clinical Findings:
A 43-year-old man with a gastric ulcer was admitted because of sudden onset of epigastric pain, cold sweats and dizziness. He had tachycardia (100/min); his blood pressure was 120/80 mm Hg: his epigastrium was tender to palpation. There were no tarry stools.
Investigations:
Haemoglobin concentration was 12.7 g/dl. WBC count 17,900/microliter. Gastroscopy revealed residual haematin and an ulcer with an arterial stump at the angular fold.
Treatment And Course:
3 ml epinephrine, diluted 1:20,000, and 13 ml of 1% polidocanol were injected around the arterial stump, most of the latter solution flowing back into the gastric lumen from the rather hard ulcer base. Haematemesis four days later necessitated laparotomy followed by gastrectomy with reconstruction and a Roux-Y anastomosis because of complete necrosis of the gastric wall. Histological examination of the surgical specimen showed chronic scarred gastric ulcer and ulcerating pangastritis with haemorrhagic necrosis of the wall and associated peritonitis, caused by accidental injection of polidocanol into the artery.
Conclusion:
Since the tissue-sparing injection of epinephrine, fibrin glue or salt solution is alone effective in the endoscopic treatment of bleeding gastroduodenal ulcers, polidocanol should not be injected as well.

Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications