Related Experiment Video
Updated: Jul 29, 2026


A Novel Approach for the Administration of Medications and Fluids in Emergency Scenarios and Settings
Published on: November 9, 2016
Efficacy and safety of intravenous phosphate replacement in critically ill patients
M M Perreault1, N J Ostrop, M G Tierney
1Department of Pharmacy, Ottawa General Hospital, Ontario, Canada.

Objective:
To evaluate the efficacy and safety of intravenous potassium phosphate administered in a fixed-dose regimen in critically ill patients.
Design:
Prospective, unblind study.
Setting:
Surgical-medical intensive care unit (ICU).
Participants:
Patients who developed hypophosphatemia during their ICU admission.
Interventions:
Patients with a serum phosphate concentration between 1.27 and 2.48 mg/dL (group 1) and those with a concentration of 1.24 mg/dL or less (group 2) received 15 and 30 mmol, respectively, of phosphate as a potassium salt via a central line over 3 hours.
Main Outcome Measures:
Normalization of serum phosphate within 6 hours of infusion, the development of arrhythmias during the infusion, and the development of hypocalcemia and hyperkalemia after the infusion were evaluated. Redevelopment of hypophosphatemia and the need for further therapy were also assessed.
Results:
Thirty-seven episodes of hypophosphatemia were entered in this study: 27 in group 1 (17 patients) and 10 in group 2 (10 patients). The mean serum phosphate concentration increased significantly from 2.02 to 2.82 mg/dL in group 1 and from 0.83 to 2.17 mg/dL in group 2, with no change in calcium or potassium. Normalization of serum phosphate with this initial dose occurred in 81.5% of the episodes in group 1 and 30% in group 2. However, over the following 2 days, 45% of the patients in group 1 and 60% in group 2 required further phosphate supplementation. No arrhythmias occurred during the 3-hour infusion that were related to the potassium phosphate. A significant drop in total serum calcium concentrations occurred in 2 patients who were slightly hypercalcemic prior to the infusion. Serum calcium concentrations remained above normal, but this was not associated with any adverse effects.
Conclusions:
The administration of potassium phosphate 15 mmol to critically ill patients with mild-to-moderate hypophosphatemia over 3 hours is both effective and safe. The administration of potassium phosphate 30 mmol to severely hypophosphatemic patients was safe but achieved normalization of serum phosphate in a minority of patients. Either a higher dose or the subsequent administration of more potassium phosphate may be required to normalize serum phosphate concentrations. Once normalization has occurred, there is a high likelihood of redevelopment of hypophosphatemia over the following 2 days and supplementation should be given accordingly.


Related Concept Videos
 01:33
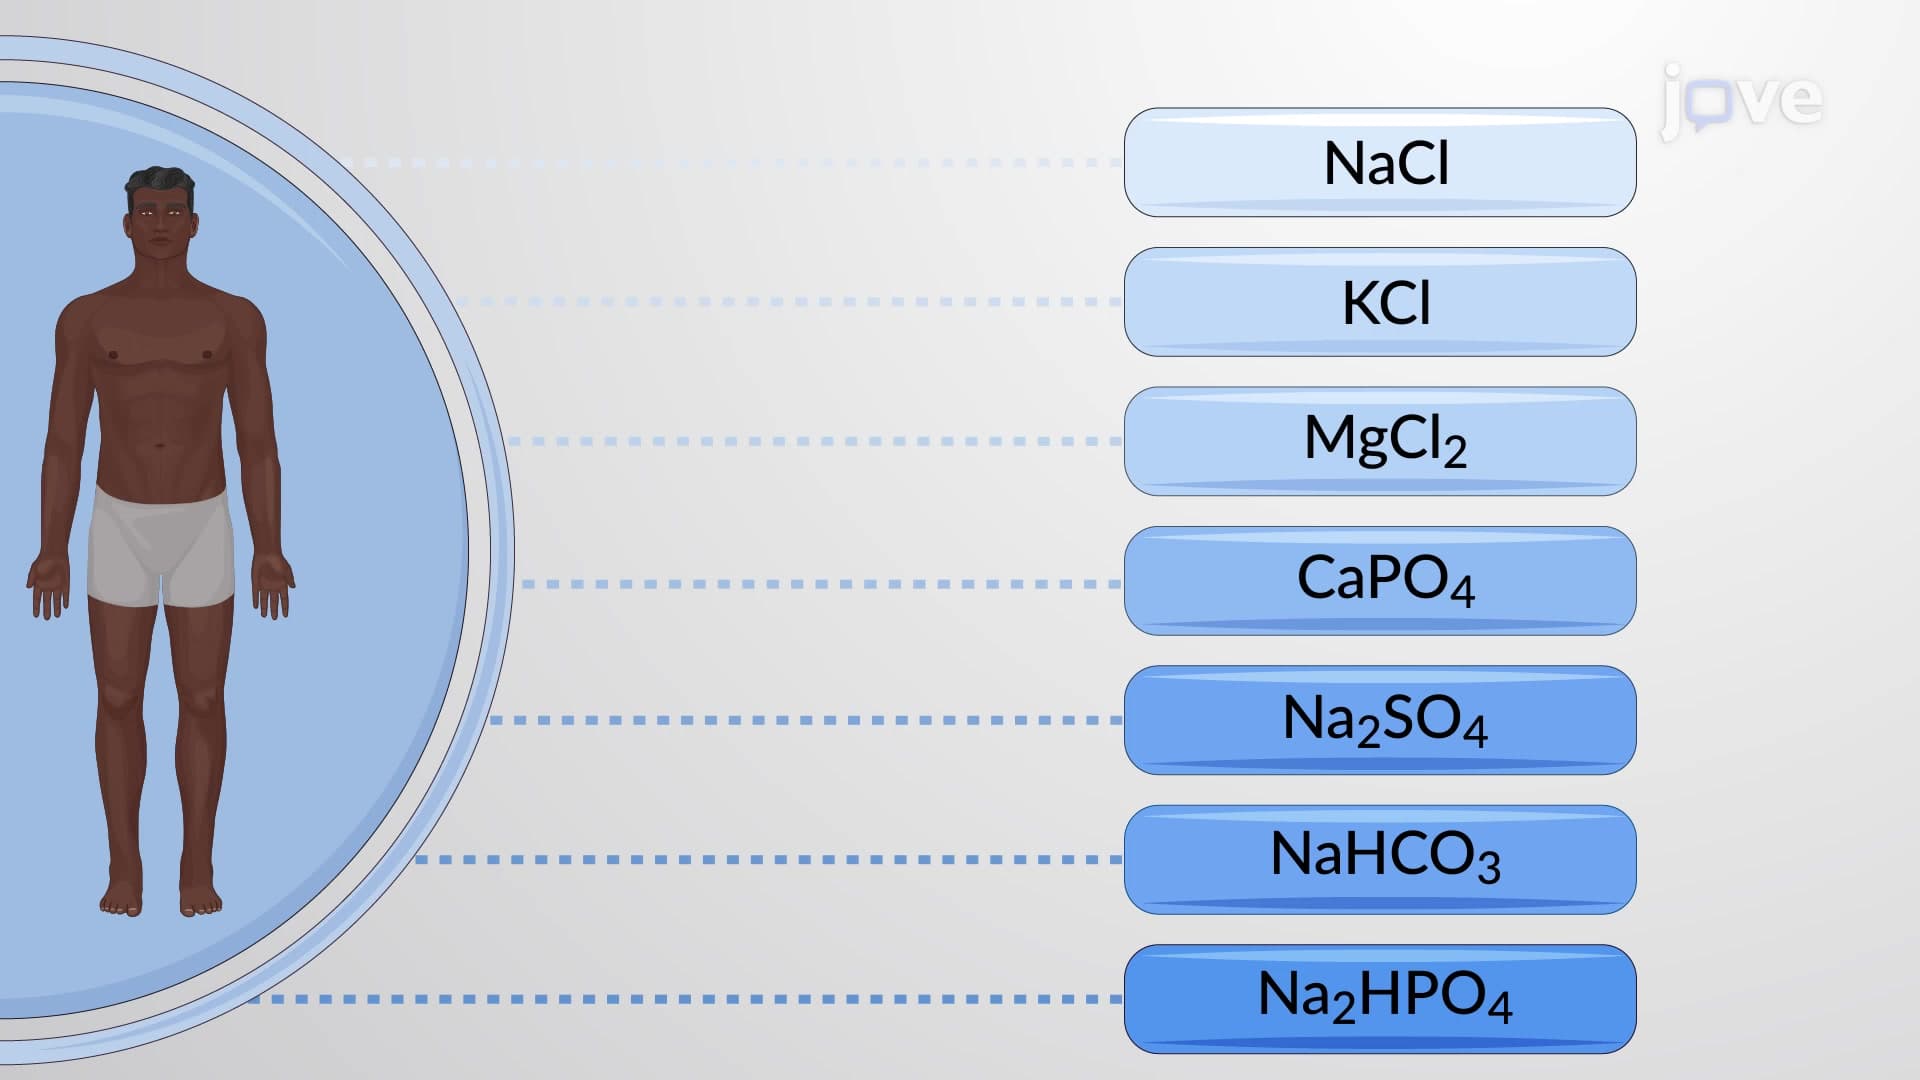
Introduction to Electrolytes
Role of Sodium
One...
 01:27
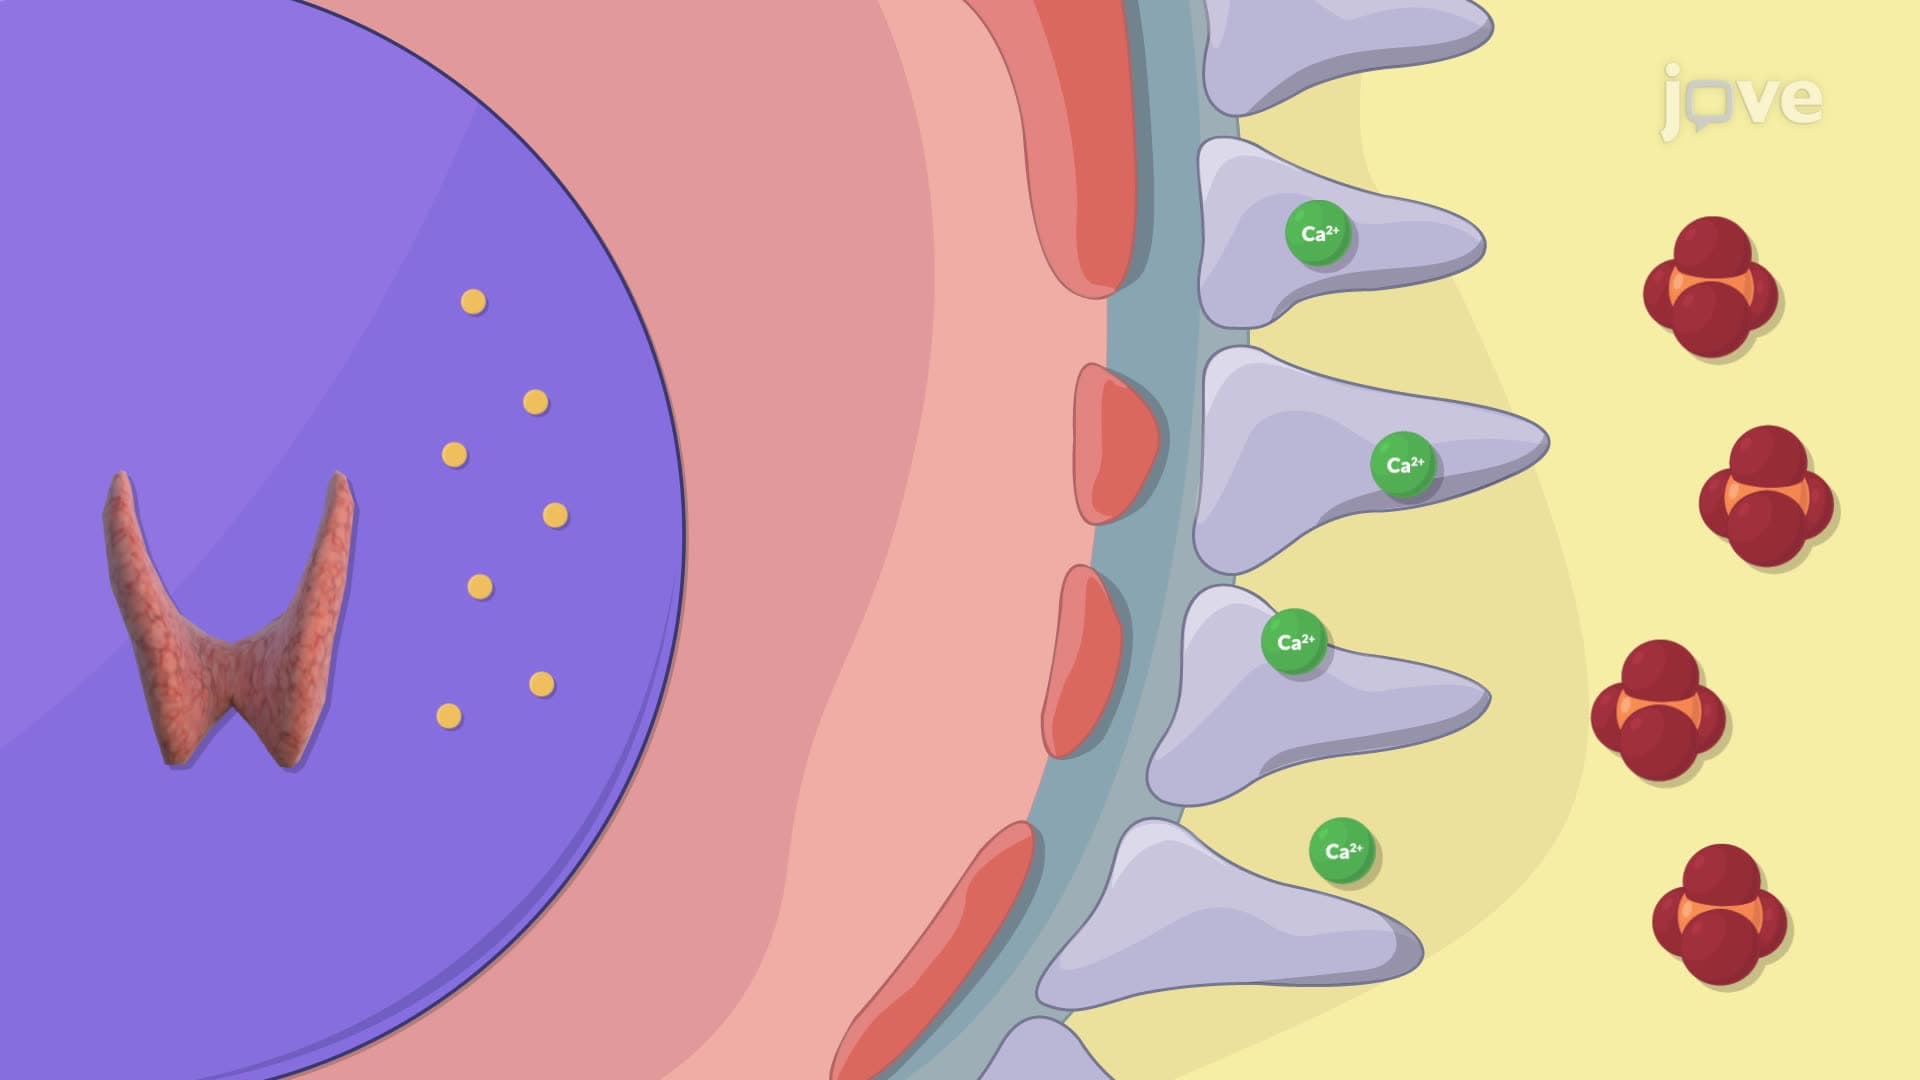
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily regulated...
 01:22
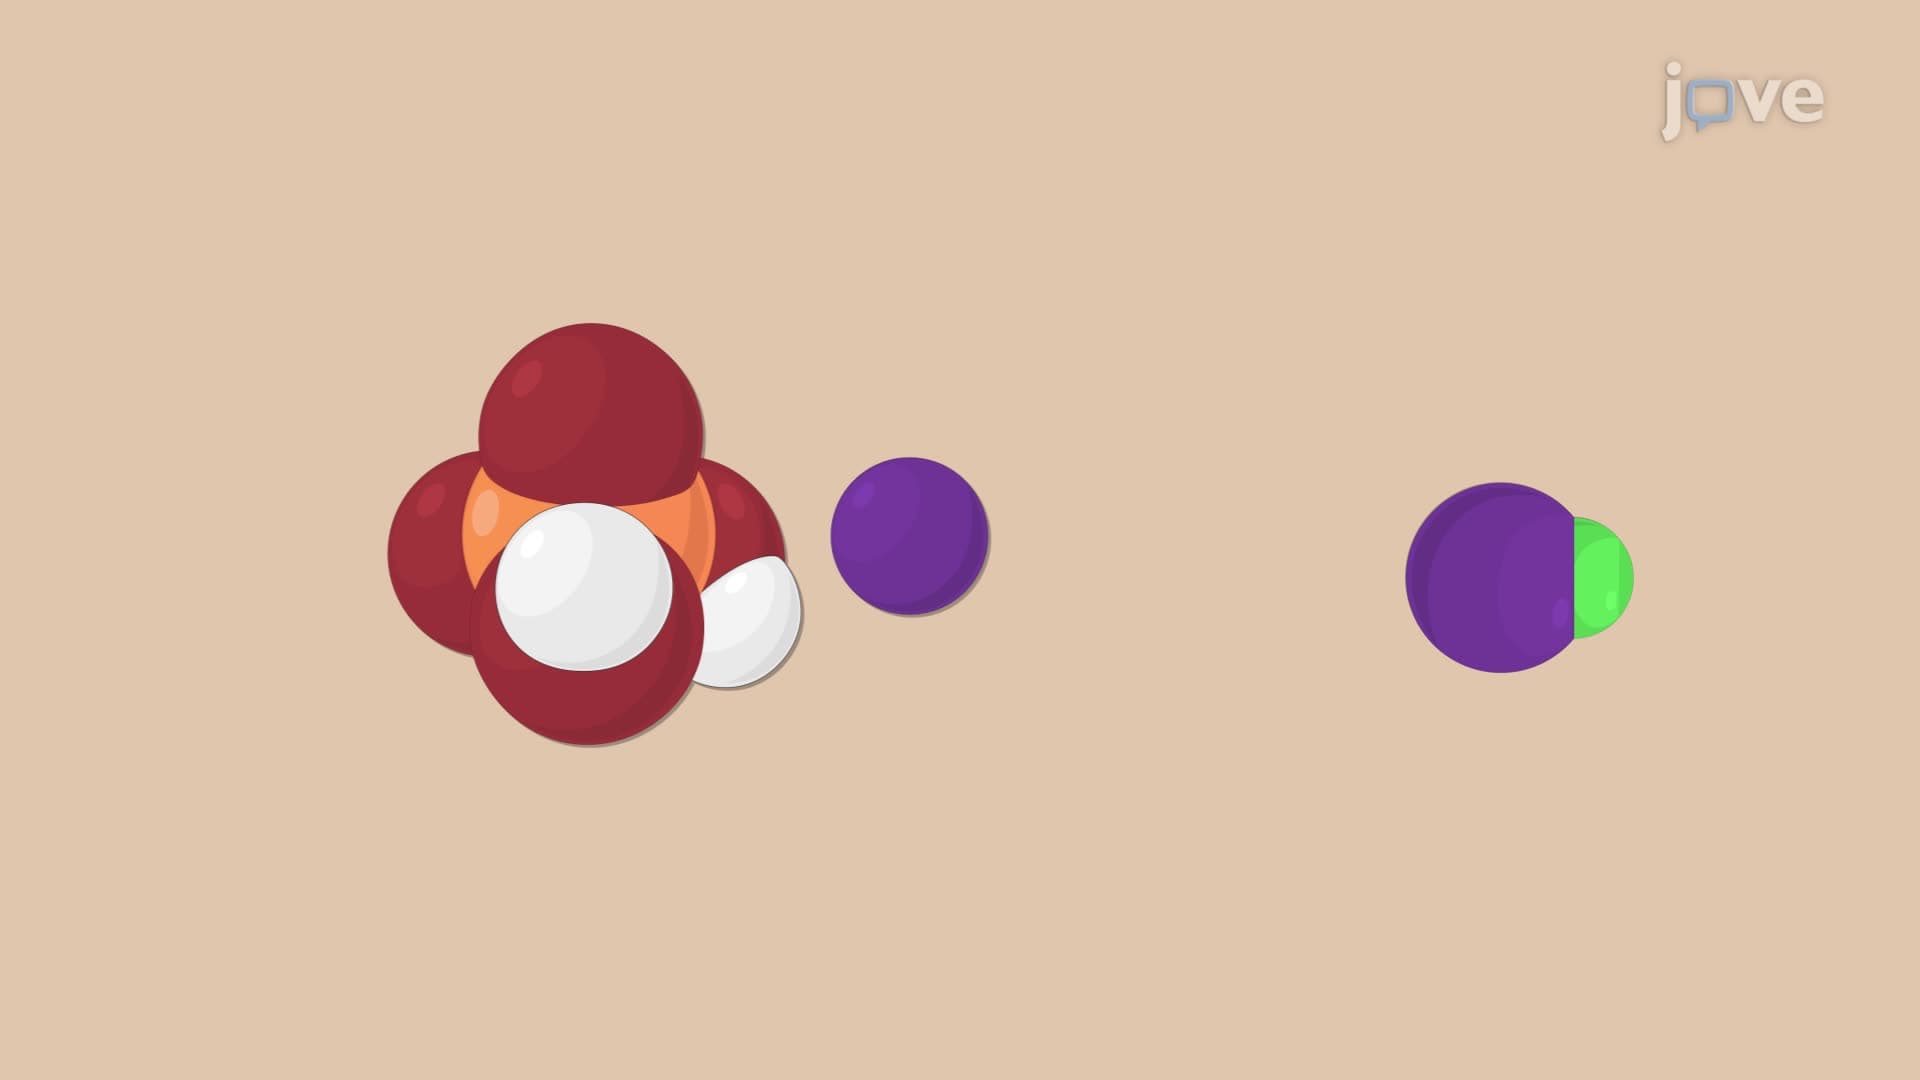
Phosphate Buffer
Sodium dihydrogen phosphate does not fully dissociate in neutral or acidic solutions. When a strong base, such as sodium hydroxide (NaOH), is introduced into the solution, sodium dihydrogen phosphate...
 01:28
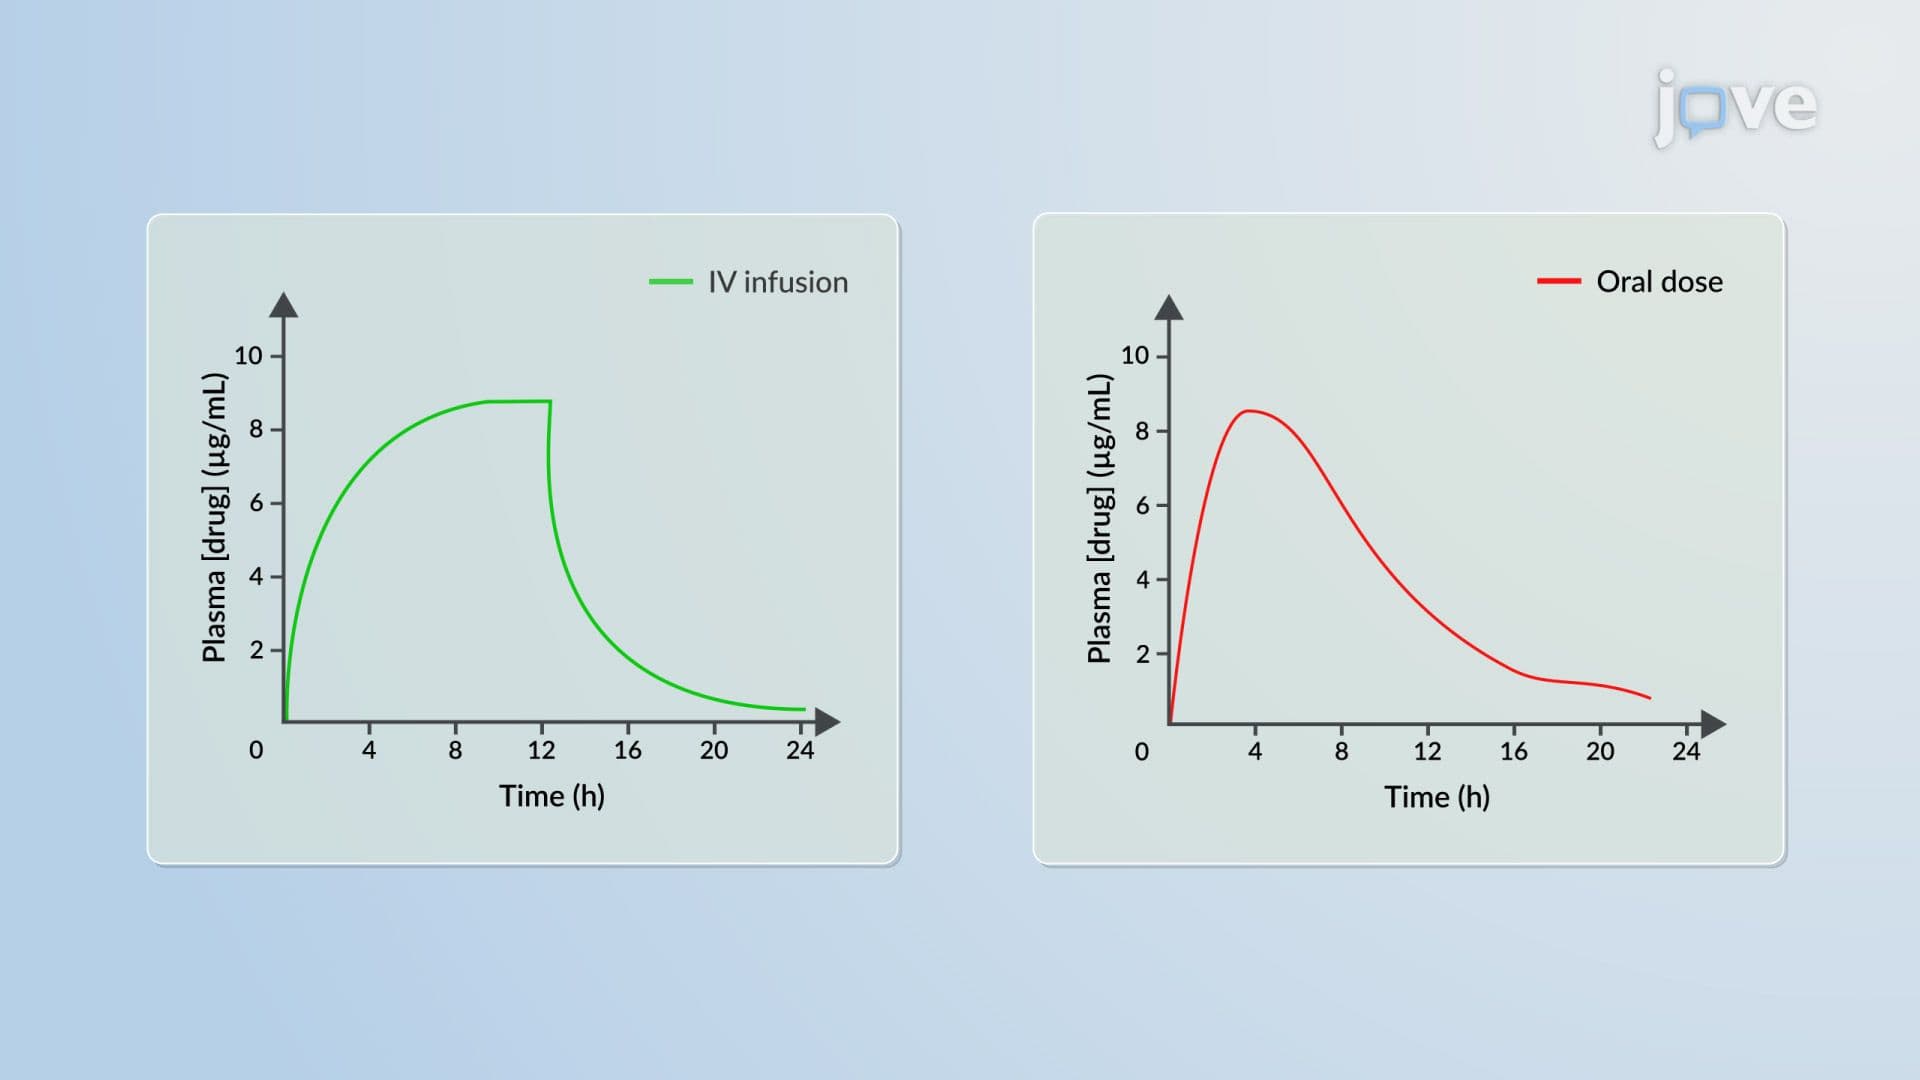
IV Infusion to Oral Dosing: Conversion Methods
 01:30
Continuous Renal Replacement Therapy
 01:20
Acute Kidney Injury V: Interprofessional Care