

The pharmacokinetics of teicoplanin in infants and children
M D Reed1, T S Yamashita, C M Myers
1Rainbow Babies and Children's Hospital, Department of Paediatrics, School of Medicine, Case Western Reserve University, Cleveland, OH 44106-5000, USA.

Insights
Teicoplanin pharmacokinetics in children showed variable drug disposition. A dose of 8 mg/kg every 12 hours is recommended for optimal therapeutic teicoplanin levels.
Area of Science:
- Pharmacology
- Clinical Pharmacy
- Pediatric Medicine
Background:
- Teicoplanin is an important antibiotic for treating Gram-positive bacterial infections.
- Understanding teicoplanin pharmacokinetics in pediatric populations is crucial for effective dosing.
- Limited data exists on teicoplanin pharmacokinetics in infants and children.
Purpose of the Study:
- To assess the pharmacokinetics of teicoplanin in pediatric patients.
- To determine optimal dosing regimens for teicoplanin in children.
- To evaluate the safety and tolerability of teicoplanin in this age group.
Main Methods:
- A single-dose and multidose pharmacokinetic study was conducted in 12 pediatric patients (2.4-11 years).
- Patients received teicoplanin 6 mg/kg intravenously daily for five days.
- Serum and urine samples were analyzed using microbiological assay and HPLC; data analyzed with three-compartment modeling.
Main Results:
- Teicoplanin disposition was variable, with wide ranges for V(d)ss, t(1/2)gamma, and CI.
- Peak and trough serum concentrations after the first dose were 39.3 and 1.8 mg/L, respectively, with minimal accumulation.
- The drug was primarily excreted unchanged in urine, with rapid distribution to a third compartment.
Conclusions:
- Teicoplanin pharmacokinetics in children are variable, necessitating careful dosing.
- A recommended dose of 8 mg/kg every 12 hours may achieve target trough concentrations of 11 mg/L.
- Higher doses might be required for severe infections like staphylococcal infections or endocarditis.
Abstract:
The pharmacokinetics of teicoplanin were assessed after a single dose and under multidose conditions in 12 infants and children. Study patients ranged in age from 2.4 to 11 years. Each patient received teicoplanin 6 mg/kg body weight given intravenously over 20-30 min, once daily for five consecutive days. Multiple timed blood and urine samples were obtained over the 6 day sampling period and were analysed for teicoplanin by both microbiological assay and HPLC. Three-compartment pharmacokinetic analysis was used to describe the drug's disposition characteristics. Peak and 24 h trough serum teicoplanin concentrations averaged 39.3 and 1.8 mg/L after the first dose with little accumulation observed after 5 days of therapy. Teicoplanin disposition was variable; V(d)ss ranged from 0.31 to 0.68 L/kg, t(1/2)gamma from 6.5 to 18.1 h and CI from 29 to 51 mL/h/kg. A substantial amount of the administered drug distributed rapidly to the largest, third compartment, with egress approximately four-fold slower than ingress. The majority of the drug was excreted unchanged in the urine. Teicoplanin administration was well tolerated by all study subjects. Using the teicoplanin pharmacokinetic data derived in our study, a dose of teicoplanin 8 mg/kg body weight administered every 12 h should achieve target serum trough concentrations averaging 11 mg/L in children. Higher doses, e.g. 15 mg teicoplanin/kg administered every 12 h, may be needed for the treatment of deep-seated staphylococcal infections and/or endocarditis.

Related Concept Videos
 01:15
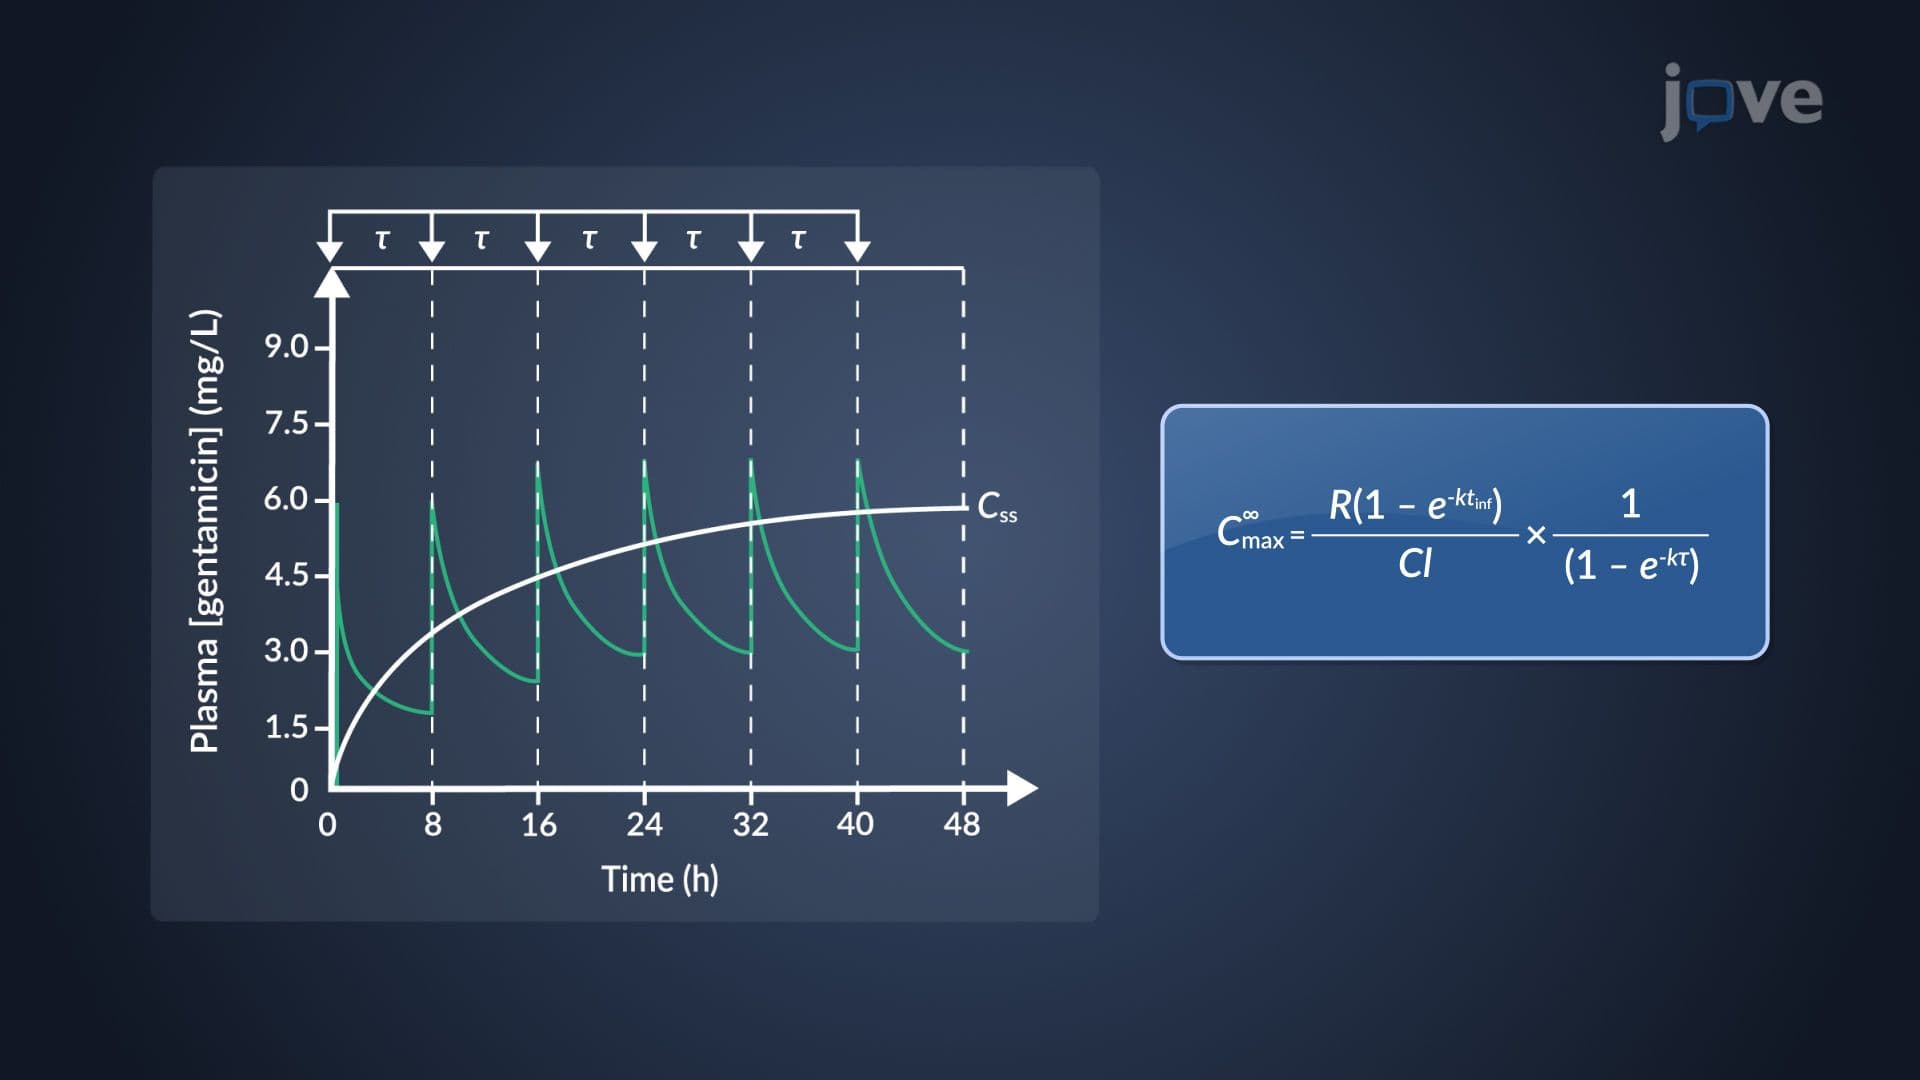
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:29
Drug Dosing: Infants and Children
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion