Related Experiment Video
Updated: Jul 30, 2026


The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
Gluteus maximus augmentation for the treatment of fecal incontinence
J J Meehan1, W D Hardin, K E Georgeson
1Department of Surgery, The Children's Hospital of Alabama and The University of Alabama at Birmingham, 35233, USA.

Abstract:
Fecal incontinence is a devastating problem for school-aged children and adults. Medical and biofeedback therapies are unsuccessful in most patients who have severely defective internal and external sphincters. Continued fecal incontinence frequently leads to social isolation and withdrawal. Gluteus maximus augmentation of the sphincter mechanism is one surgical method for treating fecal incontinence. The authors present their results with gluteus maximus augmentation of the anal sphincter and describe patient selection criteria. From 1992 through 1996, seven patients underwent gluteus maximus augmentation of the anal sphincter for fecal incontinence. Six of these patients were children 5 to 6 years of age who had major deficiencies of their anorectal sphincter demonstrated by manometry. One patient was a 56-year-old adult woman who had acquired idiopathic fecal incontinence. Four of the six children (67%) had imperforate anus and two had cloacal anomalies (33%). The augmentation was performed in three stages. A sigmoid-end colostomy with a Hartman's pouch was followed 1 month later by rotation of a portion of the gluteus maximus for anorectal sphincter augmentation. A colostomy take down was performed 2 to 4 months later. All patients underwent dilatation after sphincter augmentation and were taught muscle exercises for using their neosphincter during the period before colostomy take down. Four of six children and the adult are continent postoperatively (71%). Both patients who remain incontinent are unable to sense rectal distention clinically or on anal manometric analysis but have excellent voluntary sphincter tone. Fecal incontinence can be successfully treated with gluteus maximus augmentation in carefully selected patients. Patients unable to sense rectal distension are unlikely to benefit from this procedure. The presence of a rectal reservoir and a skin-lined anal canal also appear to be important in attaining fecal continence.

Related Concept Videos
 01:26
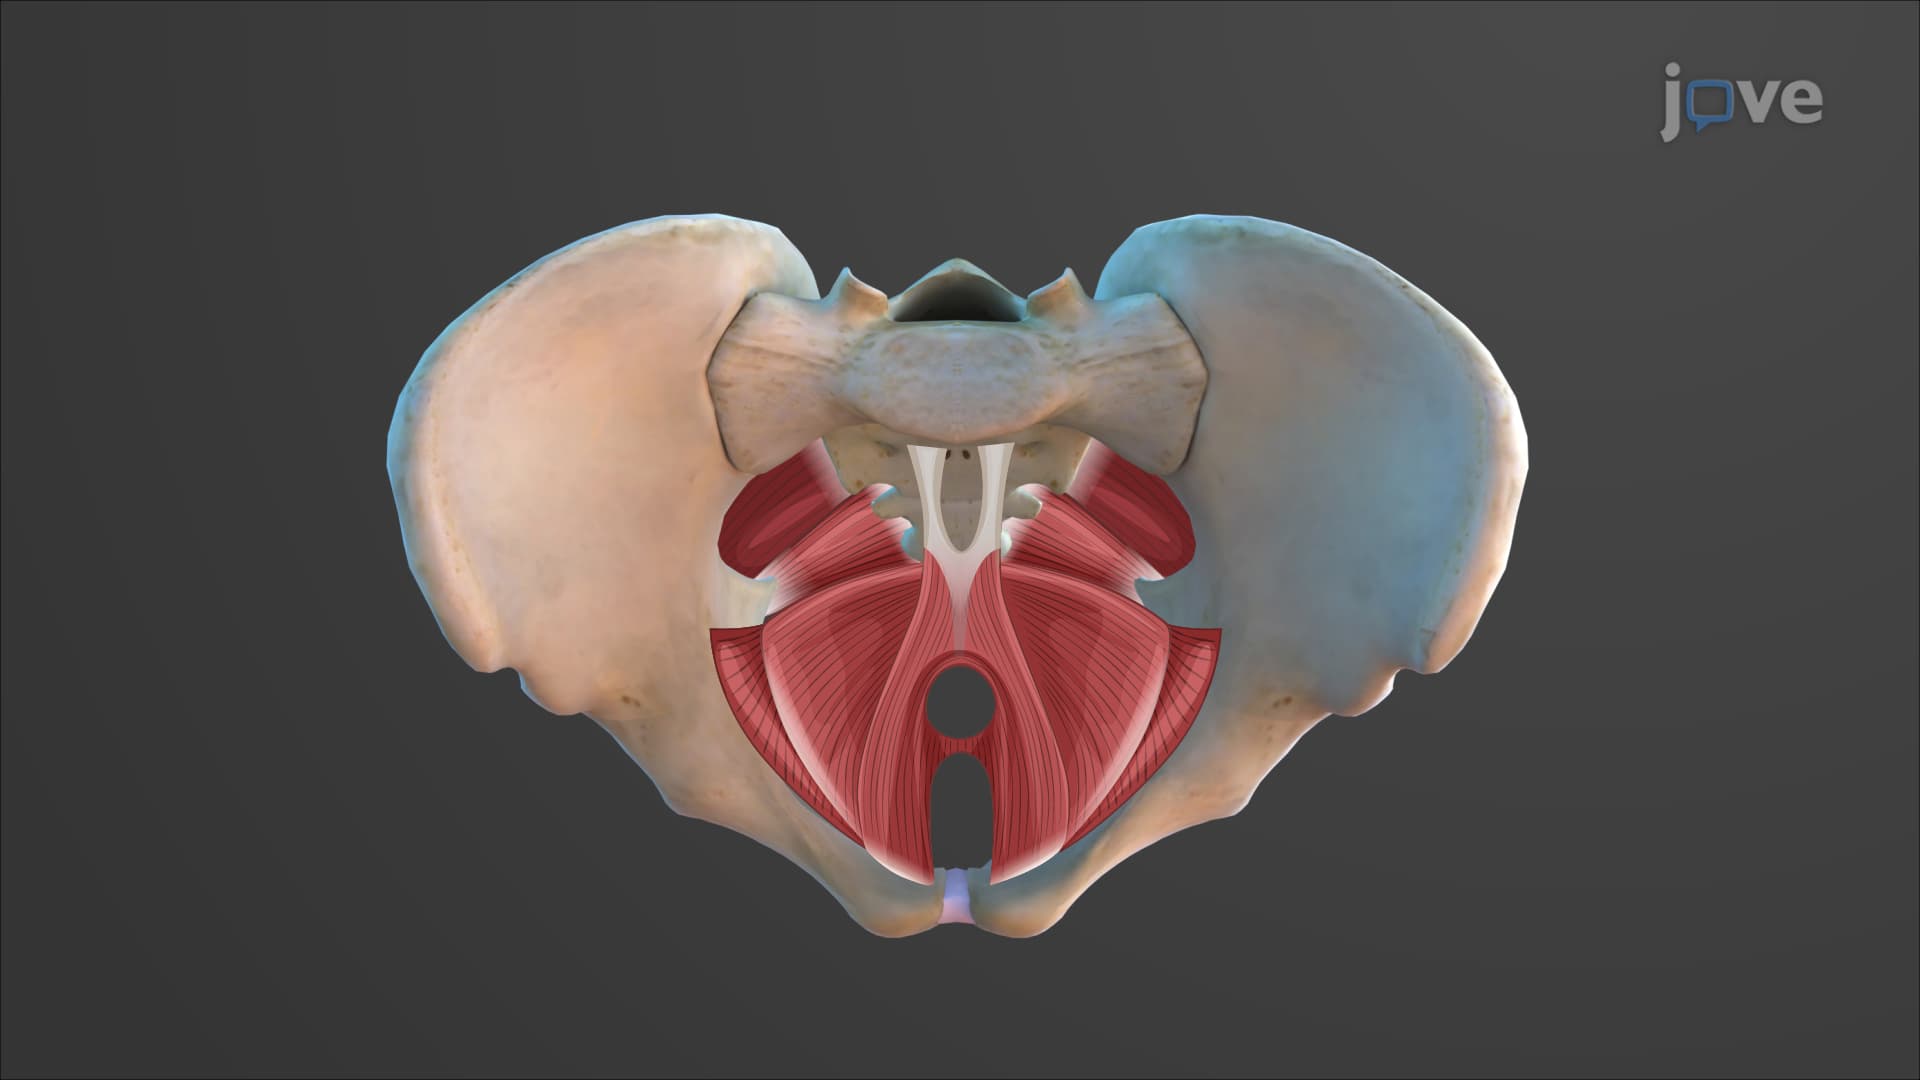
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:20
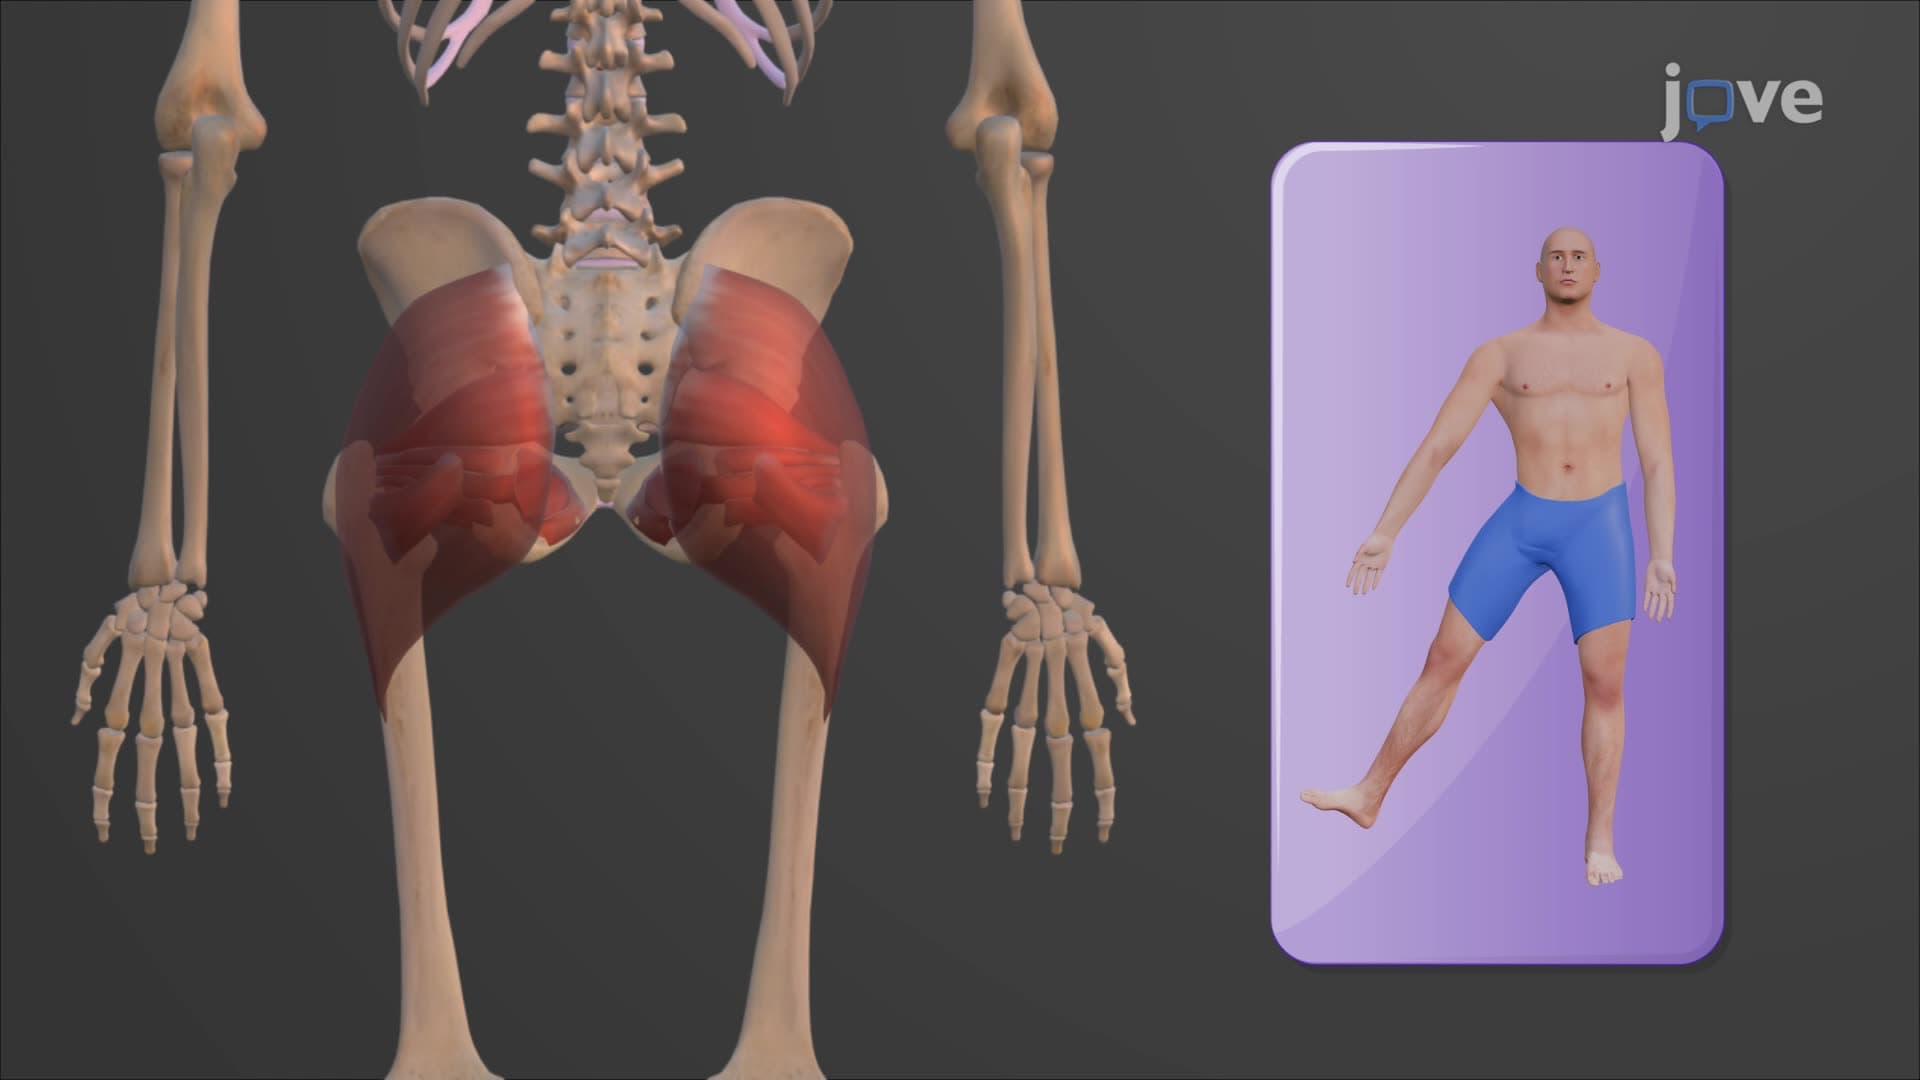
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar fascia...
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: