Related Experiment Video
Updated: Aug 13, 2026
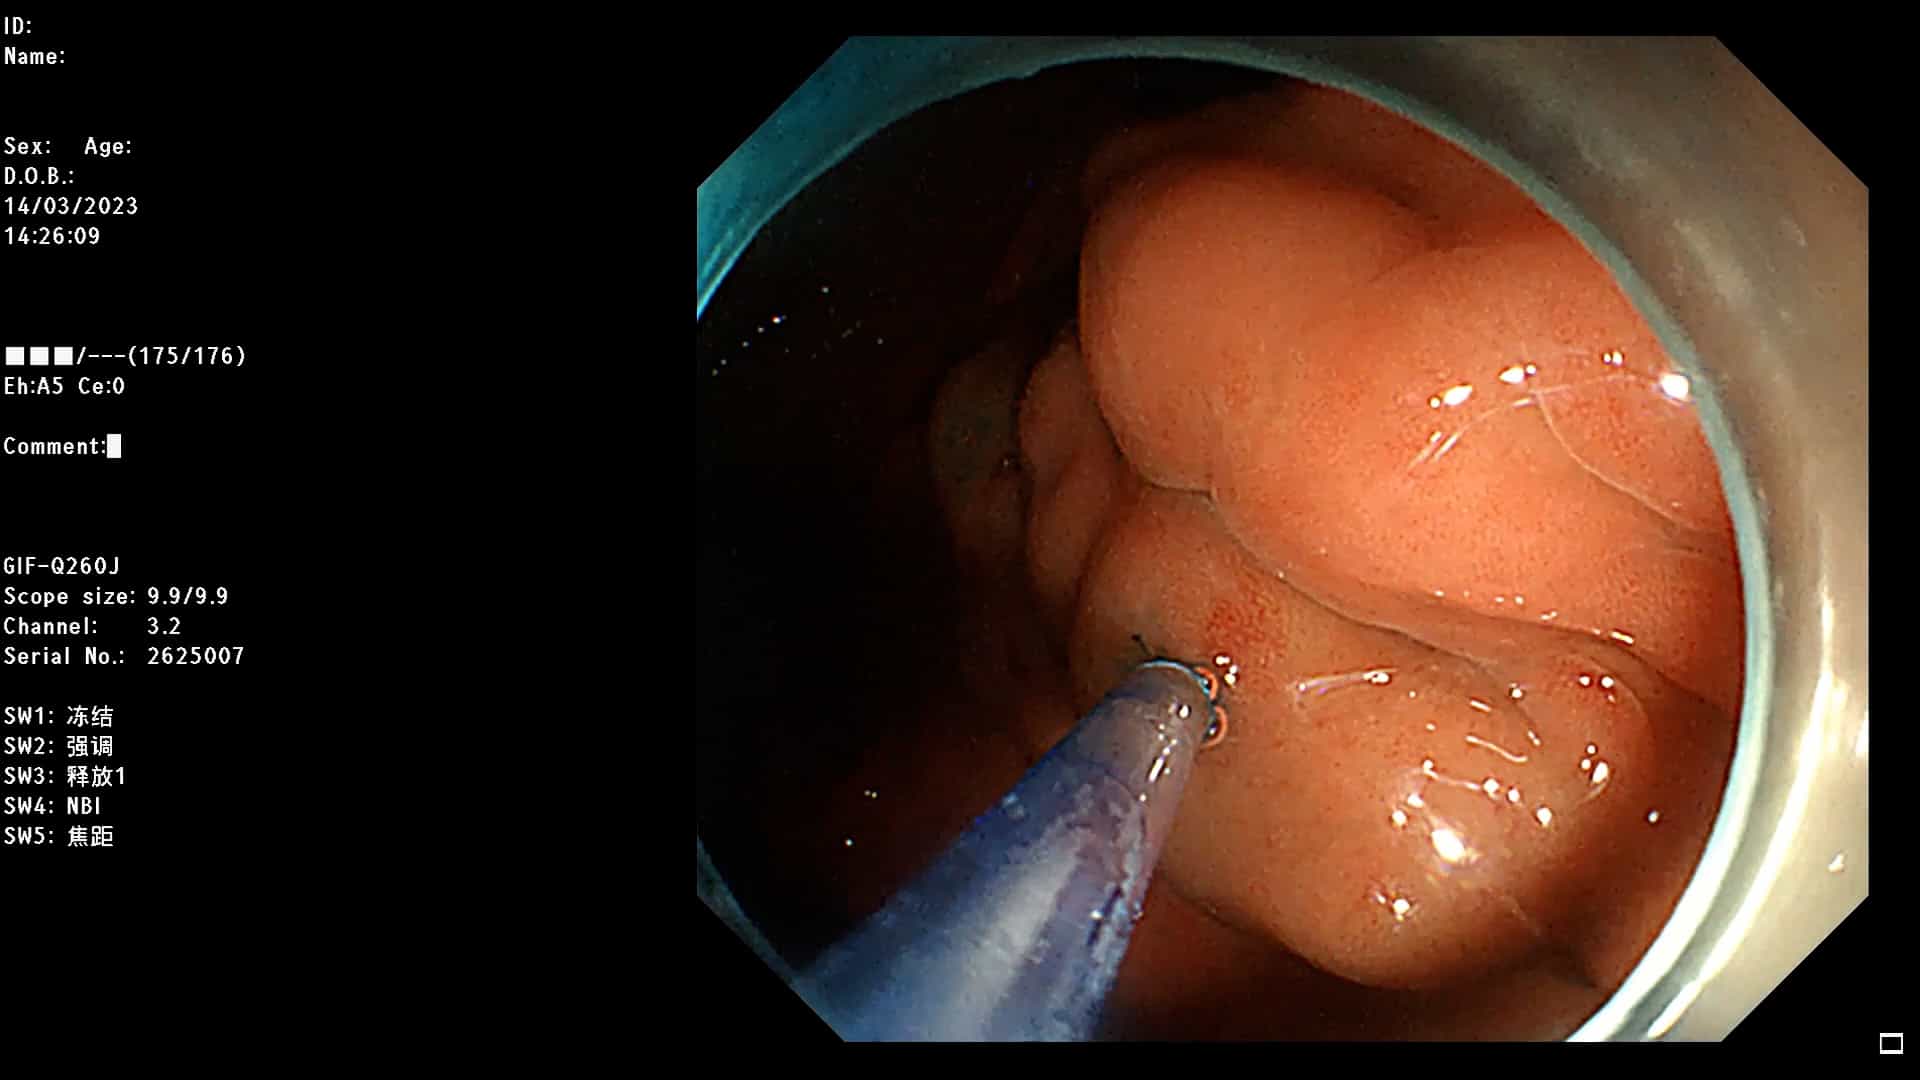
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Long-term follow-up of gastric variceal sclerotherapy: an eleven-year experience
1Department of Gastroenterology, G.B. Pant Hospital, New Delhi, India.

Insights
Gastric variceal sclerotherapy effectively stops bleeding and obliterates varices, especially gastroesophageal varices type 1. Alternative treatments are needed for isolated gastric varices type 1 due to higher rebleeding rates.
Area of Science:
- Gastroenterology
- Hepatology
- Endoscopic interventions
Background:
- Gastric variceal bleeding is a critical medical emergency.
- Endoscopic management strategies for gastric varices remain debated.
- Classification and targeted treatments for different gastric varice types are needed.
Purpose of the Study:
- To evaluate the efficacy of gastric variceal sclerotherapy in managing bleeding and achieving obliteration.
- To compare treatment outcomes across different classifications of gastric varices.
- To identify patient groups that may benefit from alternative therapeutic approaches.
Main Methods:
- Gastric varices were classified into gastroesophageal varices type 1 (GOV1), type 2 (GOV2), and isolated gastric varices type 1 (IGV1).
- Sclerotherapy involved weekly paravariceal and intravariceal injections of absolute alcohol.
- Outcomes assessed included acute bleeding control, variceal obliteration, rebleeding rates, and mortality.
Main Results:
- Sclerotherapy arrested acute bleeding in 66.7% of emergency cases.
- Overall variceal obliteration was achieved in 71.6% of patients undergoing elective sclerotherapy.
- Obliteration rates were highest for GOV1 (94.4%), followed by GOV2 (70.4%), and lowest for IGV1 (41%).
- Rebleeding rates were significantly higher for IGV1 (53%) compared to GOV1 (5.5%) and GOV2 (19%).
Conclusions:
- Gastric variceal sclerotherapy is effective for arresting acute bleeding and achieving obliteration.
- Treatment success is significantly higher for gastroesophageal varices (GOV1 and GOV2) than isolated gastric varices (IGV1).
- Alternative therapies should be explored for patients with IGV1 due to poor sclerotherapy outcomes and high rebleeding risk.
Background:
Bleeding from gastric varices is often a serious medical emergency. The role of endoscopy in the management of gastric variceal bleeding is still controversial. The types of gastric varices and their respective management strategies have not been identified.
Methods:
Gastric varices were observed in 209 patients with portal hypertension. Seventy-one patients (with cirrhosis 33, noncirrhotic 38) underwent gastric variceal sclerotherapy, 53 of these (75%) for gastric variceal bleeding. By use of a previously described classification, gastric varices were divided into gastroesophageal varices, type 1 (GOV1) and type 2 (GOV2), and isolated gastric varices, type 1 (IGV 1). Gastric variceal sclerotherapy was done every week using a combination technique of paravariceal and intravariceal injections with absolute alcohol.
Results:
Emergency gastric variceal sclerotherapy arrested acute bleeding in 12 (66.7%) of 18 patients. Variceal obliteration was achieved in 43 of the 60 (71.6%) patients who underwent repeated elective sclerotherapy. Variceal obliteration was higher in patients with GOV1 (94.4%) than in those with GOV2 (70.4%) and IGV1 (41%). Rebleeding after elective gastric variceal sclerotherapy was seen in 5.5%, 19%, and 53%, respectively, in the three types of gastric varices. Gastric variceal recurrence was not seen during a mean follow-up of 24.2 +/- 22.9 months. Seventeen (24%) patients died, nearly equally from rebleeding and liver failure.
Conclusions:
(1) Sclerotherapy can effectively arrest acute gastric variceal bleeding and achieve gastric variceal obliteration, (2) it is more effective in patients with gastroesophageal varices, and (3) alternative therapies need to be evaluated for patients with IGV1.
Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care