Related Experiment Video
Updated: Jul 27, 2026
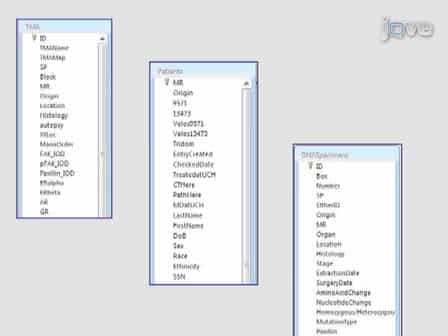

Generation of Comprehensive Thoracic Oncology Database - Tool for Translational Research
Published on: January 23, 2011
Data quality in population-based cancer registration: an assessment of the Merseyside and Cheshire Cancer Registry
1Public Health Medicine, North West Regional Health Authority, University of Liverpool, UK.

Abstract:
Merseyside and Cheshire Cancer Registry (MCCR) data quality was assessed by applying literature-based measures to 27,942 cases diagnosed in 1990 and 1991. Registrations after death (n = 8535) were also audited (n = 917) to estimate death certificate only (DCO) case accuracy and the proportion of registrations notified by death certificate (DC). Ascertainment appeared to be high from the registration/mortality ratio for lung [1.01:1] and to be low from capture-recapture estimates (59.4%), varying significantly with site from oesophagus [92.2% (95% CI 88.5-95.9)] to breast [47.5 (95% CI 41.8-53.2)]. The estimated DC-dependent proportion was 20% (5601 out of 27 942) with successful traceback in 3533 out of 5601 (63.1%) cases. DCO flagging (2497 out of 27,942, 8.9%) overestimated true DCO cases (2068 out of 27,942, 7.4%). The proportion of cases of unknown primary site was low (1.5%), varying significantly with age [0-4.2%, (95% CI 2.5-5.9)] and district [0.8% (95% CI 0.3-1.3) to 2.2% (95% CI 1.8-2.6)]. The median diagnosis to registration interval appeared to be good (10 weeks), varying significantly with site (P < 0.0001), age (P < 0.0001) and district (P < 0.0001). The proportion with a verified diagnosis was 77.3%, varying significantly with site [lung 55.2% (95% CI 53.7-56.7) to cervix 96.9% (95% CI 96.3-97.5)], age [45.2% (95% CI 40.9-49.5) to 97.5% (95% CI 96.4-98.6)] and district [71.8% (95% CI 69.9-73.8) to 82.5% (95% CI 80.7-84.3)]. The DCO percentages varied similarly by site [non-melanoma skin 0.4% (95% CI 0.2-0.6) to lung 22.6% CI (95% 19.9-25.3)], age [0.7(95% CI 0.1-1.4) to 23.0 (95% CI 19.4-26.6)] and district [6.9% (95% CI 5.7-8.1) to 13.9% (95% CI 12.9-15.0)]. MCCR data quality varied with age, site and district - inviting action - and apparently compares favourably with elsewhere, although deficiencies in published data hampered definitive assessment. Putting quality assurance into practice identified shortcomings in the scope, definition and application of existing measures, and absent standards impeded interpretation. Cancer registry quality assurance should henceforward be within an explicit framework of agreed and standardized measures.
More Related Videos
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
 07:13
Comparison of Predictive Performance of Three Lymph Node Staging Systems in Colorectal Signet Ring Cell Carcinoma Based on Machine Learning Model
Published on: April 18, 2025
Related Concept Videos
 01:25
Statistical Methods for Analyzing Epidemiological Data
 01:21
Cancer Survival Analysis