Related Experiment Video
Updated: Oct 24, 2026
Pseudofracture: An Acute Peripheral Tissue Trauma Model
Published on: April 18, 2011
Fractures of the fourth metacarpal
W A Eglseder1, P J Juliano, R Roure
1Section of Orthopaedics, R. Adams Cowley Shock Trauma Center/University of Maryland Medical System, Baltimore, MD 21201-1595, USA.

Objectives:
To determine (a) the degree of shortening associated with isolated fourth metacarpal fractures and the functional outcome after operative or nonoperative (protocol of casting and outrigger) treatment (clinical portion), and (b) the role of the deep metacarpal ligament in minimizing shortening after isolated fourth metacarpal osteotomies simulating clinical fracture (cadaveric portion).
Study Design:
This two-part study included a retrospective clinical portion and a cadaveric investigation.
Methods:
First, the records of twenty-four patients with isolated displaced oblique or spiral fourth metacarpal fractures without adjacent metacarpal fractures were retrospectively reviewed. The amounts of shortening after nonoperative (seventeen patients) and operative (seven patients) intervention were compared. Second, seven hands were studied to compare the length of intact fourth metacarpals to that after oblique osteotomies and after deep metacarpal ligament sectioning. The differences in shortening measurements were statistically analyzed using a paired t test.
Results:
There was no significant difference in mean initial shortening (+/-SD) between operative and nonoperative patients (2.65 +/- 1.85 mm vs. 4.19 +/- 1.83 mm, respectively; p < 0.09; overall average shortening, 3.1 mm) or functional outcome. The cadaveric study documented the important role of the deep metacarpal ligament in minimizing fourth metacarpal shortening. Fourth metacarpals osteotomized with an intact deep metatarsal ligament had significantly less mean shortening (+/-SD) than those with a sectioned deep metacarpal ligament: 2.1 versus 5.8 mm, respectively (p < 0.001).
Conclusions:
In the absence of unreducible rotational malalignment, fourth metacarpal fractures may be adequately treated nonoperatively with a protocol of casting and outrigger.
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:19
Bones of the Upper Limb: Humerus
 01:15
Bones of the Upper Limb: Ulna
 01:09
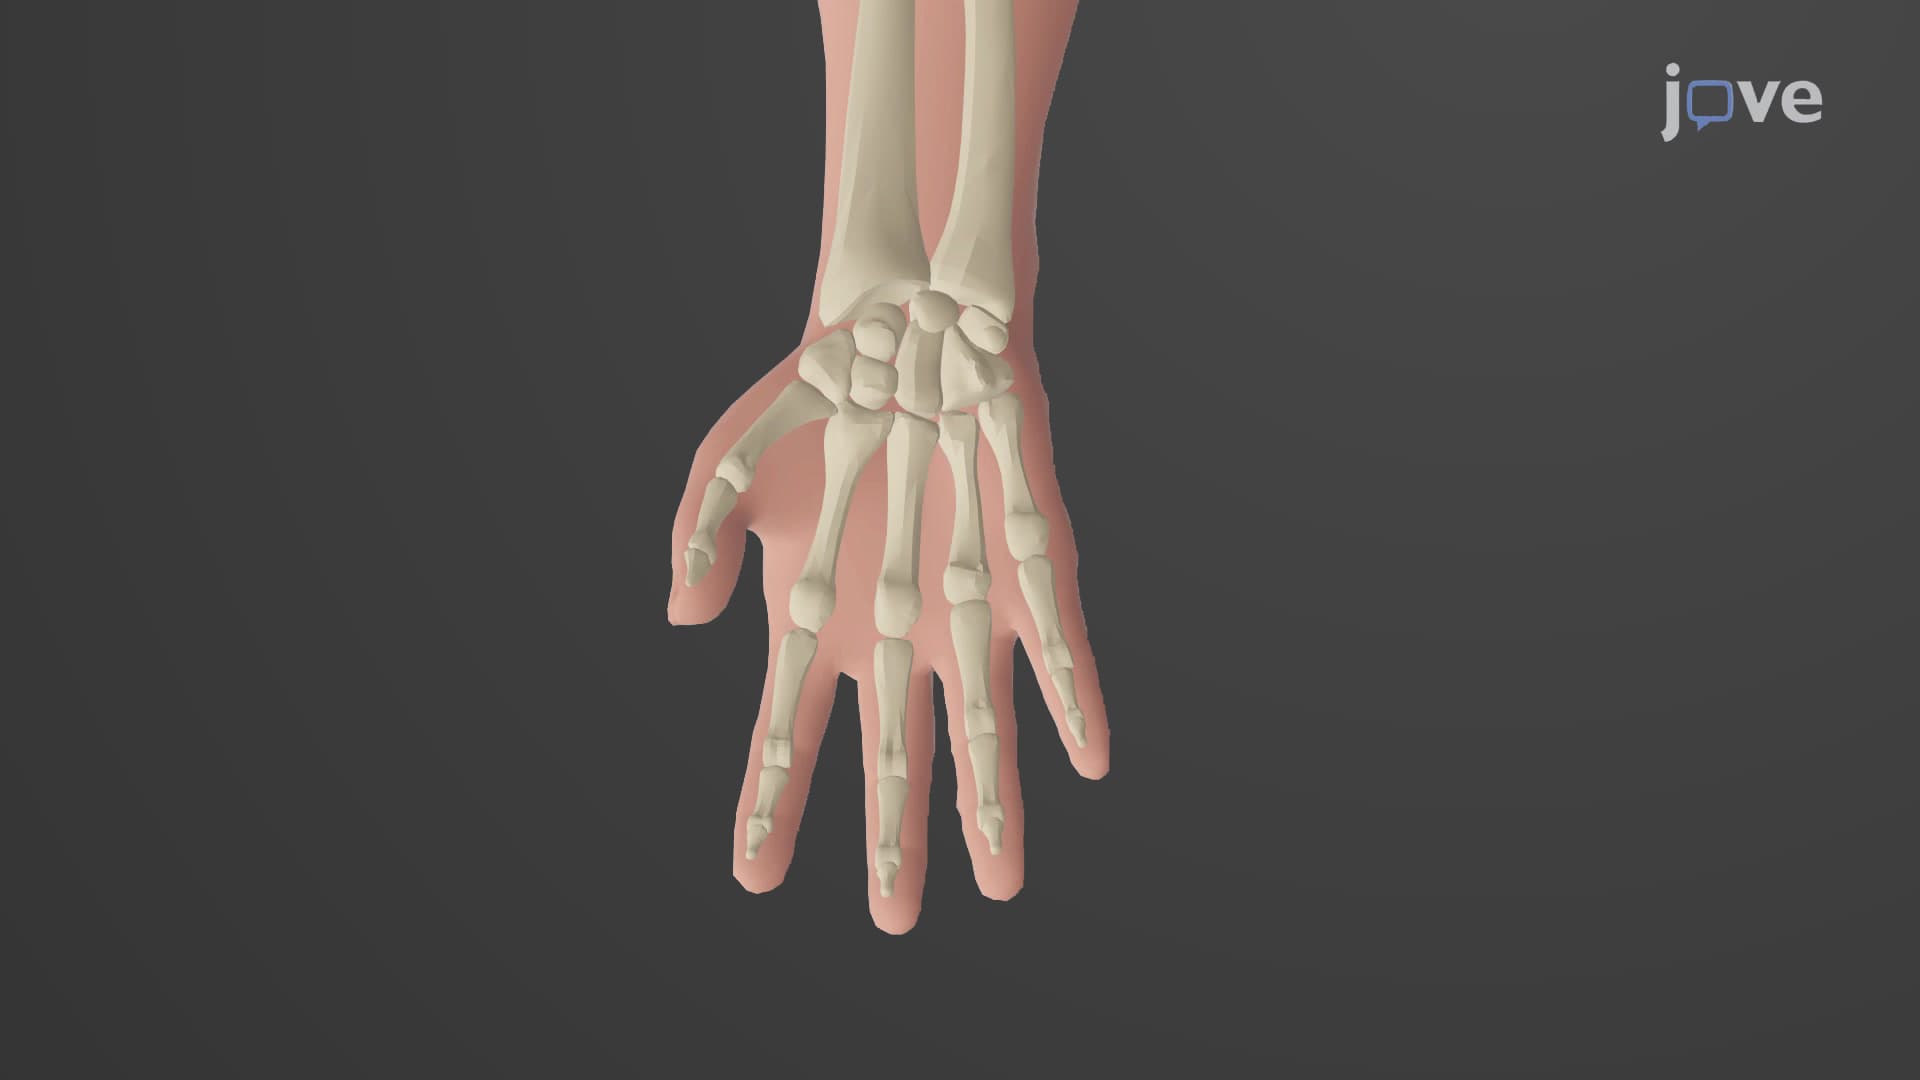
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a short...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:16
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi radialis,...