Related Experiment Video
Updated: Aug 8, 2026


Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Ophthalmological morbidity in very-low-birthweight infants with bronchopulmonary dysplasia
O A Ajayi1, D Raval, N Lucheese
1Division of Neonatology, Cook County Hospital, Chicago, Illinois, USA.

Insights
Infants born weighing less than 1250g with bronchopulmonary dysplasia face higher risks of retinopathy of prematurity and related ocular sequelae. Early intervention is crucial for these high-risk premature infants.
Area of Science:
- Neonatal ophthalmology
- Perinatal medicine
- Pediatric pulmonology
Background:
- Retinopathy of prematurity (ROP) and bronchopulmonary dysplasia (BPD) are significant morbidities in premature infants.
- Ocular sequelae can result from ROP, impacting long-term visual function.
- Understanding the interplay between ROP, ocular sequelae, and BPD is crucial for early intervention.
Purpose of the Study:
- To investigate the relationship between retinopathy of prematurity (ROP), its ocular sequelae, and bronchopulmonary dysplasia (BPD) in very low birth weight infants.
- To identify risk factors for ROP in this vulnerable population.
- To assess the impact of BPD on the development of ROP and subsequent ocular complications.
Main Methods:
- Prospective analysis of ophthalmological data from 67 infants weighing < 1250g at birth.
- Infants underwent at least two eye examinations before discharge and follow-up at 12-18 months postconceptual age.
- Comparison of outcomes between infants with severe BPD and controls, with adjustment for BPD in sequelae analysis.
Main Results:
- Incidence of any ROP was 33%, severe ROP was 25%.
- Infants with severe BPD had 1.7x higher odds of any ROP and 1.8x higher odds of severe ROP.
- Incidence of ocular sequelae was 45%; ROP increased odds of sequelae (OR 2.3-2.64), with adjusted ORs of 1.27-1.36 when accounting for BPD.
Conclusions:
- Bronchopulmonary dysplasia is an independent risk factor for ophthalmologic morbidity in premature infants.
- Lower birth weight, gestational age, acidosis, and hypoxemia are predictors of ROP.
- Future studies on therapies for chronic lung disease should adjust for the presence of underlying lung disease when evaluating effects on ROP.
Abstract:
This study was undertaken to determine the relationship between retinopathy of prematurity, ocular sequelae of retinopathy, and bronchopulmonary dysplasia in infants weighing < 1250 g at birth prior to the introduction of steroid therapy for chronic lung disease. Ophthalmological data from 67 infants (22 with severe bronchopulmonary dysplasia and 45 controls) who were enrolled prospectively in an early intervention program were analyzed. The infants had two or more eye examinations prior to discharge and a follow-up examination at 12 to 18 months postconceptual age. The incidence of any retinopathy of prematurity was 33%, and severe retinopathy was 25%. Infants with severe bronchopulmonary dysplasia were 1.7 times more likely to develop any retinopathy and 1.8 times more likely to develop severe retinopathy than controls. The incidence of ocular sequelae, was 45%. Infants with any retinopathy had a 2.3 odds of developing sequelae, and infants with severe retinopathy had a 2.64 odds ratio. When adjusted for bronchopulmonary dysplasia, the odds ratio for developing sequelae was 1.36 in infants with any retinopathy and 1.27 in those with severe retinopathy. The predictors of retinopathy were lower birthweight and gestational age, acidosis, and hypoxemia. Bronchopulmonary dysplasia per se has an adverse effect on ophthalmologic morbidity. Evaluation of the adverse effect of any therapy for chronic lung disease on retinopathy of prematurity should make adjustments for the underlying lung disease.


Related Concept Videos
 01:05
Breathing
 01:22
Photoreceptors and Visual Pathways
 01:17
Pulmonary Cycle: Exhalation
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
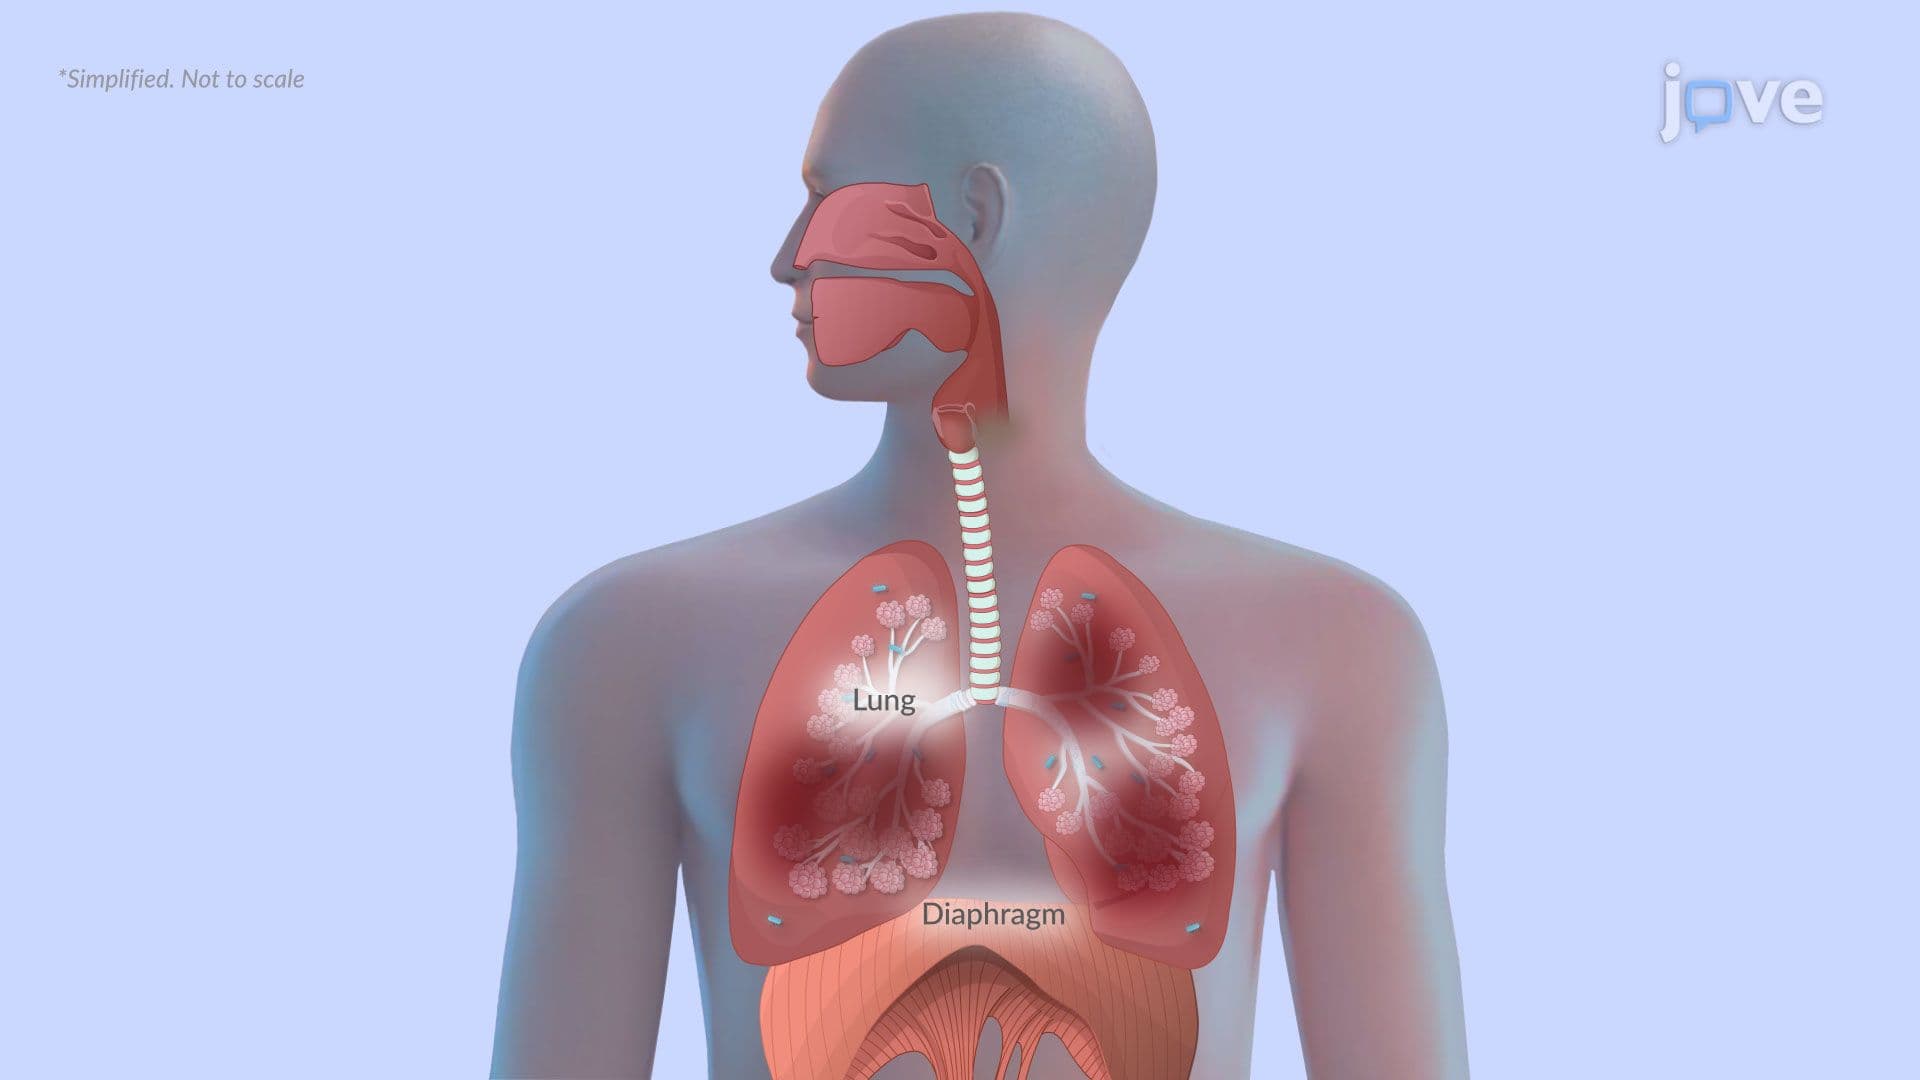
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features