Related Experiment Video
Updated: Sep 21, 2026

Removal of Arsenic Using a Cationic Polymer Gel Impregnated with Iron Hydroxide
Published on: June 28, 2019
Iron chelation therapy
1Department of Haematology, Royal Free Hospital and School of Medicine, London, UK.

Abstract:
Desferrioxamine (DFX) remains the most effective and safe iron chelator for treatment of patients with transfusional iron overload. It is usually given by intermittent subcutaneous infusions for 8-12 h on 4-6 days weekly using a battery-driven pump. Disposable balloon infusers provide a suitable method of giving continuous subcutaneous infusions with improved patient compliance. For patients with cardiac abnormalities due to iron overload, continuous intravenous desferrioxamine is essential to eliminate toxic plasma non-transferrin bound iron and to reduce body iron stores. Deferiprone (L1, l-2 dimethyl-3hydroxy-pyrid-4-one) is a less effective iron chelator but has the advantage of being orally active. Long-term trials in which patients have taken 75 mg/kg/day have shown that deferiprone is capable of maintaining body iron stores at safe levels in a proportion of thalassaemia major patients but body iron stores, assessed by liver biopsy remain at high levels (> 15.0 mg/g dry weight) in a substantial number of patients. These concentrations have been associated with tissue damage. Trials of increased doses of deferiprone (up to 100 mg/kg/day) or of combined therapy with daily deferiprone and DFX or 1 or 2 days each week are being carried out in an attempt to achieve lower body iron burden in these patients. Preliminary results show that the drugs can be given safely together and urine iron excretion produced is additive, implying that the drugs chelate different body iron pools. Patients previously well chelated with serum ferritin levels less than 2500 micrograms/L have the fewest side-effects from deferiprone and usually may be kept at the same level of body iron for periods of at least 4 years, assessed by serum ferritin and urine iron excretion. The side-effects of deferiprone result in some patients discontinuing therapy. These side-effects, especially arthropathy, mainly occur in previously poorly chelated and so the most heavily iron-loaded patients. Nausea and other gastrointestinal symptoms, agranulocytosis or milder degrees of neutropenia account with arthropathy for nearly all the withdrawals from deferiprone therapy. Patients with cardiomyopathy due to iron overload should be given intravenous DFX rather than deferiprone. Deferiprone, licensed for pharmaceutical use in India, awaits official approval for widespread clinical use in Western Europe and North America. Meanwhile, attempts to find new orally active iron chelators and improved methods of administration of desferrioxamine are in progress.
More Related Videos
 11:04
Ion Mobility-Mass Spectrometry Techniques for Determining the Structure and Mechanisms of Metal Ion Recognition and Redox Activity of Metal Binding Oligopeptides
Published on: September 7, 2019
 05:36
Quantifiable and Inexpensive Cell-Free Fluorescent Method to Confirm the Ability of Novel Compounds to Chelate Iron
Published on: February 23, 2024
Related Concept Videos
 01:22
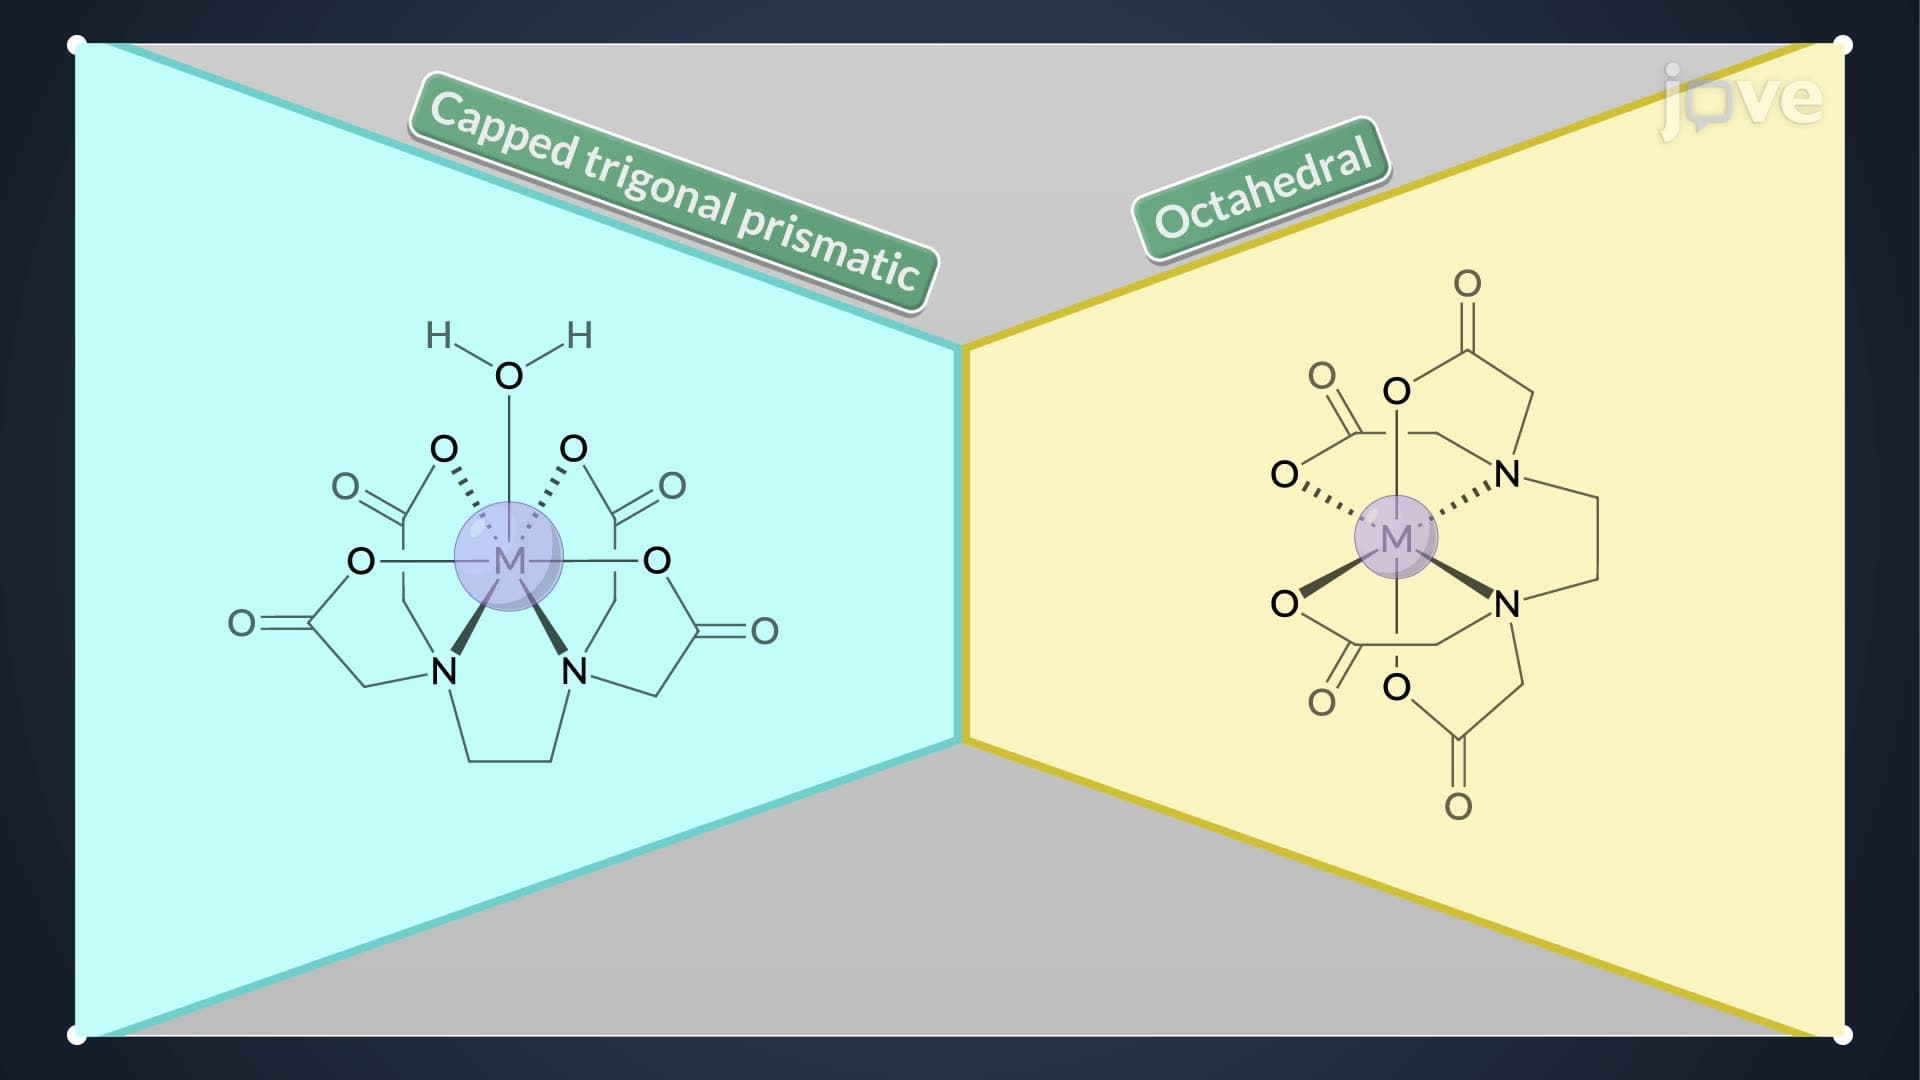
EDTA: Chemistry and Properties
 01:19
Masking and Demasking Agents
There are many masking agents, such as cyanide, fluoride, triethanolamine, thiourea, and 2,3-bis(sulfanyl)propan-1-ol (formerly 2,3-dimercapto-1-propanol), with the masking agent chosen based on the metal...
 00:56
Extraction: Advanced Methods
 01:09
Ion-Exchange Chromatography
 01:24
Microbes and Other Elemental Cycles
 01:21
Antiprotozoal Agents