Related Experiment Video
Updated: Aug 16, 2026
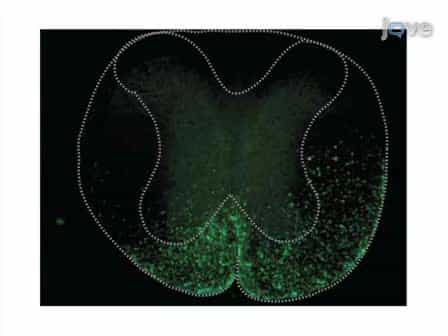
Surgical Transplantation of Mouse Neural Stem Cells into the Spinal Cords of Mice Infected with Neurotropic Mouse Hepatitis Virus
Published on: July 10, 2011
Peripheral blood stem cell transplantation in the treatment of progressive multiple sclerosis: first results of a
A Fassas1, A Anagnostopoulos, A Kazis
1Department of Haematology, The George Papanicolaou Hospital, Exokhi/Thessaloniki, Greece.

Several experimental autoimmune diseases (AID), including allergic encephalomyelitis, ie the multiple sclerosis (MS) model, respond to TBI and chemotherapy followed by BMT. Remissions of AID may also occur in patients with concomitant malignancies treated with allogeneic or autologous BMT. These observations have emphasized the possibility of treating AID with high-dose therapy and haematopoietic stem cell transplantation (HSCT). In a phase I/II pilot study, 15 patients with progressive MS were treated with BEAM followed by autologous blood SCT and antithymocyte globulin (ATG). Patients were severely disabled, with median EDSS and SNRS scores of 6 (5-7.5) and 42 (33-62), respectively. Cyclophosphamide (4 g/m2) and G/GM-CSF (5 microg/kg/day) were used for stem cell mobilization, which caused no neurotoxicity. On days +1 and +2, ATG (2.5-5 mg/kg) was given for in vivo T cell-depletion. Allergy (93%) and infections (87%) were the principal toxic complications. Mild, transient, neurotoxicity was observed in six patients in the immediate post-transplant period. The median follow-up time is 6 months (6-18). Durable neurologic improvements have been detected on both the EDSS (7/15) and SNRS (15/15) systems. One patient worsened at 3 months and two have relapsed. Autologous HSCT appears feasible in MS; it does not aggravate disability and seems to offer a clinical benefit. However, these observations need confirmation and long-term outcomes will show if benefits counterbalance toxicity and cost.
Several experimental autoimmune diseases (AID), including allergic encephalomyelitis, ie the multiple sclerosis (MS) model, respond to TBI and chemotherapy followed by BMT. Remissions of AID may also occur in patients with concomitant malignancies treated with allogeneic or autologous BMT. These observations have emphasized the possibility of treating AID with high-dose therapy and haematopoietic stem cell transplantation (HSCT). In a phase I/II pilot study, 15 patients with progressive MS were treated with BEAM followed by autologous blood SCT and antithymocyte globulin (ATG). Patients were severely disabled, with median EDSS and SNRS scores of 6 (5-7.5) and 42 (33-62), respectively. Cyclophosphamide (4 g/m2) and G/GM-CSF (5 microg/kg/day) were used for stem cell mobilization, which caused no neurotoxicity. On days +1 and +2, ATG (2.5-5 mg/kg) was given for in vivo T cell-depletion. Allergy (93%) and infections (87%) were the principal toxic complications. Mild, transient, neurotoxicity was observed in six patients in the immediate post-transplant period. The median follow-up time is 6 months (6-18). Durable neurologic improvements have been detected on both the EDSS (7/15) and SNRS (15/15) systems. One patient worsened at 3 months and two have relapsed. Autologous HSCT appears feasible in MS; it does not aggravate disability and seems to offer a clinical benefit. However, these observations need confirmation and long-term outcomes will show if benefits counterbalance toxicity and cost.
Related Concept Videos
 01:13
Induced Pluripotent Stem Cells
 01:22
iPS Cell Differentiation
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...