Related Experiment Video
Updated: Aug 30, 2026
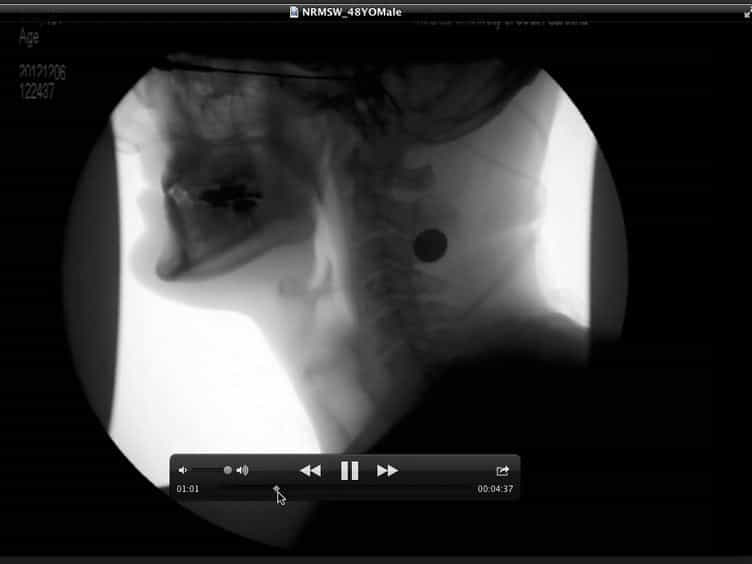

Coordinate Mapping of Hyolaryngeal Mechanics in Swallowing
Published on: May 6, 2014
Dysphagia in stroke: a prospective study of quantitative aspects of swallowing in dysphagic patients
H Nilsson1, O Ekberg, R Olsson
1Department of Neurology, University of Lund, Malmö University Hospital, Malmö, Sweden.

Abstract:
This is a prospective study of 100 consecutive stroke patients. Within 24 h after stroke onset they were asked specifically about swallowing complaints and subjected to a clinical examination including neurologic examination, Mini-Mental test, and Barthel score. Dysphagic patients were examined with the repetitive oral suction swallow test (the ROSS test) for quantitative evaluation of oral and pharyngeal function at 24 h, after 1 week, and after 1 month. At 6 months, the patients were interviewed about persistent dysphagia. Seventy-two patients could respond reliably at 24 h after the stroke onset and 14 of these complained of dysphagia. Non-evaluable patients were either unconscious, aphasic, or demented. The presence of dysphagia was not influenced by age or other risk factors for stroke. Facial paresis, but no other clinical findings, were associated with dysphagia. Dysphagia 24 h after stroke increased the risk of pneumonia but did not influence the length of hospital stay, the manner of discharge from hospital, or the mortality. The initial ROSS test, during which the seated patient ingests water through a straw, was abnormal in all dysphagic stroke patients. One-third of the patients were unable to perform the test completely. Above all, dysfunction was disclosed during forced, repetitive swallow. All phases of the ingestion cycle were prolonged whereas the suction pressures, bolus volumes, and swallowing capacities were low. Abnormalities of quantitative swallowing variables decreased with time whereas the prevalences of swallowing incoordination and abnormal feeding-respiratory pattern became more frequent. After 6 months, 7 patients had persistent dysphagia. Five of these were initially non-evaluable because of unconsciousness, aphasia, or dementia.
More Related Videos

Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:24
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...