Related Experiment Video
Updated: Oct 24, 2026
Coculture Analysis of Extracellular Protein Interactions Affecting Insulin Secretion by Pancreatic Beta Cells
Published on: June 15, 2013
Insulin does not stimulate protein synthesis acutely in prepubertal children with insulin-dependent diabetes mellitus
M G Vogiatzi1, K S Nair, P R Beckett
1Department of Pediatrics, Baylor College of Medicine, Houston, Texas 77030, USA.

Insights
Insulin treatment in children with type 1 diabetes reduces protein breakdown but does not stimulate protein synthesis. This finding in children mirrors adult responses, indicating insulin
Area of Science:
- Pediatric Endocrinology
- Metabolic Research
- Diabetes Mellitus Type 1
Background:
- Insulin's role in protein metabolism differs between adult and young subjects.
- Adults with type 1 diabetes show decreased protein loss with insulin, mainly via reduced breakdown.
- Rodent studies suggest insulin may stimulate protein synthesis in young, growing individuals.
Purpose of the Study:
- To investigate if insulin stimulates protein synthesis in prepubertal children with insulin-dependent diabetes mellitus.
- To compare insulin's effect on protein metabolism in growing children versus adults and young rodents.
Main Methods:
- Studied five prepubertal children with type 1 diabetes (aged 8.6-11.25 years).
- Measured leucine kinetics using L-[1-13C]leucine infusion during insulin deprivation and administration.
- Analyzed serum insulin, beta-hydroxybutyrate, and free fatty acid concentrations.
Main Results:
- Insulin treatment significantly reduced protein breakdown (Leucine Ra) and leucine oxidation.
- Insulin administration normalized blood glucose levels and decreased ketone and fatty acid levels.
- Protein synthesis (nonoxidative leucine disposal) was not significantly affected by insulin treatment.
Conclusions:
- Acute insulin therapy in growing prepubertal children with type 1 diabetes reduces net protein loss.
- This reduction is primarily achieved by inhibiting protein breakdown, not by stimulating protein synthesis.
- The effect of insulin on protein metabolism in growing children is similar to that observed in adults.
Abstract:
Insulin treatment in adult type I diabetic patients decreases protein loss primarily by inhibiting protein breakdown without stimulating protein synthesis. In young growing rodents, insulin treatment has been reported to stimulate protein synthesis. We examined whether insulin stimulates protein synthesis in normally growing prepubertal children with insulin-dependent diabetes mellitus. Five prepubertal children with insulin-dependent diabetes mellitus (aged 8.6-11.25 yr) were studied in the postabsorptive state on two occasions: once during insulin deprivation (I-; blood glucose, 325 +/- 67.8 mg/dL; mean +/- SD) and once during insulin administration for 4 h (I+; blood glucose, 96 +/- 23.6 mg/dL). Leucine kinetics were measured using a 4-h primed continuous infusion of L-[1-13C]leucine. Serum insulin concentrations were lower (I- vs. I+, 0.6 +/- 0.3 vs. 7.5 +/- 4.3 microU/mL; mean +/- SD; P = 0.02), whereas serum beta-hydroxy-butyrate (I- vs. I+, 3.4 +/- 0.5 vs. 0.9 +/- 0.5 mg/dL; P < 0.001) and free fatty acid concentrations (I- vs. I+, 2.9 +/- 0.4 vs. 0.9 +/- 0.4 mEq/L; P < 0.001) were higher in the insulin-deprived state than during insulin administration. Leucine Ra, an index of protein breakdown (I- vs. I+, 200.5 +/- 23.4 vs. 167 +/- 17 mumol/kg.h; P = 0.008), and leucine oxidation (I- vs. I+, 56.5 +/- 20.7 vs. 29.6 +/- 9.3 mumol/kg.h; P = 0.03) were reduced by insulin treatment. Nonoxidative leucine disposal, an index of protein synthesis, was not affected by insulin treatment (I- vs. I+, 144 +/- 20.8 vs. 137.5 +/- 13.5 mumol/kg.h; P = 0.4). We conclude that the acute decline in net protein loss during insulin treatment in growing prepubertal children, like that in adults, is due primarily to an inhibition of protein breakdown without stimulation of protein synthesis.
More Related Videos
 07:30
Homogeneous Time-resolved Förster Resonance Energy Transfer-based Assay for Detection of Insulin Secretion
Published on: May 10, 2018
 08:04
Isolation of Primary Mouse Hepatocytes for Nascent Protein Synthesis Analysis by Non-radioactive L-azidohomoalanine Labeling Method
Published on: October 23, 2018
Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:28
Insulin: The Receptor and Signaling Pathways
 01:25
Insulin: Biosynthesis, Chemistry, and Preparation
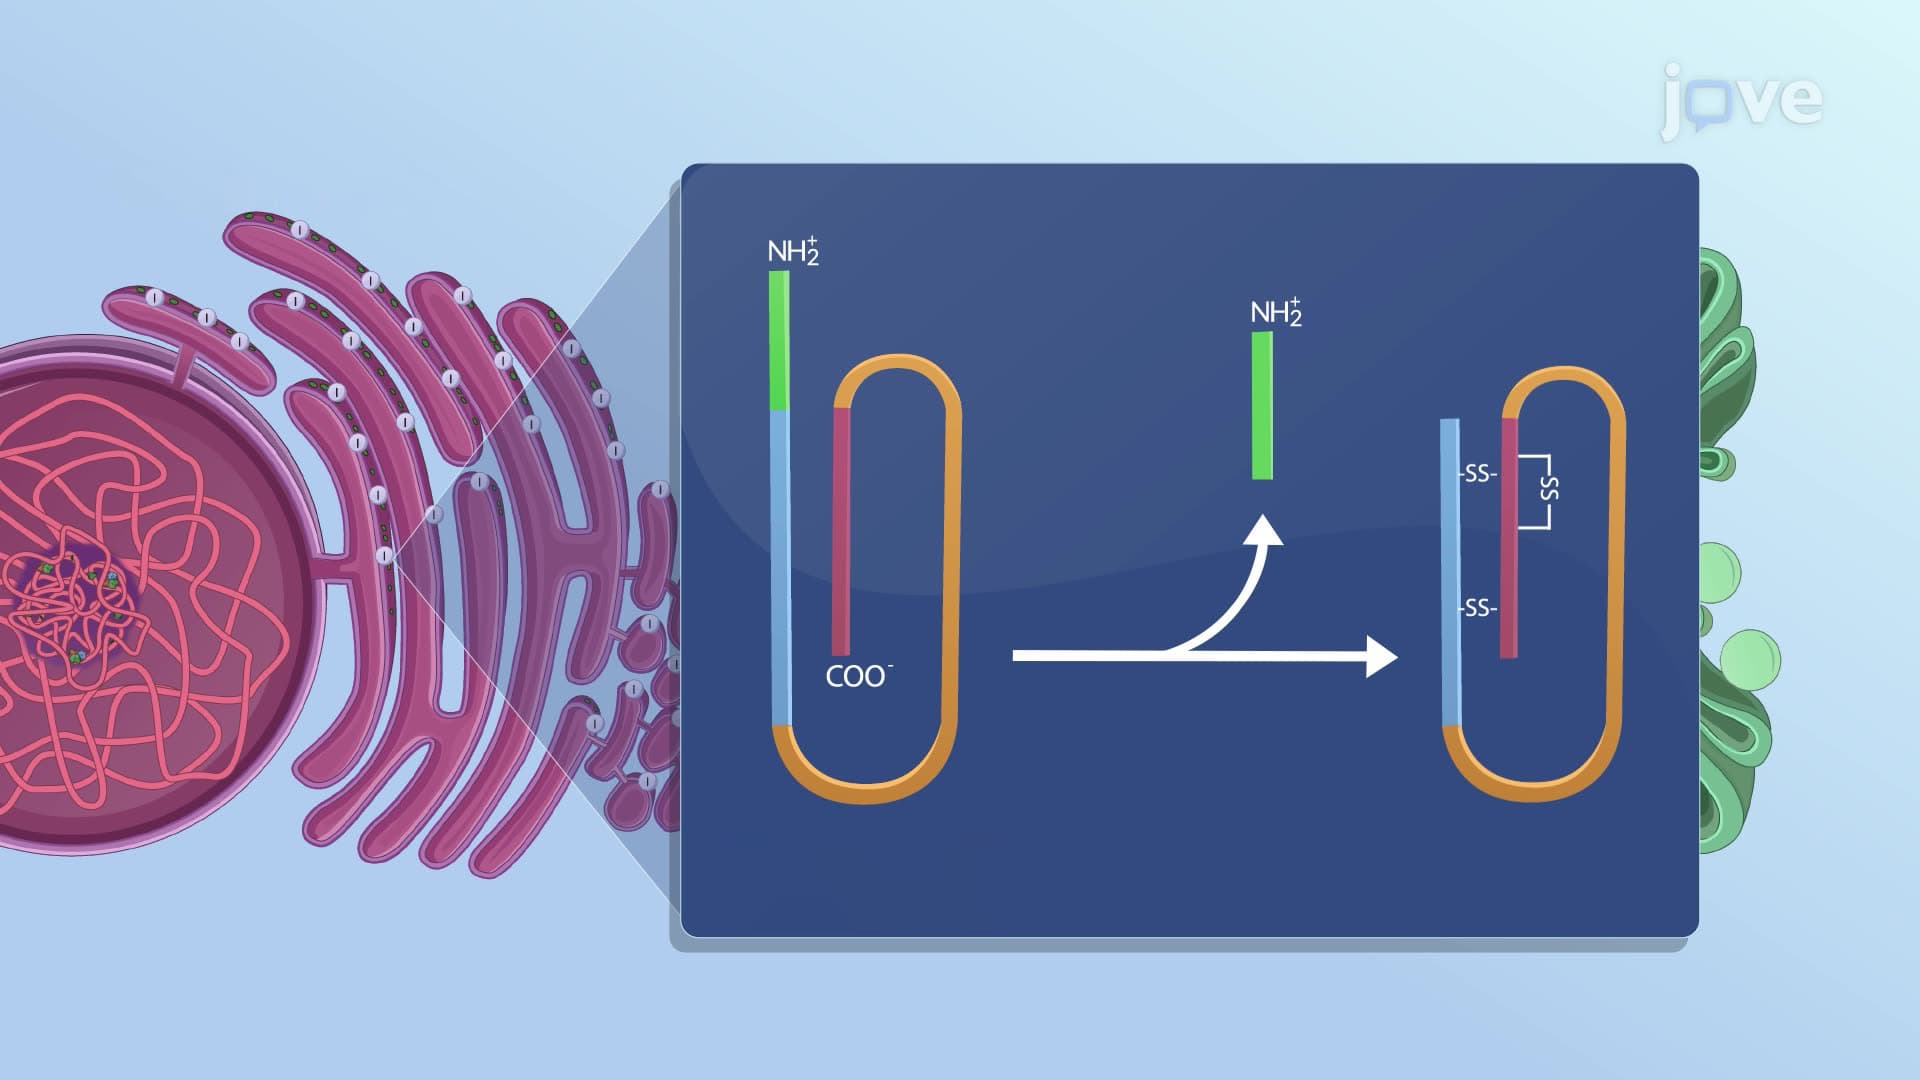
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...