Changes in function of antigen-specific lymphocytes correlating with progression towards diabetes in a transgenic model
Related Experiment Video
Updated: Oct 30, 2026
Accelerated Type 1 Diabetes Induction in Mice by Adoptive Transfer of Diabetogenic CD4+ T Cells
Published on: May 6, 2013
A Sarukhan1, A Lanoue, A Franzke
1Institut Necker, INSERM 373, 156 rue de Vaugirad, 75730 Paris, Cedex 15, France.

Mice that express influenza hemagglutinin under control of the rat insulin promoter (INS-HA) as well as a class II major histocompatibility complex (MHC)-restricted HA-specific transgenic TCR (TCR-HA), develop early insulitis with huge infiltrates, but progress late and irregularly to diabetes. Initially, in these mice, INS-HA modulates the reactivity of antigen-specific lymphocytes, such that outside the pancreas they do not cause lethal shock like their naive counterparts in single transgenic TCR-HA mice, when stimulated with high doses of antigen. Inside the pancreas, the antigen-specific cells do not initially attack the islet cells, and produce some IFN-gamma as well as IL-10 and IL-4. Spontaneous progression to diabetes, which can be accelerated by cyclophosphamide injection, is accompanied by a 10-fold increase in IFN-gamma and a 3-fold decrease in IL-10 and IL-4 production by the locally residing antigen-specific T cells. Also, total islets from non-diabetic mice contain more TNF-alpha, compared with diabetic mice. This scenario is consistent with the view that beta cell destruction depends upon the increased production of certain pro-inflammatory cytokines by infiltrating T cells. Our inability to detect Fas expression on beta cells, but not on lymphoid cells, in diabetic and non-diabetic mice, puts some constraints on the role of Fas in beta cell destruction.
Mice that express influenza hemagglutinin under control of the rat insulin promoter (INS-HA) as well as a class II major histocompatibility complex (MHC)-restricted HA-specific transgenic TCR (TCR-HA), develop early insulitis with huge infiltrates, but progress late and irregularly to diabetes. Initially, in these mice, INS-HA modulates the reactivity of antigen-specific lymphocytes, such that outside the pancreas they do not cause lethal shock like their naive counterparts in single transgenic TCR-HA mice, when stimulated with high doses of antigen. Inside the pancreas, the antigen-specific cells do not initially attack the islet cells, and produce some IFN-gamma as well as IL-10 and IL-4. Spontaneous progression to diabetes, which can be accelerated by cyclophosphamide injection, is accompanied by a 10-fold increase in IFN-gamma and a 3-fold decrease in IL-10 and IL-4 production by the locally residing antigen-specific T cells. Also, total islets from non-diabetic mice contain more TNF-alpha, compared with diabetic mice. This scenario is consistent with the view that beta cell destruction depends upon the increased production of certain pro-inflammatory cytokines by infiltrating T cells. Our inability to detect Fas expression on beta cells, but not on lymphoid cells, in diabetic and non-diabetic mice, puts some constraints on the role of Fas in beta cell destruction.
More Related Videos
 11:31
High-Efficiency Generation of Antigen-Specific Primary Mouse Cytotoxic T Cells for Functional Testing in an Autoimmune Diabetes Model
Published on: August 16, 2019
 10:03
Bioluminescent Monitoring of Graft Survival in an Adoptive Transfer Model of Autoimmune Diabetes in Mice
Published on: November 18, 2022
Related Concept Videos
 01:26
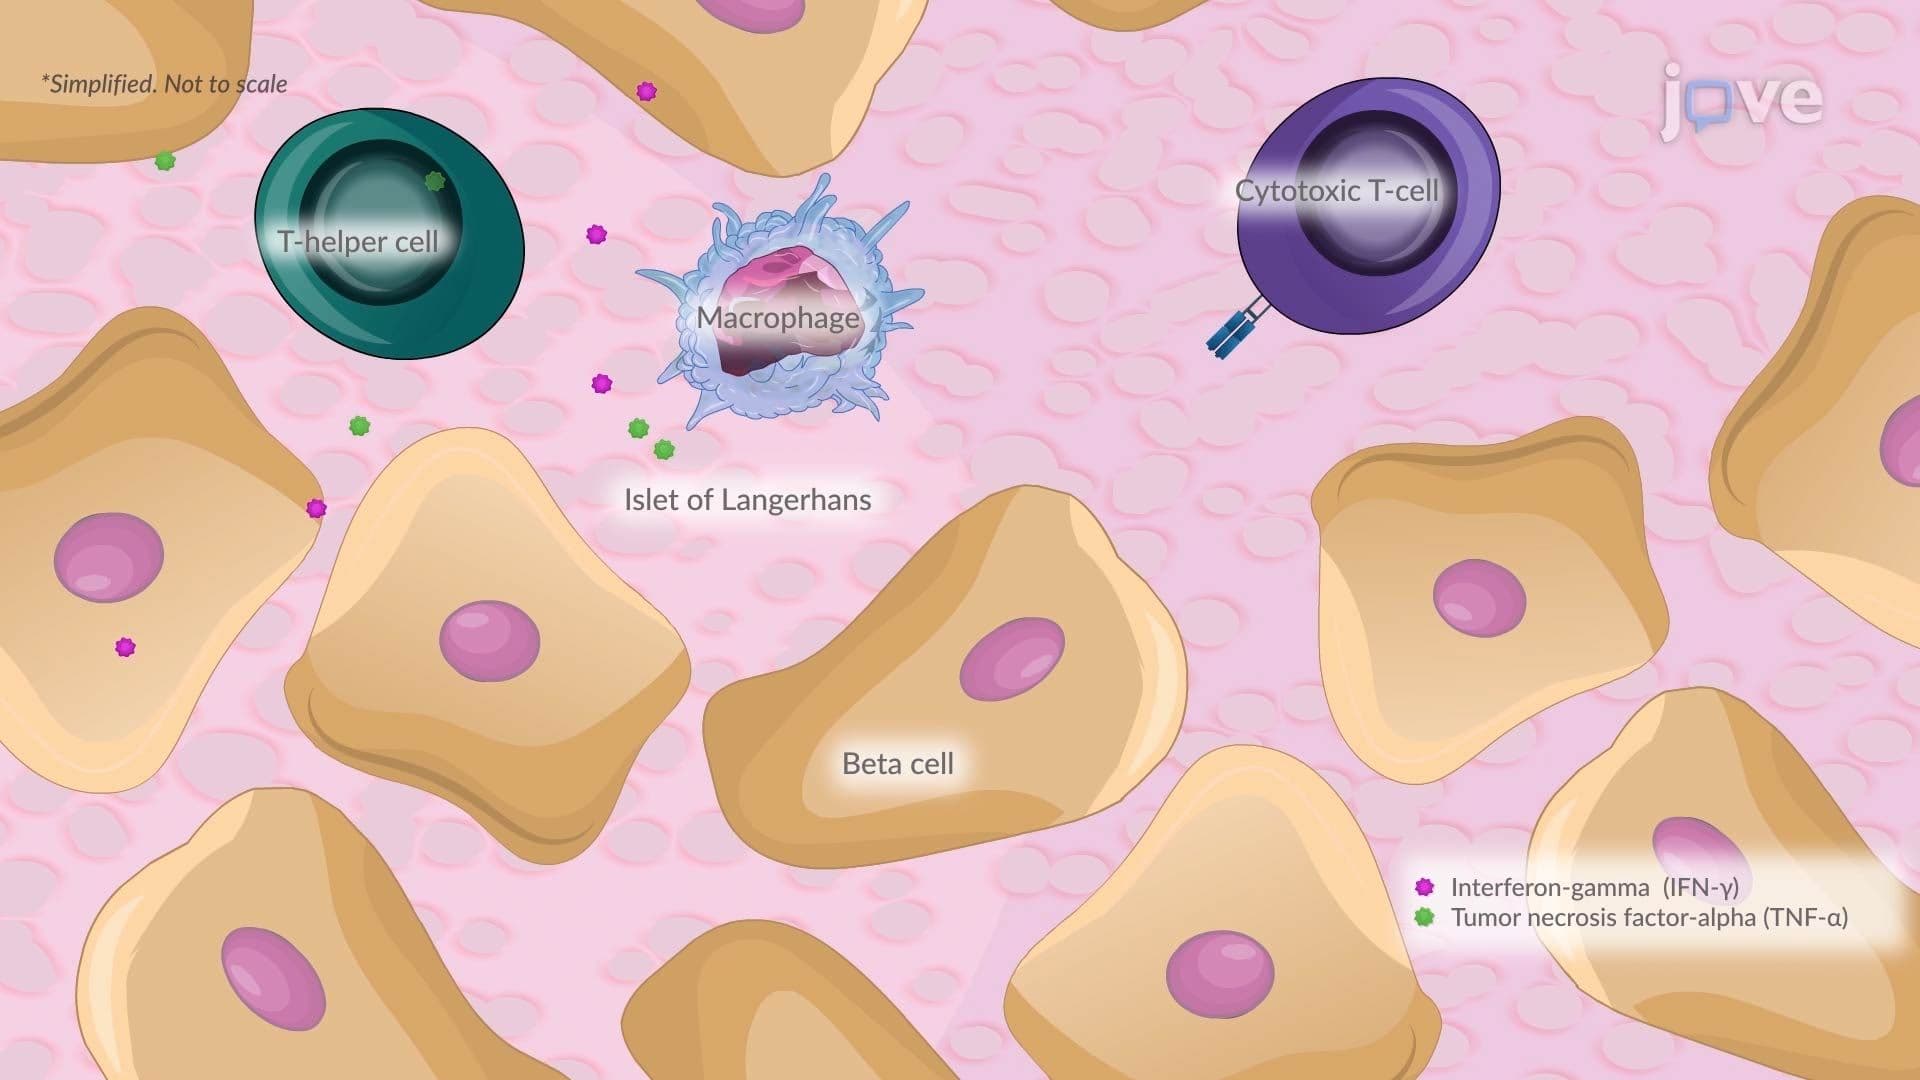
Type I Diabetes II: Pathophysiology
 01:12
Type I Diabetes I: Introduction
 01:24
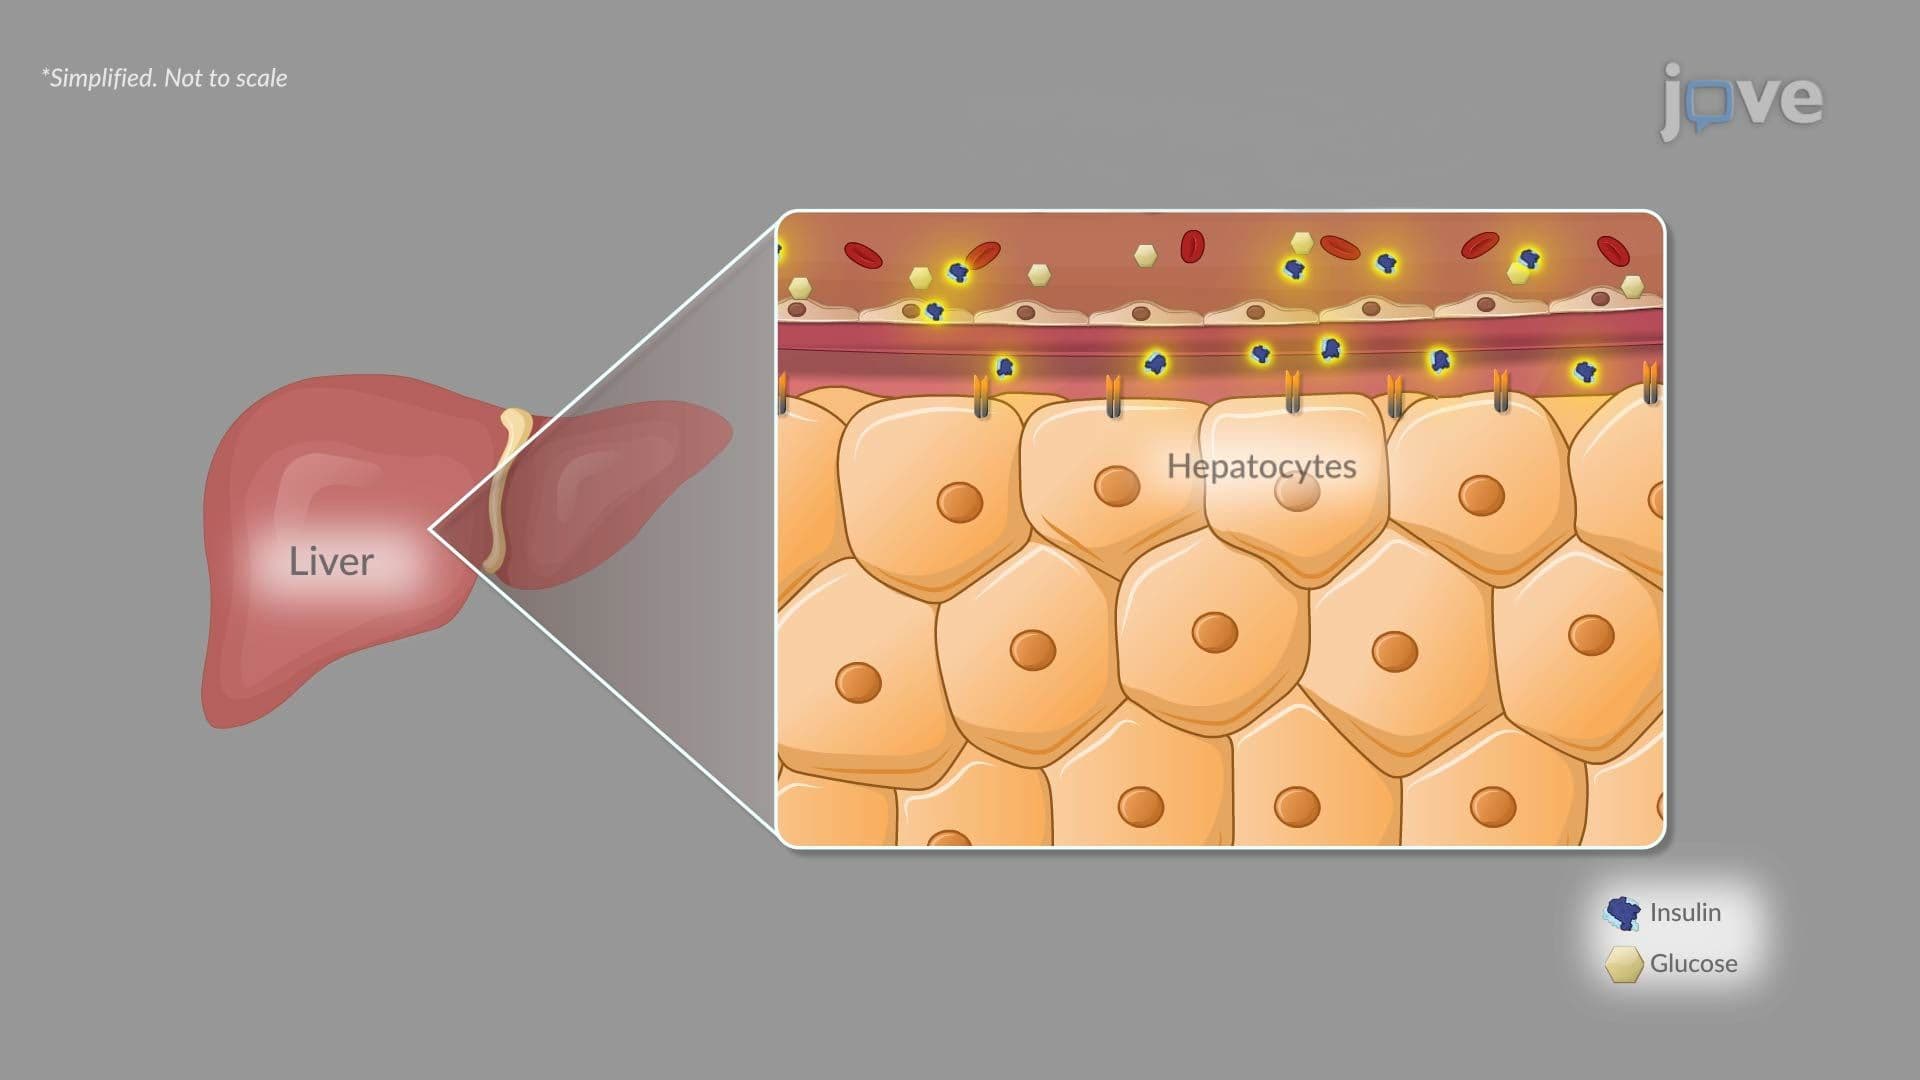
Type II Diabetes II: Pathophysiology
 01:40
Cell-mediated Immune Responses
 01:26
Type II Diabetes I: Introduction
 01:19
Type I Diabetes III: Clinical Manifestations