
Ouabain reduces net acid secretion and increases pHi by inhibiting NH4+ uptake on rat tIMCD Na(+)-K(+)-ATPase
1Division of Renal Diseases and Hypertension, University of Texas Medical School at Houston 77030, USA.

Abstract:
In the rat terminal inner medullary collecting duct (tIMCD), Na+ pump inhibition reduces transepithelial net acid secretion (JtAMM) [JH = total CO2 absorption (JtCO2)+ total ammonia secretion] and increases resting intracellular pH (pHi). The increase in pHi and reduction in JH that follow ouabain addition do not occur in the absence of NH4+ nor when NH4+ is substituted with another weak base. The purpose of this study was to explore the mechanism of the NH4(+)-dependent reduction in JtCO2 and increase in pHi that follow ouabain addition. We hypothesized that NH4+ enters the tIMCD cell through the Na(+)-K(+)-ATPase with proton release in the cytosol. To test this hypothesis, tIMCDs were dissected from deoxycorticosterone-treated rats and perfused in vitro with symmetrical physiological saline solutions containing 6 mM NH4Cl. Since K+ and NH4+ compete for a common binding site on the Na+ pump, increasing extracellular K+ should limit NH4+ (and hence net H+) uptake by the Na+ pump. Upon increasing extracellular K+ concentration from 3 to 12 mM, the NH4(+)-dependent, ouabain-induced increase in pHi and reduction in JtCO2 were attenuated. In the presence but not in the absence of NH4+, reducing Na+ pump activity by limiting Na+ entry reduced JtCO2 and attenuated ouabain-induced alkalinization. Ouabain-induced alkalinization was not dependent on the presence of HCO3-/CO2 and was not reproduced with BaCl2 or bumetanide addition. Therefore, ouabain-induced alkalinization is not mediated by the Na(+)-K(+)-2Cl- cotransporter or a HCO3- transporter and is not mediated by changes in membrane potential. In conclusion, on the basolateral membrane of the tIMCD cell, NH4+ uptake is mediated by the Na(+)-K(+)-ATPase. These data provide an explanation for the reduction in net acid secretion in the tIMCD observed following administration of amiloride or with dietary K+ loading.
Related Concept Videos
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:18
Indirect-Acting Cholinergic Agonists: Mechanism of Action
Reversible inhibitors like edrophonium bind to a specific part of the enzyme called the anionic catalytic site. They form noncovalent bonds, which means they are not strongly attached to the enzyme. This creates a temporary and less stable enzyme–inhibitor complex, leading to...
 01:13
Acid Suppressive Drugs for Peptic Ulcer Disease: Proton Pump Inhibitors
Gastric acid, a potent cocktail of hydrogen and chloride ions, is produced in specialized parietal cells within the...
 01:29
Renal Regulation of Acid-Base Balance
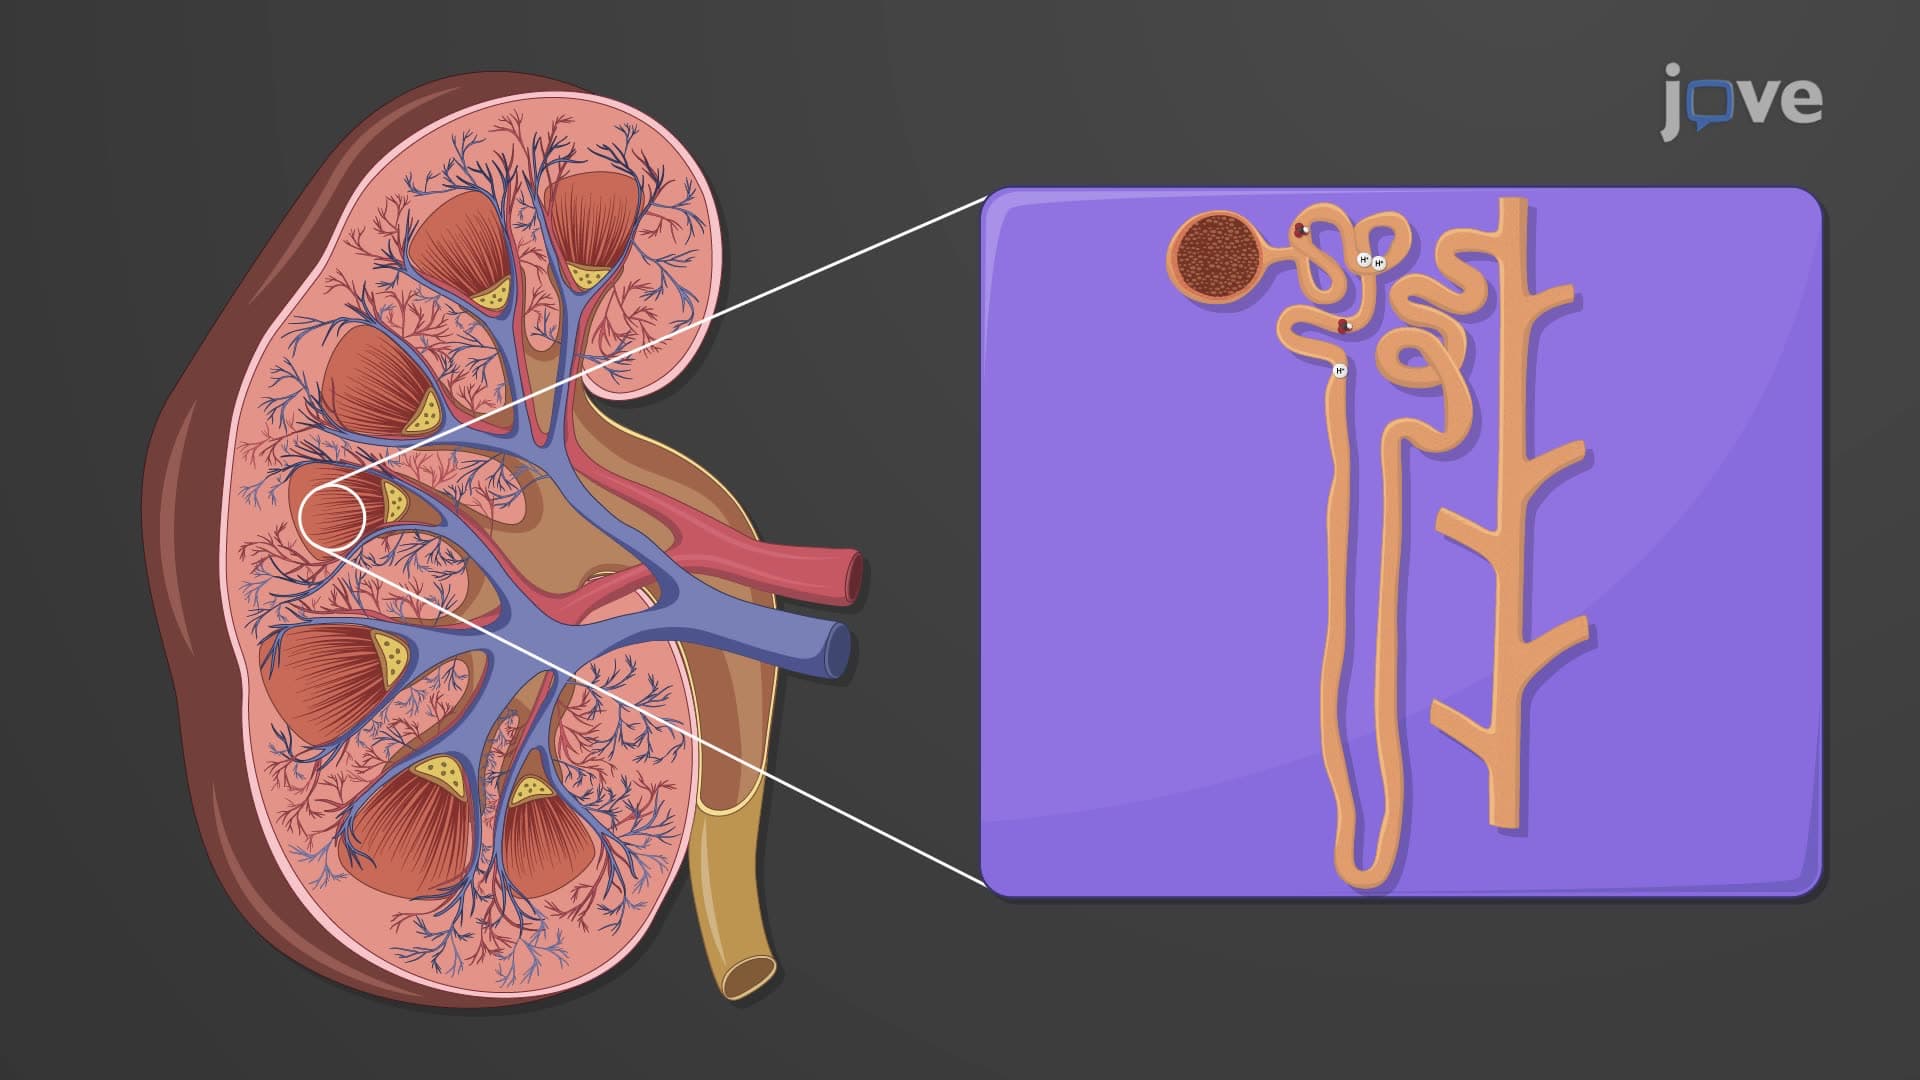
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...