Related Experiment Video
Updated: Aug 8, 2026

Electrophysiology on Isolated Brainstem-spinal Cord Preparations from Newborn Rodents Allows Neural Respiratory Network Output Recording
Published on: November 19, 2015
Control of respiration in newborn babies. IV. Rib cage stability and respiratory regulation

Insights
Breathing patterns in preterm infants influence their response to carbon dioxide (CO2). An unstable breathing pattern predicts a rate increase response to CO2, while a stable pattern predicts an amplitude increase response.
Area of Science:
- Neonatal Physiology
- Respiratory Control
Background:
- Infants exhibit varying breathing patterns.
- Carbon dioxide (CO2) exposure is a common method to study respiratory control.
Purpose of the Study:
- To reexamine the relationship between pre-exposure breathing patterns and subsequent respiratory responses to CO2 in preterm infants.
- To investigate how breathing excursion patterns affect respiratory depth and rate changes.
Main Methods:
- Reanalysis of recordings from a previous study involving 13 preterm infants (32-43 weeks postmenstrual age).
- Categorization of breathing patterns into 'stable' (in-phase thoracic and abdominal excursions) and 'unstable' (inverted, incongruous, or variable excursions).
- Correlation of pre-exposure breathing patterns with induced respiratory responses (Type A: increased amplitude, Type B: increased rate) to 4% CO2 exposure.
Main Results:
- An 'unstable' pre-exposure breathing pattern was associated with a 60% incidence of 'Type B' (rate increase) response to CO2.
- 'Stable' pre-exposure breathing patterns led to a 59% incidence of 'Type A' (amplitude increase) response.
- Breathing variability in preterm infants was highest with an 'unstable' pattern.
- Increasing postmenstrual age correlated with more 'stable' breathing patterns and fewer 'Type B' CO2 responses.
Conclusions:
- The pre-exposure breathing excursion pattern significantly influences the type of respiratory response to CO2 in preterm infants.
- Maturation leads to more stable breathing patterns, potentially due to improved neuromuscular control of the rib cage and stabilized pulmonary vagal input.
- Findings suggest a dynamic interaction between thoracic wall mechanics and pulmonary mechanoreceptors in respiratory regulation.
Abstract:
The recordings from an earlier study regarding the respiratory depth and rate changes induced by exposure to 4% CO2 in air in 13 babies with PM age varying between 32 and 43 weeks were reexamined with regard to the pattern of thoracic abdominal breathing excursion in breathing immediately prior to the CO2 exposure and the type of response induced. The pattern was called "stable" when the thoracic breathing excursions were in phase and congruent with the abdominal ones. When the thoracic excursions in comparison with the abdominal excursions were totally inverted, or incongruous but in phase, or rapidly varying between those two, the pattern was called "unstable". "Unstable" pattern of the breathing prior to the CO2 exposures was followed in an incidence of 60% by the type of response to CO2 which is characterized by a prompt rate increase (the "Type B" response) and only in 16% by the type characterized by an increased breathing amplitude (the "Type A" response). When the excursion pattern of the breathing prior to the CO2 exposures was "stable" "Type A" responses were induced in 59% and "Type B" responses in only 14%. The excursion pattern present when a baby is exposed to 4% CO2 thus seems to affect the type of respiratory depth and rate changes achieved. With increasing postmenstrual age the excursion pattern of the spontaneous breathing is more often "stable" and respiratory depth and rate changes of the "Type B" induced by CO2 less common. The variabilities of the breathing seen preferably in the preterm baby regarding regularity, rate and tidal volumes (as they could be approximated by the registration methods used) were noted most when the excursion pattern was "unstable". The results can be hypothetically interpreted to indicate a dynamic interaction between the thoracic wall and pulmonary mechanoreceptor systems of respiratory regulation. The decreasing variability of the breathing seen with increasing maturation in the baby could be explained by an increasing maturation of the neuromuscular ability to provide stability to the rib cage which would act stabilizing on the pulmonary vagal afferent input to the respiratory center.
Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:23
Mechanism of Breathing II: Expiration
Expiration, or exhaling, is a complex physiological process that begins as the inspiratory muscles begin to relax. This relaxation triggers a series of events that epitomize the efficiency of the respiratory system.
Mechanism of Expiration:
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical level,...
 01:22
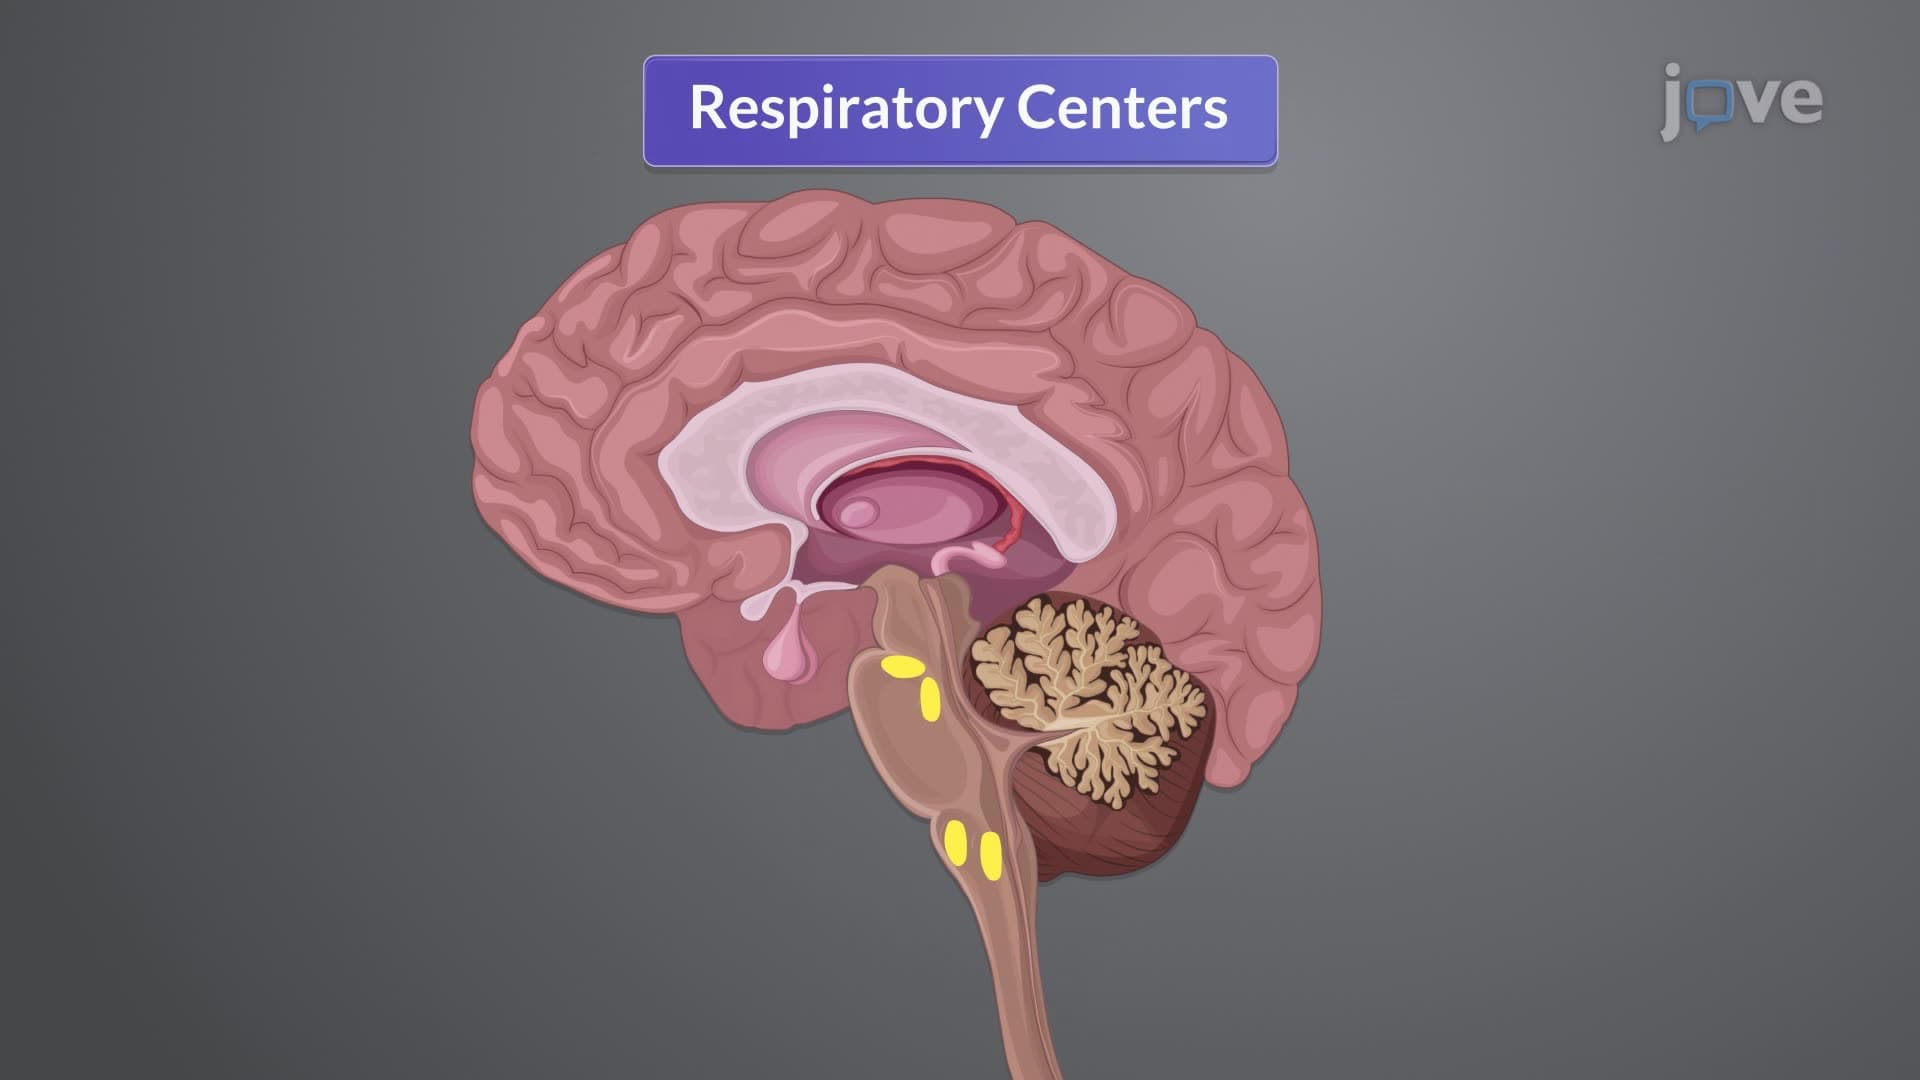
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers: