Related Experiment Video
Updated: Aug 19, 2026

In vivo Characterization of Endocrine Disrupting Chemical Effects via Thyroid Hormone Action Indicator Mouse
Published on: October 6, 2023
[Therapy of hypo- and hyperthyroidism in pregnancy]
1Abteilung für Nuklearmedizin und Spezielle Endokrinologie, Landeskrankenhauses Klagenfurt. peter.lind@lkh-klg.co.at

Abstract:
Therapy of thyroid dysfunction needs a close cooperation between endocrinologist and gynecologist. In addition to a number of metabolic changes during pregnancy, the diaplacentar transfer of different substances (thionamides, antibodies) has to be considered. Pregnant women with overt and subclinical hypothyroidism should be treated using L-Thyroxine with the bTSH between 1 and 2 mU/l. Many of the women need an increase of the L-Thyroxine dose during pregnancy. Overt hyperthyroidism (mostly due to Graves' disease) has to be treated immediately after diagnosis using thionamides. Because thionamides cross the placenta, the dose should be as low as possible with the fT4 in upper level and bTSH in the lower level of normal range. Most studies show, that both methimazole (MI) and propylthiouracil (PTU) can be used in pregnancy. Although PTU is preferred especially in the USA, an advantage of PTU over MI is not proven. Surgery is necessary in only few cases of hyperthyroidism during pregnancy with the optimal time for surgery during the second trimester. In case of subclinical hyperthyroidism and HCG induced hyperthyroidism several controls of thyroid function should be performed to decide whether treatment is necessary.
More Related Videos
Related Concept Videos
 01:20
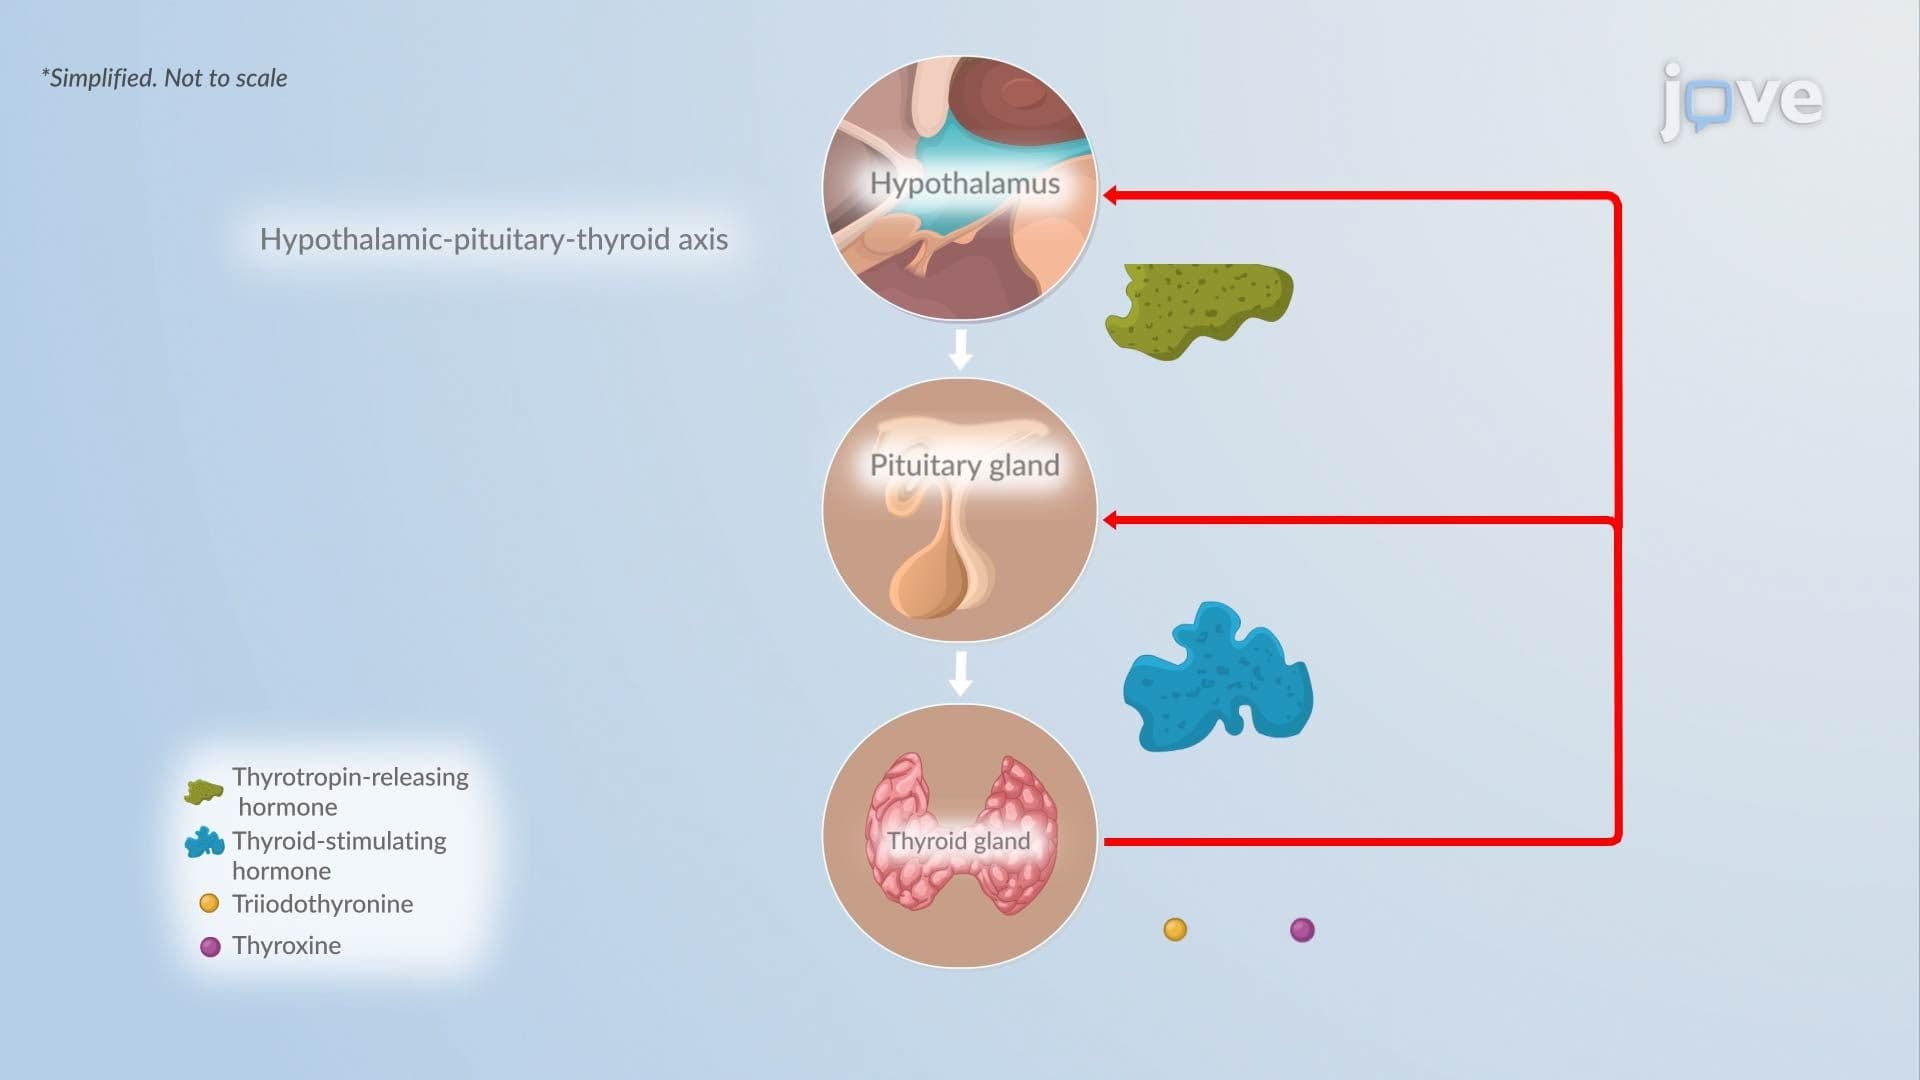
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology