Related Experiment Video
Updated: Aug 13, 2026


Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Massive hiatus hernia: evaluation and surgical management
D E Maziak1, T R Todd, F G Pearson
1University of Toronto, Department of Thoracic Surgery, Ontario, Canada.

Objective:
Paraesophageal hernias represent advanced degrees of sliding hiatus hernia with intrathoracic displacement of the intraesophageal junction. Gastroesophageal reflux disease occurs in most cases, resulting in acquired short esophagus, which should influence the type of repair selected.
Methods:
Between 1960 and 1996, 94 patients with massive, incarcerated paraesophageal hiatus hernia were operated on at the Toronto General Hospital. The mean age was 64 years (39 to 85 years), with a female to male ratio of 1.8:1. Organoaxial volvulus was present in 50% of cases. Clinical presentation in these patients included postprandial pain in 56%, dysphagia in 48%, chronic iron deficiency anemia in 38%, and aspiration in 29%. Symptomatic reflux, either present or remote, was recorded in 83% of cases. All patients underwent endoscopy by the operating surgeon. In 91 of 94 patients, the esophagogastric junction was found to be above the diaphragmatic hiatus, denoting a sliding type of hiatus hernia. Gross, endoscopic peptic esophagitis was observed in 36% of patients: ulcerative esophagitis in 22% and peptic esophagitis with stricture in 14%. A complete preoperative esophageal motility study was obtained for 41 patients. The lower sphincter was hypotensive in 21 patients (51%), and the amplitude of peristalsis in the distal esophagus was diminished in 24 patients (59%). These abnormalities are both features of significant gastroesophageal reflux disease. In 13 recent, consecutive patients with paraesophageal hernia, the distance between the upper and lower esophageal sphincters was measured during manometry. The average distance was 15.4 +/- 2.33 cm (11 to 20 cm), which is consistent with acquired short esophagus. The normal distance is 20.4 cm +/- 1.9 (p < 0.0001).
Results:
All 94 patients were treated surgically: 97% had a transthoracic repair with fundoplication. A gastroplasty was added in 75 cases (80%) because of clearly defined or presumed short esophagus. There were two operative deaths, and two patients were never followed up. Among the 90 available patients, the mean follow-up was 94 months; median follow-up was 72 months. Seventy-two patients (80%) are free of symptoms (excellent result); 13 (13%) have inconsequential symptoms requiring no therapy (good result); and three patients (4%) are improved but have symptoms requiring medical therapy or interval dilatation (fair result). Two patients had poor results because of recurrent hernia and severe reflux. Both were successfully treated by reoperation with the addition of gastroplasty because of acquired shortening, which was not recognized at the first operation.
Conclusions:
Most of these 94 patients had symptoms or endoscopic, manometric, and operative findings that were consistent with a sliding hiatus hernia. There was a high incidence of endoscopic reflux esophagitis and of acquired short esophagus. True paraesophageal hernia, with the esophagogastric junction in a normal abdominal location, appears rare. Our observations were supported by measurements obtained at preoperative endoscopy and manometry, and by findings at the time of surgical repair. These observations support the choice of a transthoracic approach for repair in most patients.


Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:25
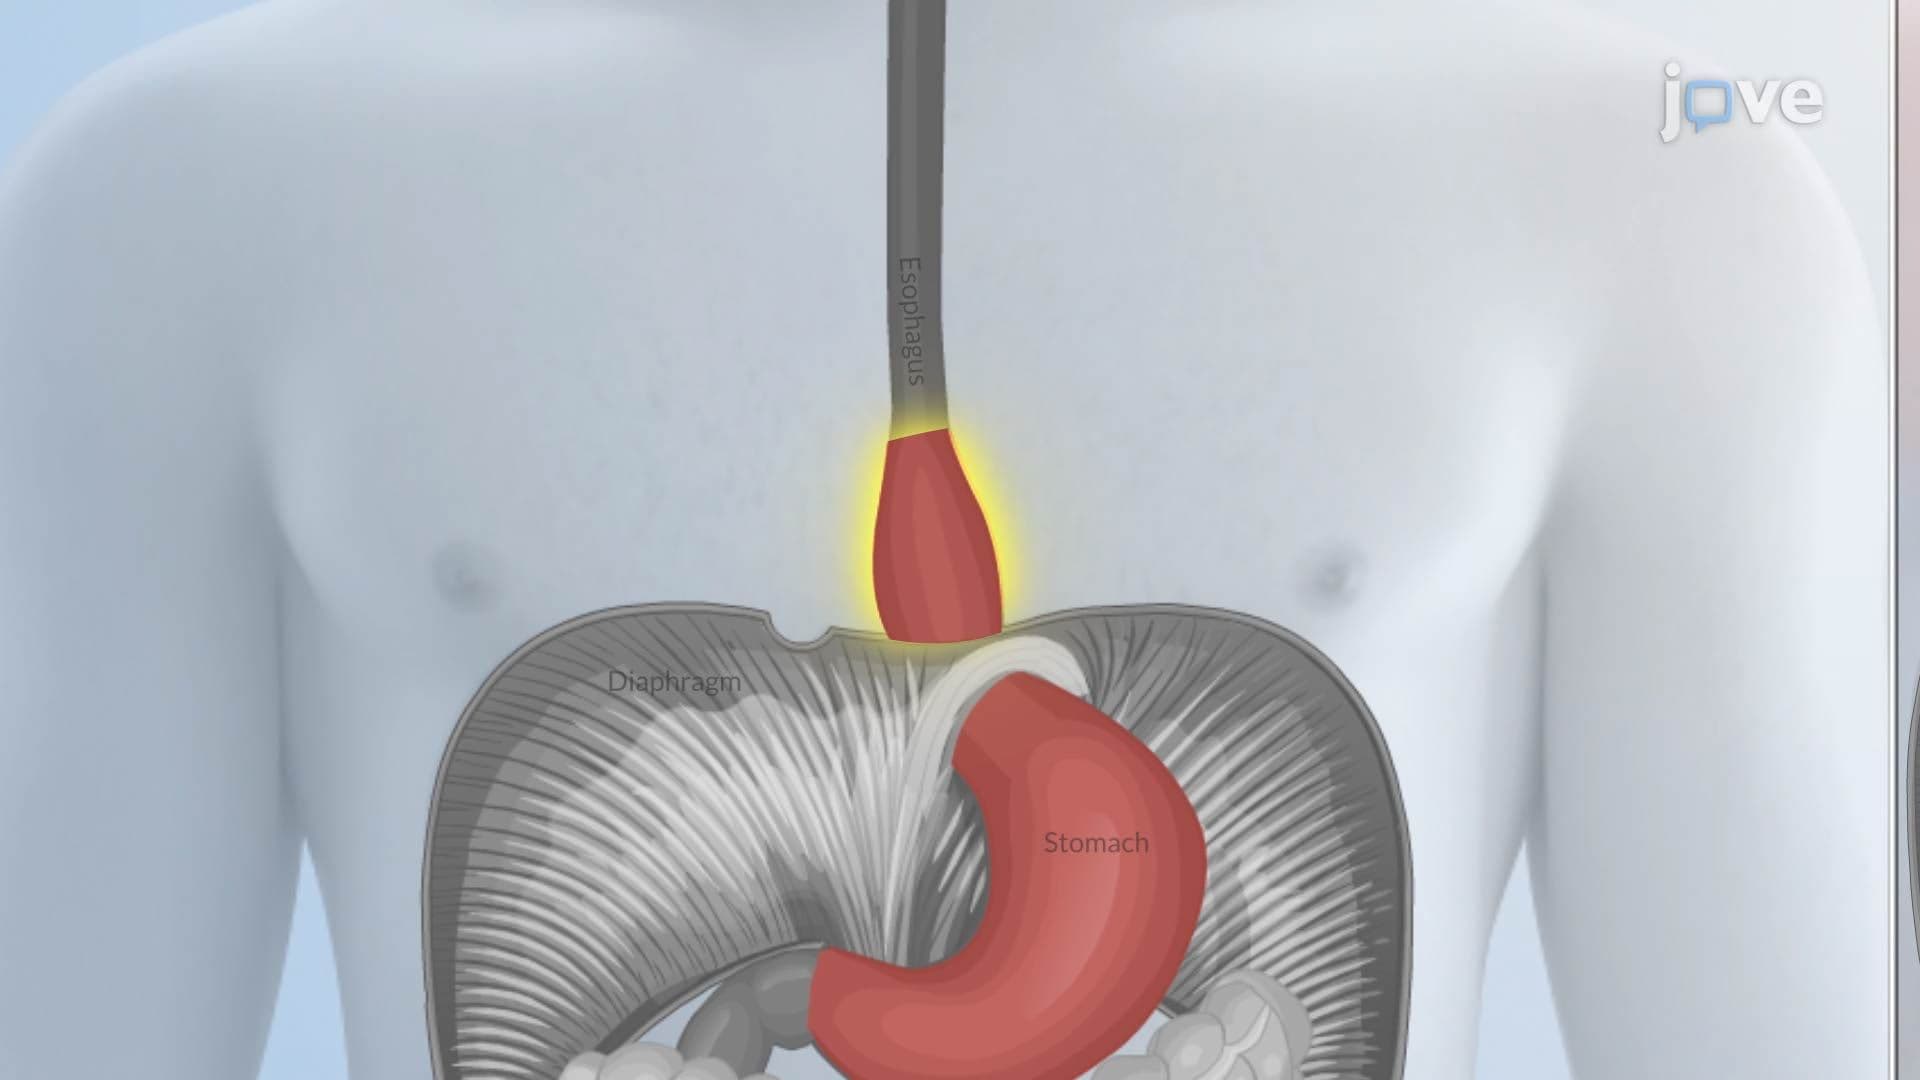
Hiatal Hernia