Missed diaphragmatic injuries and their long-term sequelae
Related Experiment Video
Updated: Oct 30, 2026

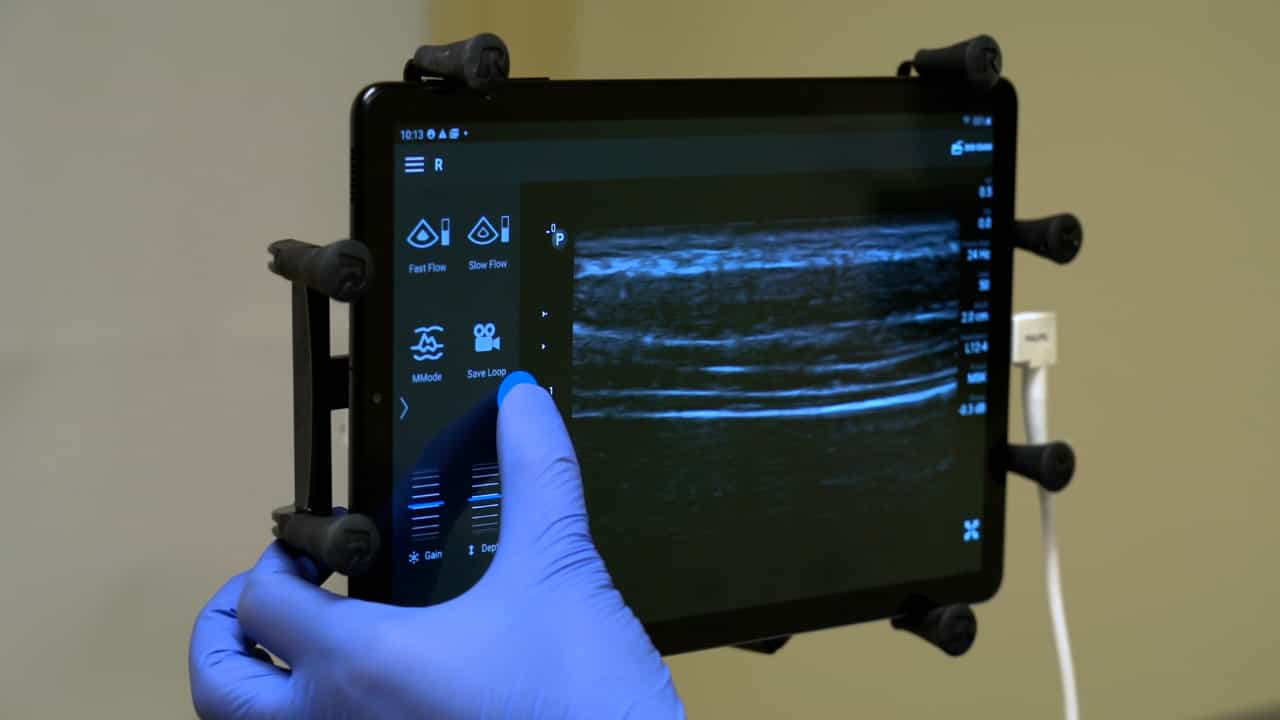
Diaphragmatic Ultrasound in Adults: Image Acquisition and Interpretation
Published on: January 31, 2025
P U Reber1, B Schmied, C A Seiler
1Department of Visceral and Transplantation Surgery, Inselspital, University of Bern, Switzerland.

Background:
Blunt or penetrating truncal traumas can result in diaphragmatic rupture or injury. Because diaphragmatic defects are difficult to diagnose, those that are missed may present with latent symptoms of obstruction of herniated viscera.
Methods:
A chart review of all patients admitted with late presentations of posttraumatic diaphragmatic hernias from 1980 to 1996 was undertaken.
Results:
Ten patients with posttraumatic diaphragmatic hernias were treated in this specified period. There were six males and four females with a mean age of 65 years. Eight patients sustained blunt truncal traumas and two patients sustained penetrating truncal traumas. The hernias occurred in two patients on the right and in eight patients on the left side and contained the liver (n = 2), bowel (n = 10), stomach (n = 4), omentum (n = 5), or spleen (n = 1). The time until the hernias became clinically symptomatic ranged from 20 days to 28 years. In all but one patient, either routine chest roentgenograms or upper gastrointestinal contrast studies were diagnostic. All 10 patients underwent laparotomy (n = 9) or thoracotomy (n = 2) with direct repair of the diaphragmatic defect. One patient died 3 days after the operation, representing a mortality of 10%; the morbidity was 30%.
Conclusion:
Initial recognition and treatment of diaphragmatic rupture or injury is important in avoiding long-term sequelae.
Related Concept Videos
 01:10
Atelectasis II: Pathophysiology
 01:08
Pneumothorax II: Pathophysiology
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema