

A comparison between the influence of pindolol and propranolol on the response of plasma potassium to catecholamines

Abstract:
The influence of propranolol (0.3 and 1.0 mg/kg) and of D,L-4-(2-hydroxy-3-isopropylamino-propoxy)-indol-hydrochloride (pindolol, LB 46) (0.10, 0.25 and 0.50 mg/kg) on the responses of plasma potassium levels of anaesthetized dogs to slow i.v. infusions of adrenaline, noradrenaline and isoprenaline (5 mug/kg-min-1) was studied. Adrenaline and noradrenaline infusions regularly evoked a dual response (hyperkaliemia followed by hypokaliemia), whereas isoprenaline caused either similar effects or only a decrease of plasma potassium. Propranolol abolished the hypokaliemic phase of the responses to adrenaline, noradrenaline and isoprenaline; the lower dose used had no effect on the primary increase in plasma potassium, but the dose of 1.0 mg/kg modified this part of the response, which was reduced and became less steep. Pindolol antagonized in a dose dependent way the hypokaliemic phase of the responses to adrenaline, noradrenaline and isoprenaline, but did not interfere with the early rise in plasma potassium, thus being more specific than propranolol. It is concluded that the secondary decrease in plasma potassium is due to an activation of beta-receptors, whereas the initial increase is caused by alpha-receptor stimulation. Propranolol shows, in the 1.0 mg/kg dose, some alpha-blocking activity, thus contrasting with pindolol, which is devoid of this effect and therefore appears to be especially suitable for tentative characterization of adrenergic receptors.

Related Concept Videos
 01:25
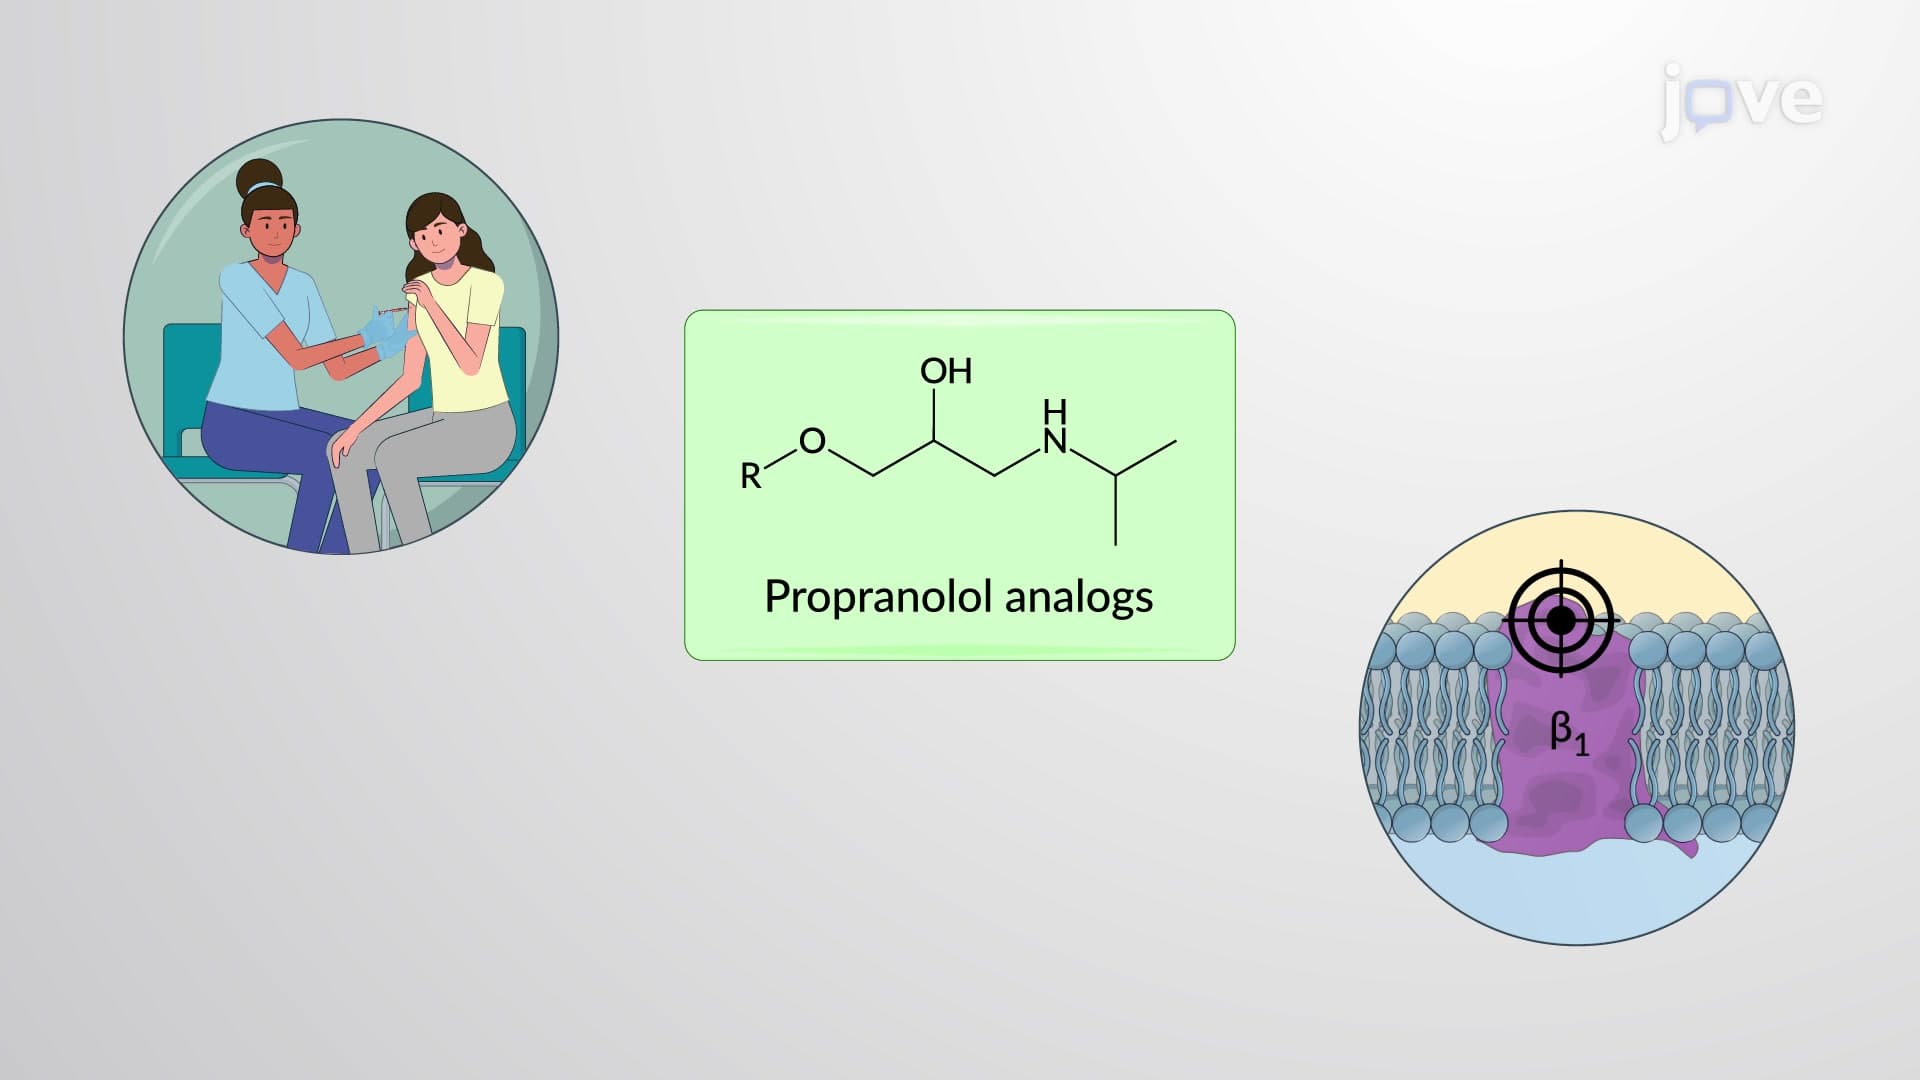
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:15
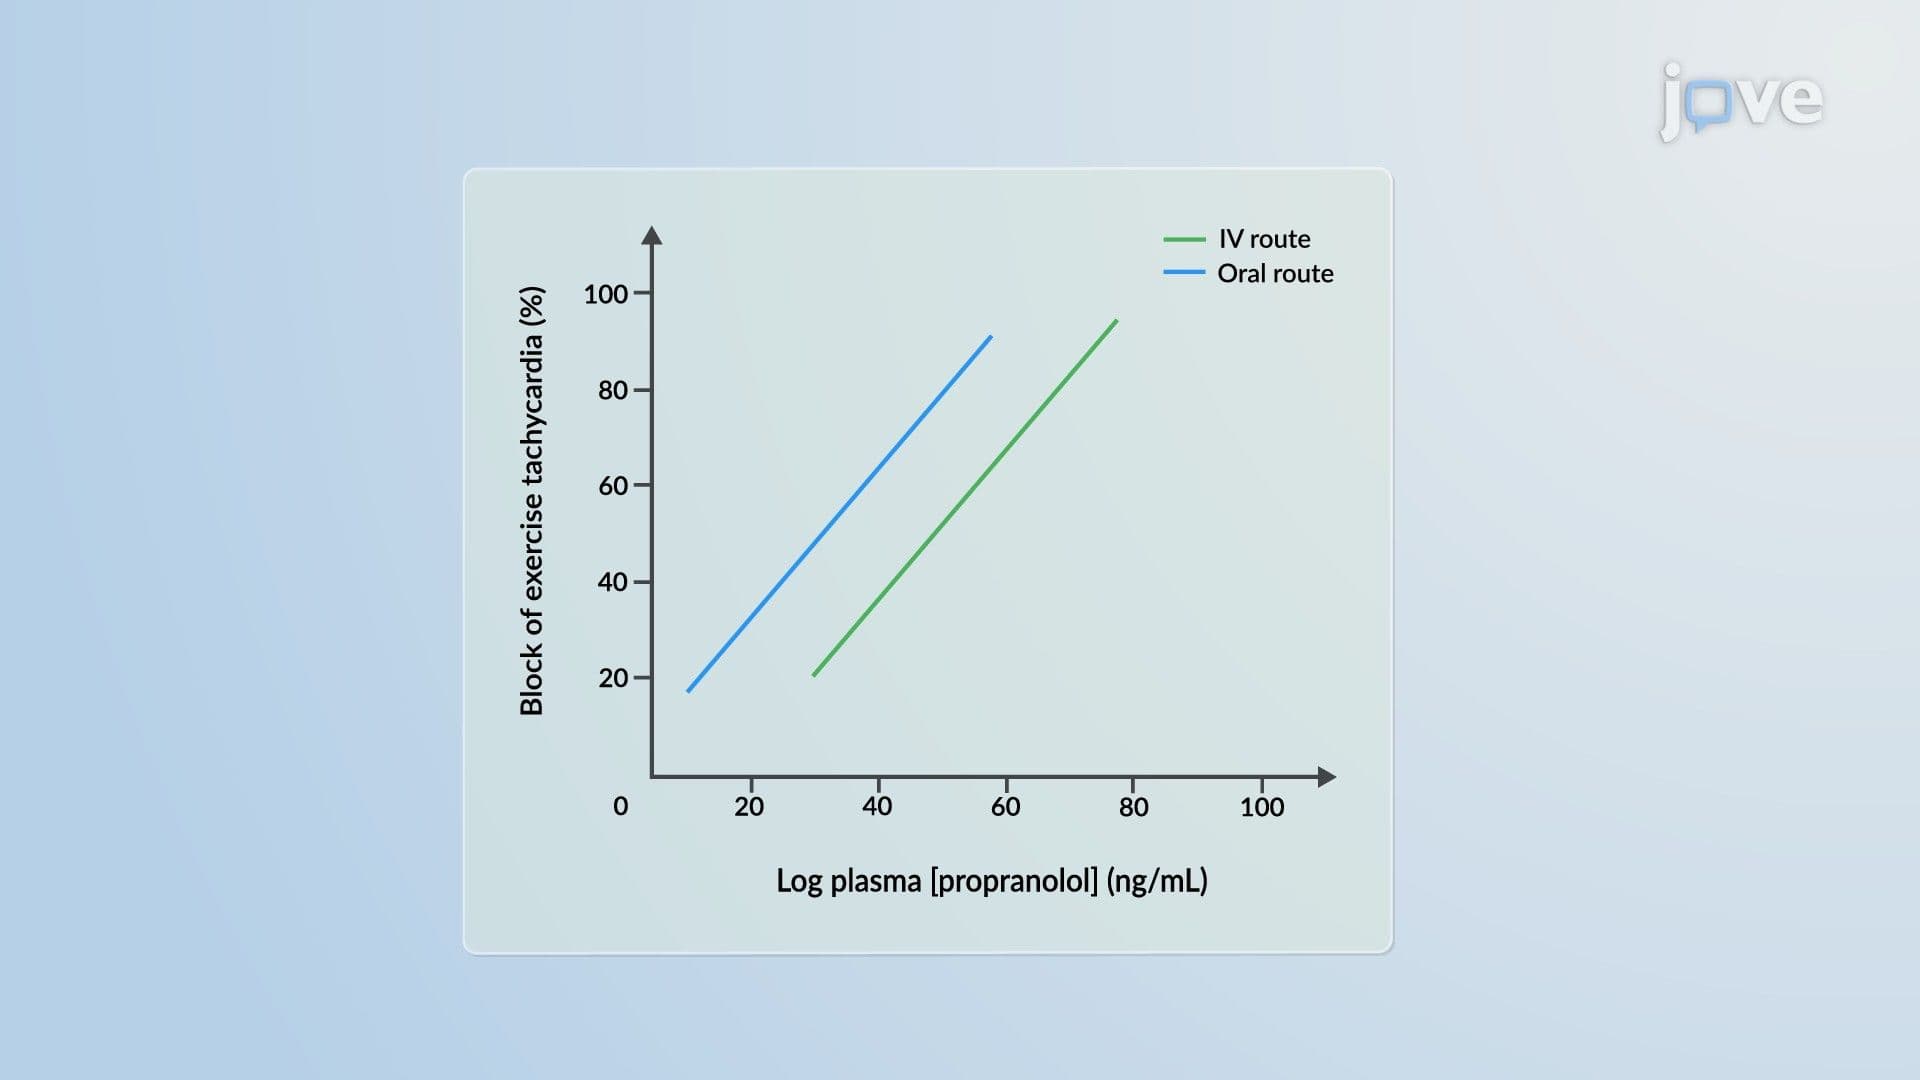
Pharmacodynamic Models: Logarithmic Concentration–Effect Model