Respiratory oscillation mechanics in infants with bronchiolitis during mechanical ventilation
Related Experiment Video
Updated: Oct 30, 2026
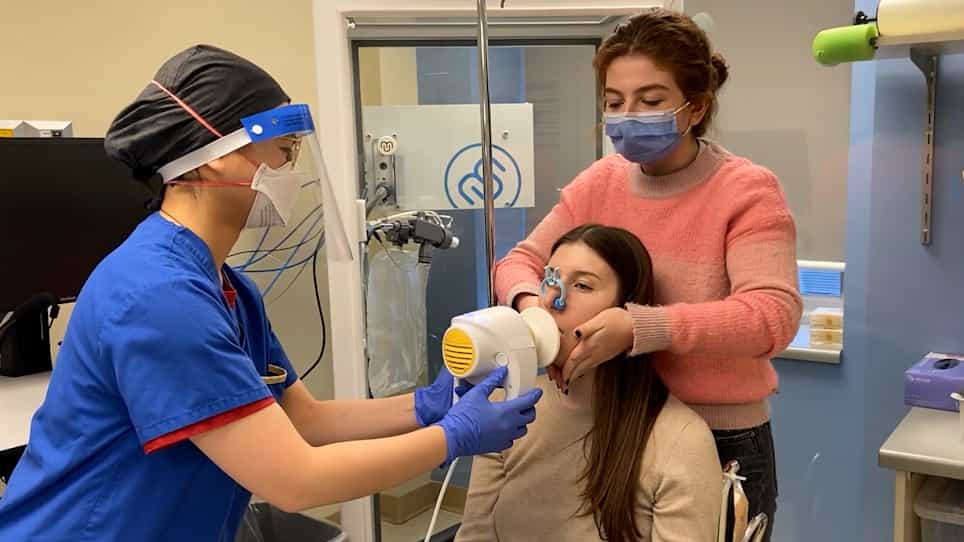
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
R Gauthier1, C Beyaert, F Feillet
1Laboratoire d'Explorations Fonctionnelles Pédiatriques, Hôpital-d'Enfants Vandoeuvre les Nancy, France.

Insights
Respiratory oscillation mechanics in infants with bronchiolitis reveal distinct patterns related to lung volume and airflow limitation. Positive end-expiratory pressure (PEEP) effectively improved these parameters, aiding mechanical ventilation strategies.
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Critical Care Medicine
Background:
- Bronchiolitis is a common pediatric respiratory illness often requiring mechanical ventilation.
- Understanding respiratory mechanics is crucial for optimizing ventilation strategies in infants.
Purpose of the Study:
- To characterize respiratory oscillation mechanics in infants with bronchiolitis.
- To investigate the effects of positive end-expiratory pressure (PEEP) on these mechanics.
Main Methods:
- Six infants undergoing mechanical ventilation for bronchiolitis were studied.
- Respiratory impedance was measured using a 20 Hz sinusoidal pressure variation.
- Measurements were taken at varying levels of PEEP (0-8 hPa).
Main Results:
- Two infants showed normal respiratory mechanics, unaffected by PEEP.
- Four infants exhibited abnormal mechanics: two with low lung volumes/atelectasis, and two with expiratory airflow limitation.
- Increasing PEEP improved respiratory mechanics in infants with abnormal patterns.
Conclusions:
- Respiratory impedance measurements provide insights into bronchiolitis pathophysiology during mechanical ventilation.
- PEEP adjustments can be guided by respiratory impedance to improve outcomes in infants with bronchiolitis.
Abstract:
The aim of the study was to describe the pattern of respiratory oscillation mechanics and responses to positive end-expiratory pressure (PEEP) in bronchiolitis. Six infants were studied during the course of mechanical ventilation. A 20 Hz sinusoidal pressure variation was applied at the endotracheal tube where flow was measured with a pneumotachograph. Resistance and reactance obtained from the complex pressure-flow ratio were separated during inspiration (R(rs,i); X(rs,i)) and expiration (R(rs,e); X(rs,e)), and the differences between R(rs,i) and R(rs,e) (deltaR(rs)) and X(rs,i) and X(rs,e) (deltaX(rs)) were calculated. The data were corrected for the mechanical characteristics of the endotracheal tube. The measurements were repeated while PEEP was varied between 0 and 8 hPa. Two infants were found to have normal R(rs) and near-zero X(rs) and both parameters exhibited little change within the respiratory cycle or with varying PEEP. Four infants had high R(rs) at zero PEEP. In two, R(rs,i) was markedly elevated (108.5 and 85.2 hPa.s/L, respectively), and X(rs,i) was markedly negative (-25.0 and -22.5 hPa.s/L, respectively) at zero PEEP, while deltaR(rs) and deltaX(rs) were small. R(rs,i) and the absolute value of X(rs,i) decreased with increasing PEEP. This pattern of oscillation mechanics was consistent with low lung volumes and atelectasis, being reversed by increasing PEEP. In the remaining two subjects, R(rs,i) was moderately elevated (57.8 and 53.6 hPa.s/L, respectively) and X(rs,i) moderately negative (-12.5 and -7.7 hPa.s/L, respectively) at zero PEEP. DeltaR(rs) (-59.8 and -56.5 hPa.s/L, respectively) and delta(rs) (28.1 and 48.7 hPa.s/L, respectively) were large, but were dramatically reduced by increasing PEEP. These patterns were consistent with expiratory airflow limitation. Measurements of respiratory impedance are, therefore, informative in regard to the pathophysiological mechanisms occurring in bronchiolitis during mechanical ventilation, and they may be helpful in setting the level and assessing the effect of PEEP.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:17
Pulmonary Cycle: Exhalation
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: