Related Experiment Video
Updated: Aug 12, 2026


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Activity of erythrocyte sodium-hydrogen exchange in normal pregnancy
1Istituto di Clinica Medica II, Università di Pisa, Italy.

1. Pregnancy is associated with a 30-50% rise in cardiac output and a 50% increase in blood volume. The contribution of changes in the activity of primary and secondary active transporters to these haemodynamic adaptations remains unknown. For the first time, we measured sodium-hydrogen exchange activity over the course of normal pregnancy. 2. Eighteen healthy pregnant women were studied at 14, 24 and 33 weeks of gestation and compared with 18 non-pregnant healthy women. None of the pregnancies was complicated by hypertension. At each antenatal visit, body weight and blood pressure were recorded, blood and 24 h-urine samples were taken to control renal function and metabolic equilibrium, maternal glucose tolerance was evaluated by oral glucose test and glycated haemoglobin testing, and erythrocyte sodium-hydrogen antiport was also measured. 3. Erythrocyte antiport activity values were 10.0 +/- 3.0, 9.6 +/- 2.9 and 8.4 +/- 3.5 mmol h-1 (litre of cells)-1 in the three gestational trimesters respectively, significantly higher at each trimester than in control women [6.8 +/- 2.5 mmol h-1 (litre of cells)-1]. The clearances of urea and creatinine were constantly elevated in pregnant women; at each trimester their serum concentrations were lower than in non-pregnant women. Serum potassium significantly decreased during pregnancy. Serum total cholesterol and triacylglycerol levels, already above the normal range from the first trimester, further increased until the third trimester. The area under the glycaemic curve became larger during pregnancy, and the area under the insulinaemic curve increased to a lesser extent. There was a significant association between antiport activity and serum triacylglycerol levels. 4. The observed hyperactivity of the transporter, peaking at the fourteenth week of gestation, may be a contributing factor to the haemodynamic adjustments attending upon normal pregnancy.
1. Pregnancy is associated with a 30-50% rise in cardiac output and a 50% increase in blood volume. The contribution of changes in the activity of primary and secondary active transporters to these haemodynamic adaptations remains unknown. For the first time, we measured sodium-hydrogen exchange activity over the course of normal pregnancy. 2. Eighteen healthy pregnant women were studied at 14, 24 and 33 weeks of gestation and compared with 18 non-pregnant healthy women. None of the pregnancies was complicated by hypertension. At each antenatal visit, body weight and blood pressure were recorded, blood and 24 h-urine samples were taken to control renal function and metabolic equilibrium, maternal glucose tolerance was evaluated by oral glucose test and glycated haemoglobin testing, and erythrocyte sodium-hydrogen antiport was also measured. 3. Erythrocyte antiport activity values were 10.0 +/- 3.0, 9.6 +/- 2.9 and 8.4 +/- 3.5 mmol h-1 (litre of cells)-1 in the three gestational trimesters respectively, significantly higher at each trimester than in control women [6.8 +/- 2.5 mmol h-1 (litre of cells)-1]. The clearances of urea and creatinine were constantly elevated in pregnant women; at each trimester their serum concentrations were lower than in non-pregnant women. Serum potassium significantly decreased during pregnancy. Serum total cholesterol and triacylglycerol levels, already above the normal range from the first trimester, further increased until the third trimester. The area under the glycaemic curve became larger during pregnancy, and the area under the insulinaemic curve increased to a lesser extent. There was a significant association between antiport activity and serum triacylglycerol levels. 4. The observed hyperactivity of the transporter, peaking at the fourteenth week of gestation, may be a contributing factor to the haemodynamic adjustments attending upon normal pregnancy.

Related Concept Videos
 01:33
Hormonal Regulation
 01:14
Erythropoiesis
 01:20
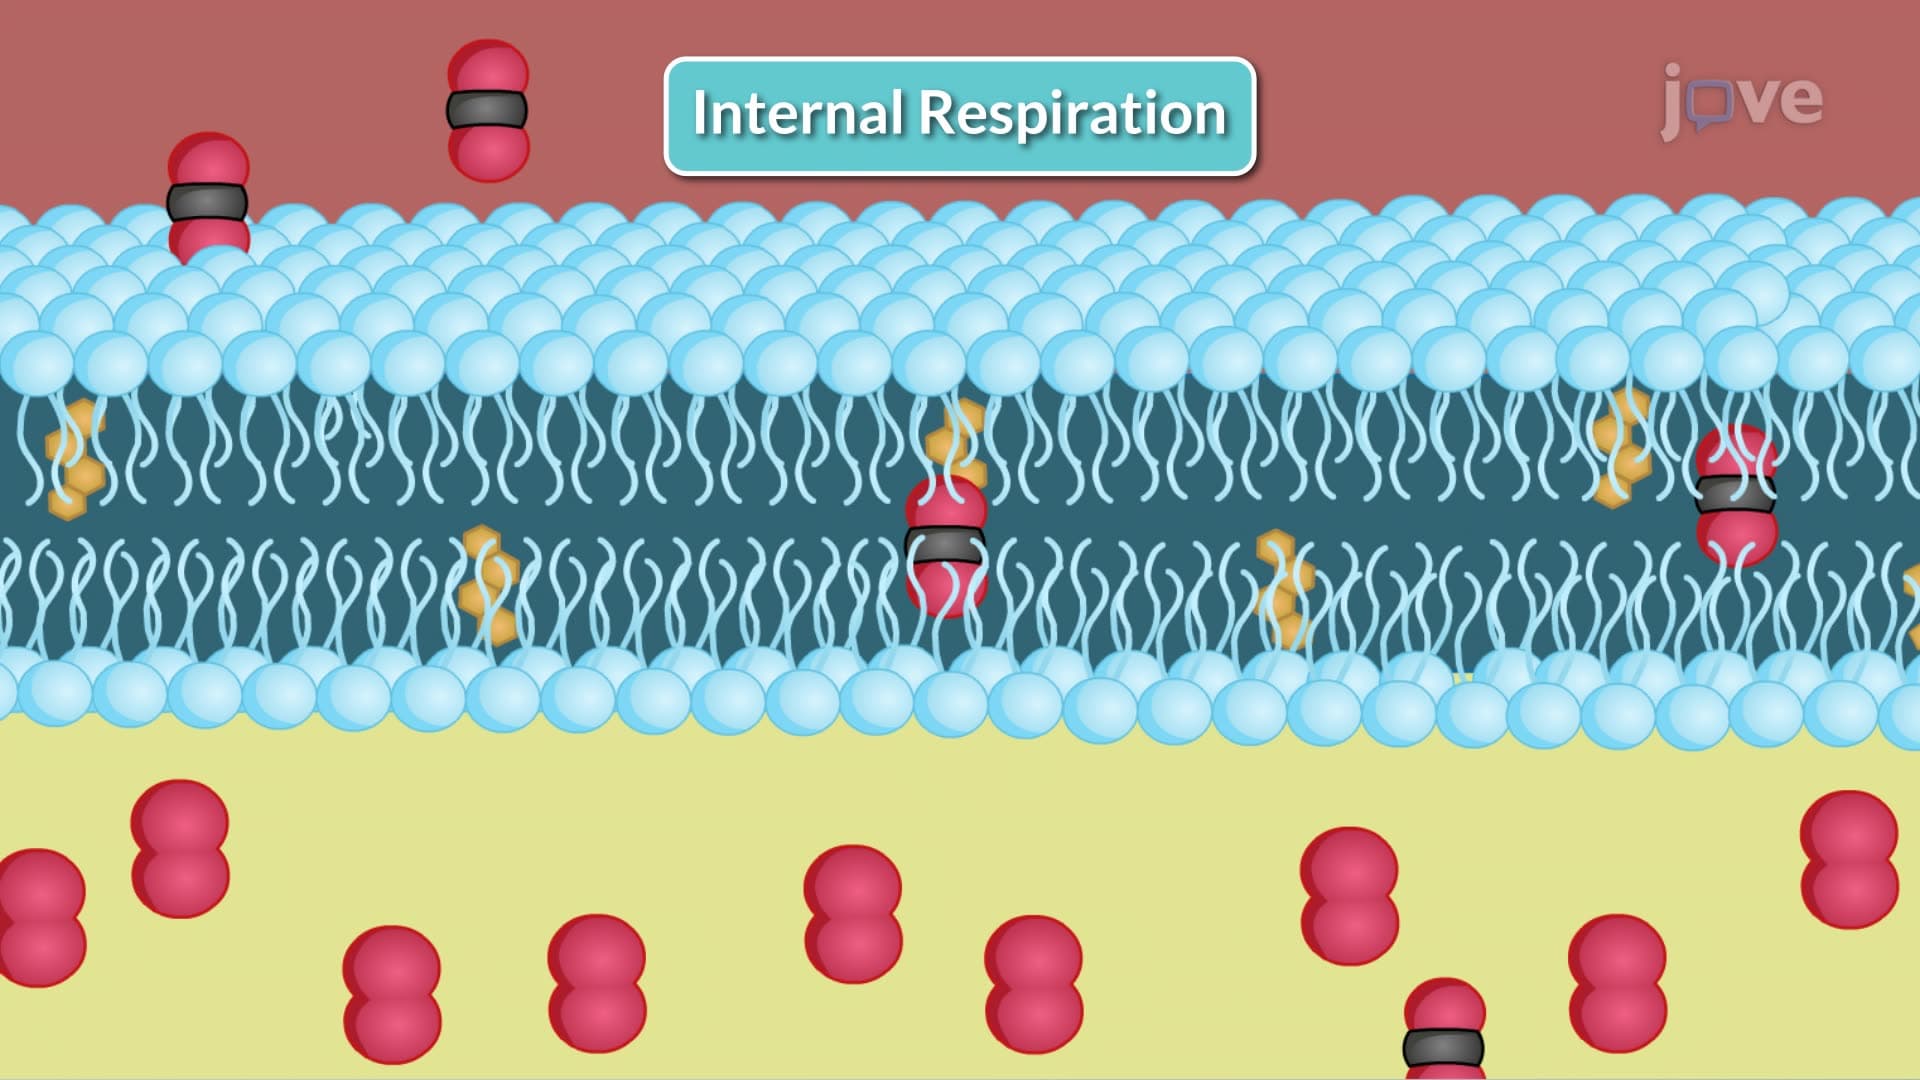
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
01:14Erythropoiesis
 01:24
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:27
Oxygen Transport in the Blood