Related Experiment Video
Updated: Aug 11, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Parathyroid responsivity in postmenopausal women with osteoporosis during treatment with parathyroid hormone
F Cosman1, J Nieves, L Woelfert
1Regional Bone Center, Helen Hayes Hospital, West Haverstraw, New York 10993, USA.

Abstract:
Endocrine systems may be affected permanently by administration of supraphysiologic doses of hormone. This is a well known complication of glucocorticoid treatment where the pituitary/adrenal axis may never fully recover, especially when large doses of steroids are needed during significant physical stress. The goal of this investigation was to determine whether responsivity of the parathyroid gland was normal after use of (1-34)PTH daily as an investigational therapy for osteoporosis. Patients were all postmenopausal osteoporotic women treated with estrogen and enrolled in a 3-yr trial of (1-34)PTH by daily subcutaneous injection (400 IU/day) in addition to their estrogen therapy. A volunteer subgroup (n = 10) of this population was recruited for this investigation. All patients had an EDTA-provoked hypocalcemic challenge before beginning PTH treatment. The same patients had repeat EDTA-challenge tests at various times during the 3-yr PTH treatment trial. Three patients had 2 infusions while on PTH treatment (interim and at the end of 3 yr). Ionized calcium declined identically before and during PTH treatment in response to the EDTA stimulus. PTH(1-84) responses were identical before and during PTH therapy. Furthermore, there were no differences in 1,25(OH)2D elevation or in phosphorus reduction over the course of the EDTA infusion during daily PTH treatment. Osteocalcin levels were higher during PTH treatment, as expected, but responsivity to acute endogenous PTH elevations was the same after PTH treatment. We conclude that 1-34PTH therapy, at 400 IU/day for up to 3 yr, does not suppress parathyroid responsivity and should therefore (at least within this period of treatment) have no permanent adverse effect on the ability of the body to maintain calcium homeostasis. Additionally, there is no difference in target organ responsivity to acute endogenous elevations of PTH after exogenous PTH therapy.


Related Concept Videos
 01:40
Bone Remodeling
 01:31
Osteoclasts in Bone Remodeling
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
 00:51
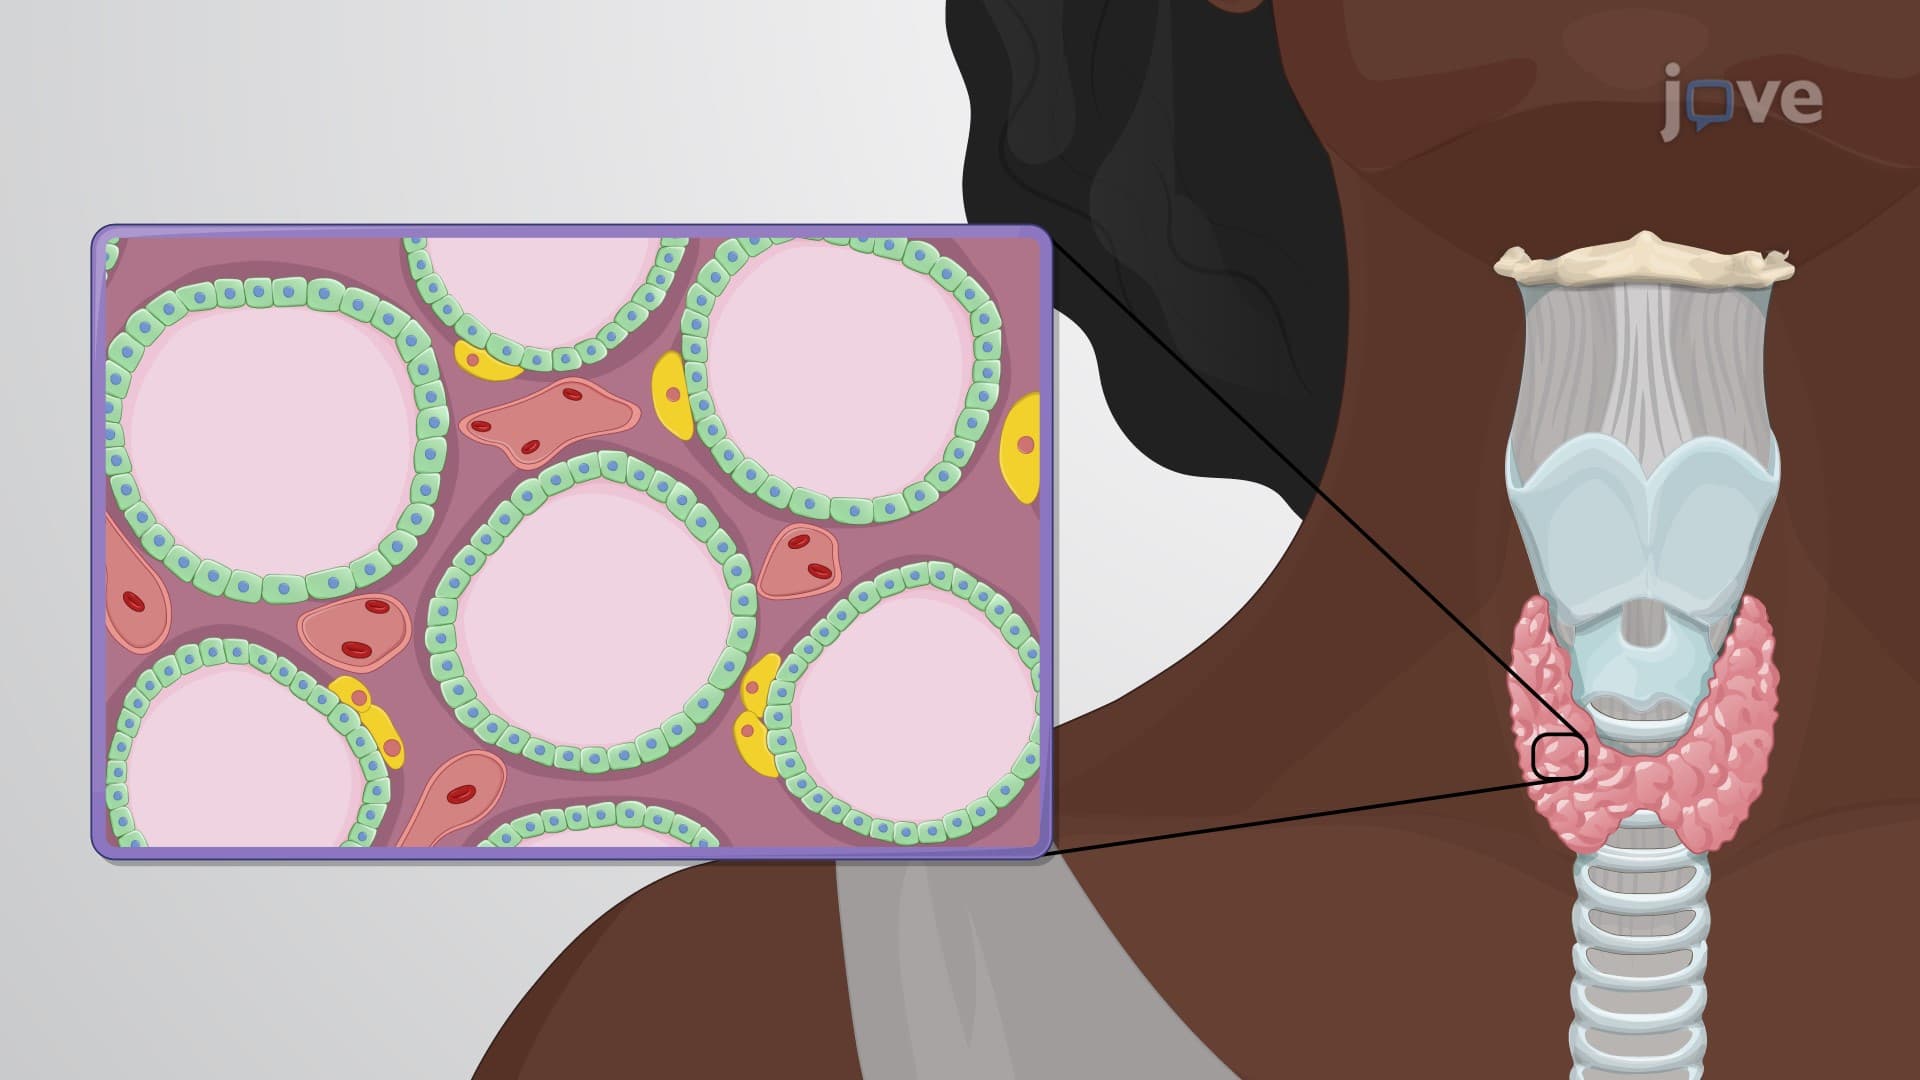
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 00:59
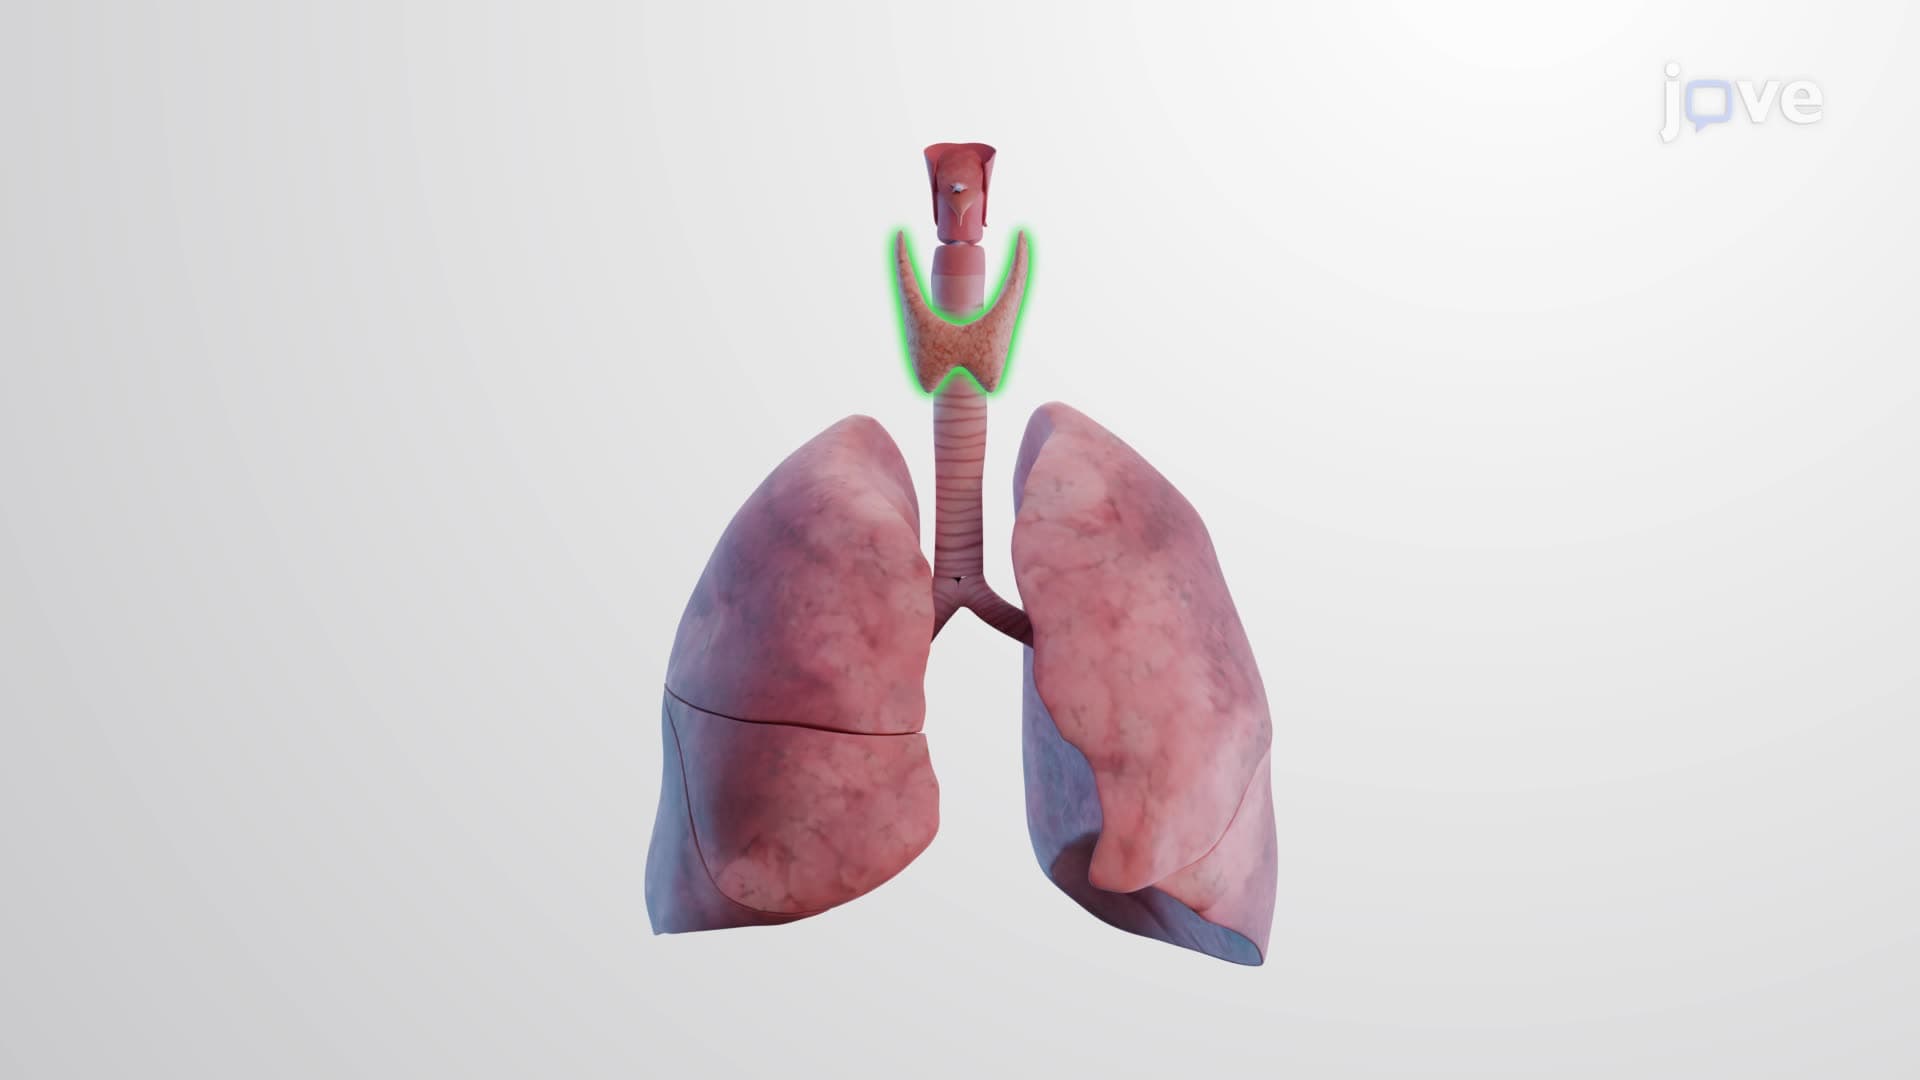
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...